Related Experiment Video
Updated: Dec 18, 2025


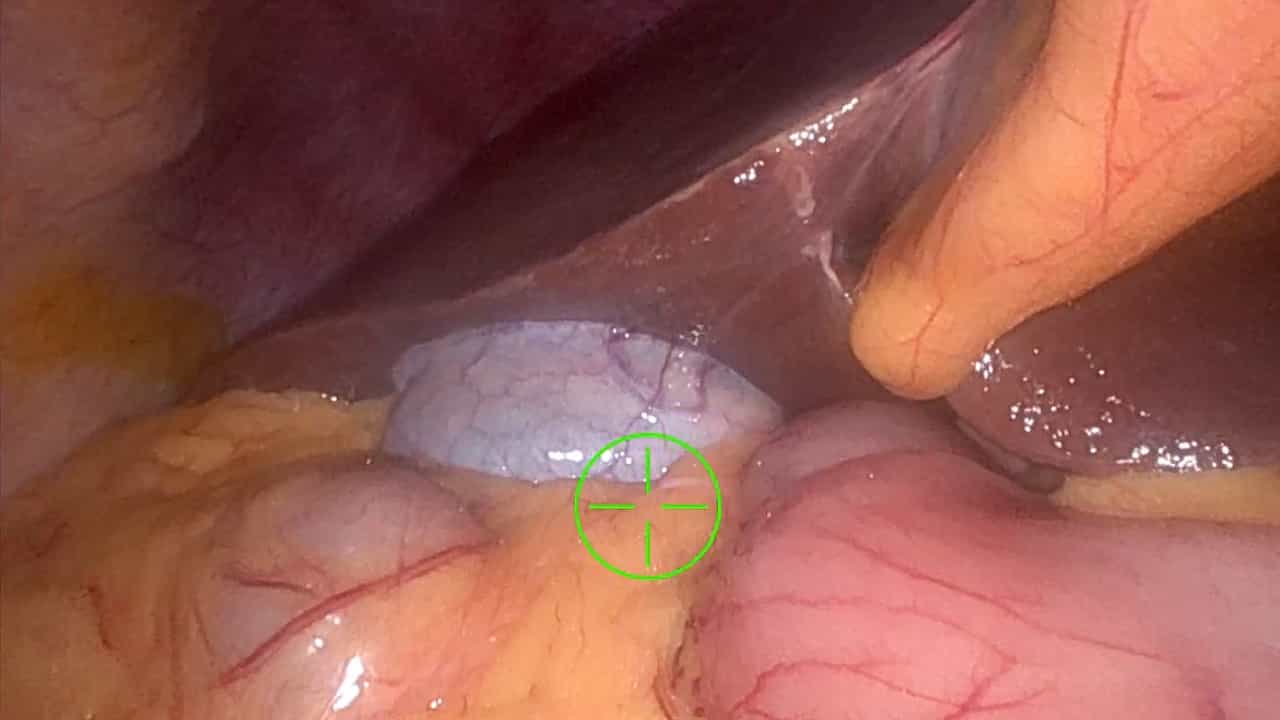
Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
Gastric pyloric gland adenoma resembling a submucosal tumor: A case report
Cong-Cong Min1, Jun Wu1, Feng Hou2
1Department of Gastroenterology, The Affiliated Hospital of Qingdao University, Qingdao 266003, Shandong Province, China.

Background:
Pyloric gland adenoma (PGA) is a recently described and rare tumor. Submucosal tumor (SMT)-like PGA is more difficult to diagnose and differentiate from other submucosal lesions.
Case Summary:
We present the case of a 69-year-old man with a 10 mm SMT-like elevated lesion with an opening in the upper part of the gastric body, referred to our hospital for further endoscopic treatment. Magnifying endoscopy with narrow-band imaging, endoscopic ultrasonography, and complete endoscopic submucosal dissection were performed on the patient. Histopathological findings revealed tightly packed tubular glands lined with cuboidal or columnar cells that had round-to-oval nuclei containing occasional prominent nucleoli and an eosinophilic cytoplasm similar to that in non-neoplastic gastric pyloric glands. Additionally, immunohistochemical analysis showed positive staining for both mucin 5AC and mucin 6. Therefore, we arrived at the final diagnosis of gastric PGA. Although there was no apparent malignant component in this tumor, PGA has been considered a precancerous disease with a high risk of transformation into adenocarcinoma.
Conclusion:
PGA should be considered when detecting gastric SMT-like lesions. Physicians and pathologists should focus on PGA due to its malignant potential.
Related Concept Videos
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds...
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors