
Traumatic diaphragmatic rupture successfully managed in 4-year-old patient: Case report and literature review
Adel Elkbuli1, Evander Meneses1, Aaron Shepherd1
1Department of Surgery, Kendall Regional Medical Center, Miami, FL, USA.

Insights
Traumatic diaphragmatic rupture in children is a rare but serious injury. Early diagnosis and surgical repair are crucial for preventing complications and ensuring a good recovery.
Area of Science:
- Pediatric Surgery
- Trauma Management
- Diagnostic Imaging
Background:
- Traumatic diaphragmatic rupture is uncommon in pediatric patients.
- Symptoms can be nonspecific, including dyspnea and abdominal pain, or the patient may be asymptomatic.
Observation:
- A 4-year-old boy sustained a diaphragmatic rupture after a motor vehicle accident.
- Initial presentation included hypoxia, abdominal/chest pain, and radiographic evidence of elevated diaphragm.
- Laparoscopy confirmed the rupture, followed by open surgical repair.
Findings:
- The case highlights the diagnostic challenges of traumatic diaphragmatic hernias due to low incidence and varied presentation.
- Chest radiography is a valuable initial tool, with CT scans serving as an accurate adjunct.
- Prompt surgical intervention leads to favorable outcomes.
Implications:
- A high index of suspicion is essential for diagnosing traumatic diaphragmatic hernias in pediatric blunt trauma.
- Delayed diagnosis can lead to significant morbidity and mortality.
- Surgical repair, even after delayed presentation, often results in recovery without major complications.
Introduction:
Traumatic diaphragmatic ruptures are rare injuries in the pediatric population that can present with dyspnea, abdominal pain, or even be asymptomatic.
Case Presentation:
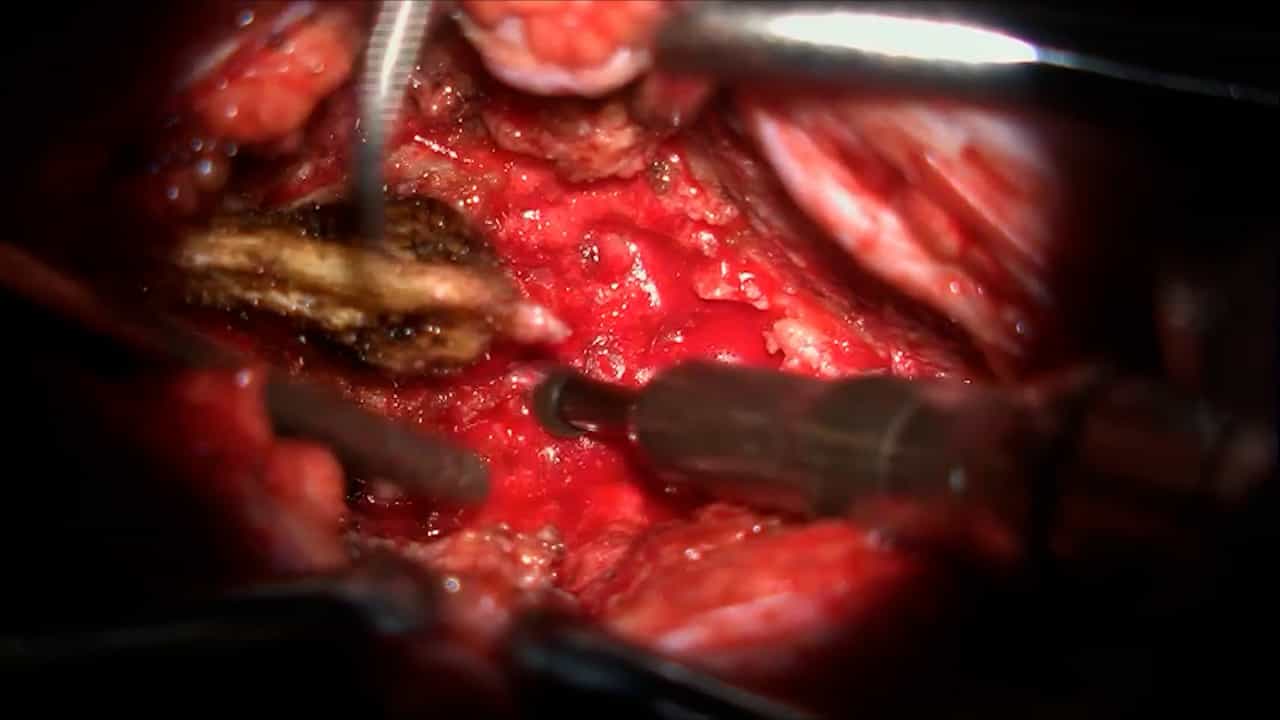
A 4-year-old boy presents to our Level 1 Pediatric Trauma Center after being hit by a car. He presented awake and alert but with low oxygen saturations and chief complaint of left sided abdominal and chest pain. The initial chest radiograph showed an elevated left diaphragm and bilateral opacities. A laparoscopic approach confirmed the diagnosis of a diaphragm rupture and an open approach allowed for the diaphragm repair, after returning the stomach, colon and spleen back to the abdominal cavity. He had an uneventful recovery and was discharged home on postoperative day seven.
Discussion:
Traumatic diaphragmatic hernia continues to be a difficult diagnosis to make without a high index of suspicion with variable time to diagnosis. This has been attributed to nonspecific clinical presentation and low incidence of the condition. Chest radiograph has been suggested to be an appropriate initial imaging modality with computed tomography as an accurate adjunct. Right sided diaphragm hernias, although less common, still occur and are often misdiagnosed. Recovery without significant morbidity after definitive surgical treatment with laparotomy is common.
Conclusion:
Consider a traumatic diaphragmatic hernia in a blunt pediatric trauma patient with abdominal pain and dyspnea once other life-threatening injuries have been ruled out. This is an easily missed injury that can lead to significant morbidity and mortality if not identified early in the patient's hospital course.

