Related Experiment Video
Updated: Dec 18, 2025
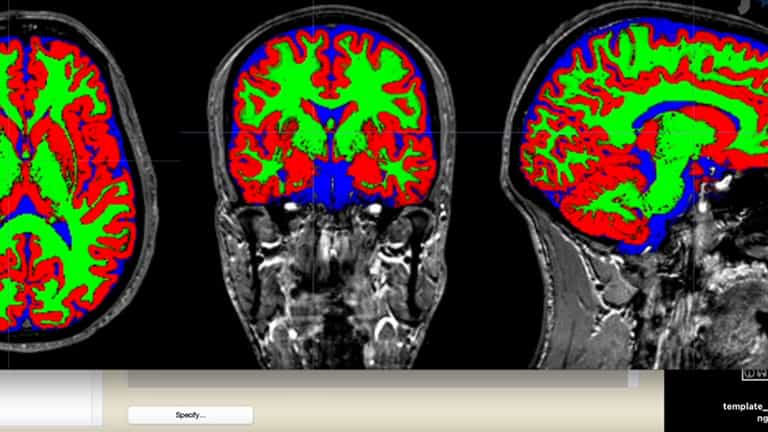

Brain Morphology of Cannabis Users With or Without Psychosis: A Pilot MRI Study
Published on: August 18, 2020
Recent cannabis use in HIV is associated with reduced inflammatory markers in CSF and blood
Ronald J Ellis1, Scott N Peterson2, Yueling Li1
1From the Departments of Neurosciences and Psychiatry (R.J.E.), University of California, San Diego; Sanford Burnham Prebys Medical Discovery Institute (S.N.P.); LECOM health - Millcreek Community Hospital (Y.L.), Erie, PA; Department of Pathology (R.S.), Department of Psychiatry (J.I., E.M., B.T., I.G., M.C.), and Departments of Medicine and Psychiatry (S.L.), University of California, San Diego. roellis@ucsd.edu.

Objective:
To determine whether cannabis may reduce HIV-related persistent inflammation, we evaluated the relationship of cannabis use in people with HIV (PWH) to inflammatory cytokines in CSF and blood plasma.
Methods:
We measured a panel of proinflammatory cytokines (interleukin [IL]-16, C-reactive protein [CRP], IL-6, interferon gamma-induced protein [IP]-10, soluble CD14, and soluble tumor necrosis factor receptor type II [sTNFRII]) in CSF and blood plasma in PWH and HIV- individuals who did or did not use cannabis at various levels of exposure. Participants in this observational cohort were recruited from community sources and underwent lumbar puncture and phlebotomy. Cannabis use parameters were characterized by self-report based on a semistructured timeline follow-back interview. Cytokines were measured using commercially available immunoassays. Data were analyzed using factor analysis.
Results:
Participants were 35 PWH and 21 HIV- individuals, mean (SD) age 45.4 (14.5) years, 41 cannabis ever users, and 15 never users. PWH and HIV- were not different in recency, cumulative months, grams, or density of cannabis use. A factor analysis using CSF biomarkers yielded a factor loading on CRP, IL-16, and sTNFRII that was significantly associated with recency of cannabis use (more recent use associated with lower factor 1 values, reflecting less inflammation; r = 0.331 [95% CI 0.0175, 0.586]). In particular, more recent cannabis use was related to lower IL-16 levels (r = 0.549 [0.282, 0.737]). Plasma biomarkers yielded a factor loading on sTNFRII and IP-10 that was associated with more recent cannabis use (more recent use related to less inflammation; r = 0.374 [0.0660, 0.617]).
Conclusions:
Recent cannabis use was associated with lower levels of inflammatory biomarkers, both in CSF and blood, but in different patterns. These results are consistent with compartmentalization of immune effects of cannabis. The principal active components of cannabis are highly lipid soluble and sequestered in brain tissue; thus, our findings are consistent with specific anti-neuroinflammatory effects that may benefit HIV neurologic dysfunction.

Related Concept Videos
 01:26
Sexually Transmitted Infections
 01:21
Chemotherapy-Induced Nausea and Vomiting: Cannabinoids
Two synthetic agonists of THC,...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:24
CNS Stimulants: Cocaine, Amphetamines and Cannabinoids
 01:10
Retrovirus Life Cycles