Related Experiment Video
Updated: Dec 18, 2025
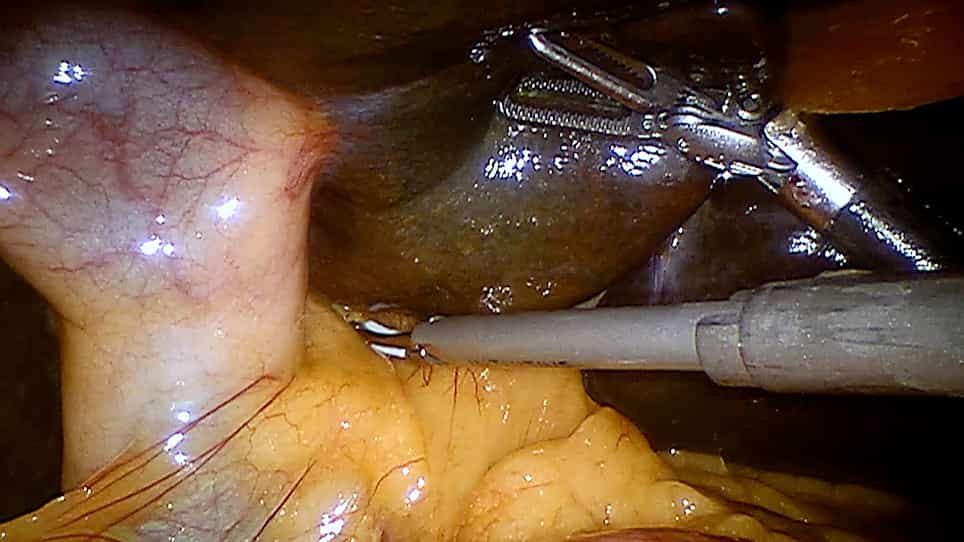

Robotic Taj Mahal Hepatectomy for Hilar Cholangiocarcinoma
Published on: July 14, 2022
Endoscopic treatment of hepaticojejunostomy anastomotic strictures using fully-covered metal stents
Tatsuya Sato1, Hirofumi Kogure1, Yousuke Nakai1,2
1Departments of, Department of, Gastroenterology, Graduate School of Medicine, The University of Tokyo, Tokyo, Japan.

Objectives:
With the emergence of the double-balloon endoscope (DBE), hepaticojejunostomy anastomotic strictures (HJASs) are increasingly managed endoscopically. However, balloon dilation and/or plastic stent placement may be associated with low stricture resolution rates and long treatment duration. We utilized a fully-covered metal stent (FCSEMS), which was designed for temporary placement for benign biliary strictures, and assessed its feasibility for patients with HJASs.
Methods:
We retrospectively studied 20 patients who underwent DBE-assisted FCSEMS placement for HJASs between June 2017 and March 2019. The FCSEMS was removed endoscopically at three months of stent placement. The outcomes investigated were the stricture resolution at the time of FCSEMS removal, the stricture recurrence, and adverse events.
Results:
Among 20 patients treated, stricture resolution was achieved in 17 patients (85.0%) at three months of stent placement. The FCSEMS was removed endoscopically without any technical difficulties in all cases except for two with asymptomatic stent migration due to stricture resolution. During a median follow-up period of 11.9 months (interquartile range, 7.5-18.0 months), an HJAS recurred in one patient (5.9%). For two patients without stricture resolution and one patient with recurrent stricture, another FCSEMS placement for 77, 84, and 186 days resolved the stricture. The overall stricture resolution rate was 95.0%. In one patient with FCSEMS-induced de novo stricture, long-term plastic stent placement was required. Procedure-related adverse events included mild cholangitis in two patients and mild pancreatitis in one patient.
Conclusions:
Endoscopic treatment using a FCSEMS via DB-ERCP was a feasible and effective treatment option for a HJAS.
More Related Videos
 09:40
An Ivor Lewis Esophagectomy Designed to Minimize Anastomotic Complications and Optimize Conduit Function
Published on: April 17, 2020
 07:44
Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...