Related Experiment Video
Updated: Dec 17, 2025
Author Spotlight: An Economic and Efficient Method for Quantitative Evaluation of Bone Microarchitecture in a Murine Osteoporosis Model
Published on: September 8, 2023
Deficits in bone strength, density and microarchitecture in women living with HIV: A cross-sectional HR-pQCT study
Heather M Macdonald1, Evelyn J Maan2, Claudie Berger3
1Department of Family Practice, Faculty of Medicine, University of British Columbia, 5950 University Blvd, Vancouver, British Columbia V6T 1Z3, Canada; Centre for Hip Health and Mobility, Vancouver Coastal Health Research Institute, 2735 Laurel St, Vancouver, British Columbia V5Z 1M9, Canada.

Insights
Women living with HIV (WLWH) on combined antiretroviral therapy (cART) show reduced bone density, microarchitecture, and strength compared to women without HIV. Tenofovir treatment may be linked to these bone deficits.
Area of Science:
- Bone biology and metabolism
- HIV/AIDS and comorbidities
- Osteoporosis research
Background:
- Combined antiretroviral therapy (cART) has improved life expectancy for people with HIV.
- Increased risk of osteoporosis and fragility fractures is a growing concern in this population.
- Understanding the impact of HIV and cART on bone health is crucial for managing long-term health.
Purpose of the Study:
- To investigate whether HIV status and cART influence three-dimensional bone mineral density (BMD), microarchitecture, and strength.
- To compare bone outcomes between women living with HIV (WLWH) and women without HIV (controls).
Main Methods:
- Dual-energy X-ray absorptiometry (DXA) for areal BMD (aBMD) at lumbar spine, total hip, and femoral neck.
- High-resolution peripheral quantitative computed tomography (HR-pQCT) for volumetric BMD, microarchitecture, and cortical parameters at distal radius and tibia.
- Finite element analysis (FEA) to assess bone strength (failure load); multivariable regression adjusted for osteoporosis risk factors.
Main Results:
- Women living with HIV (WLWH) aged ≥50 years had lower total hip aBMD T-scores compared to controls.
- Adjusted analysis revealed 8-19% lower distal radius trabecular bone mineral density (BMD), thickness, and distal tibia trabecular BMD and failure load in WLWH.
- Previous tenofovir treatment was negatively associated with distal radius bone microarchitecture and lumbar spine aBMD T-score in WLWH.
Conclusions:
- Women living with HIV exhibit compromised bone mineral density, microarchitecture, and strength compared to age- and menopausally-matched controls.
- Tenofovir-containing cART regimens may contribute to bone deficits in WLWH.
- Further research is needed to elucidate mechanisms and develop targeted interventions for bone health in WLWH.
Purpose:
With the advent of combined antiretroviral therapy (cART), life expectancy has increased among persons living with HIV, but so too has risk for comorbidities including osteoporosis and fragility fracture. To explore whether HIV status and cART influence three-dimensional measures of BMD, bone microarchitecture and strength we aimed to compare these outcomes between women living with HIV (WLWH; n = 50; 50.4 ± 1.2 years, 44% postmenopausal) and without HIV (controls; n = 50; 51.8 ± 1.2 years, 52% postmenopausal).
Methods:
Outcomes were lumbar spine, total hip and femoral neck areal BMD by DXA; distal radius and tibia trabecular BMD, thickness and number, and cortical BMD and area by HR-pQCT; and finite element analysis-derived bone strength (failure load). Multivariable regression analysis compared bone outcomes between groups adjusting for known osteoporosis risk factors. Within WLWH, we examined associations between bone outcomes and HIV-related factors including disease severity and cART duration.
Results:
WLWH were diagnosed 20 ± 4 years ago, were on cART for 123 ± 37 months and 80% had HIV plasma viral load <40 copies/mL. For women ≥50 years (n = 61), total hip aBMD T-Score was lower among WLWH than controls. Adjusted distal radius trabecular BMD and thickness and distal tibia trabecular BMD and failure load were 8-19% lower in WLWH than controls (p < 0.05). Cortical BMD and area did not differ between groups at either site. Lifetime cART duration and current plasma viral load were not associated with bone outcomes in WLWH; however, previous treatment with tenofovir was negatively associated with distal radius trabecular BMD and trabecular number and LS aBMD T-score.
Conclusions:
WLWH have compromised BMD, bone microarchitecture and strength vs. controls of similar age and reproductive status. Treatment with tenofovir may contribute to bone deficits in WLWH.
More Related Videos
 07:12
Semiautomated Longitudinal Microcomputed Tomography-based Quantitative Structural Analysis of a Nude Rat Osteoporosis-related Vertebral Fracture Model
Published on: September 28, 2017
 07:56
Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:40
Bone Remodeling
 01:31
Osteoclasts in Bone Remodeling
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:27
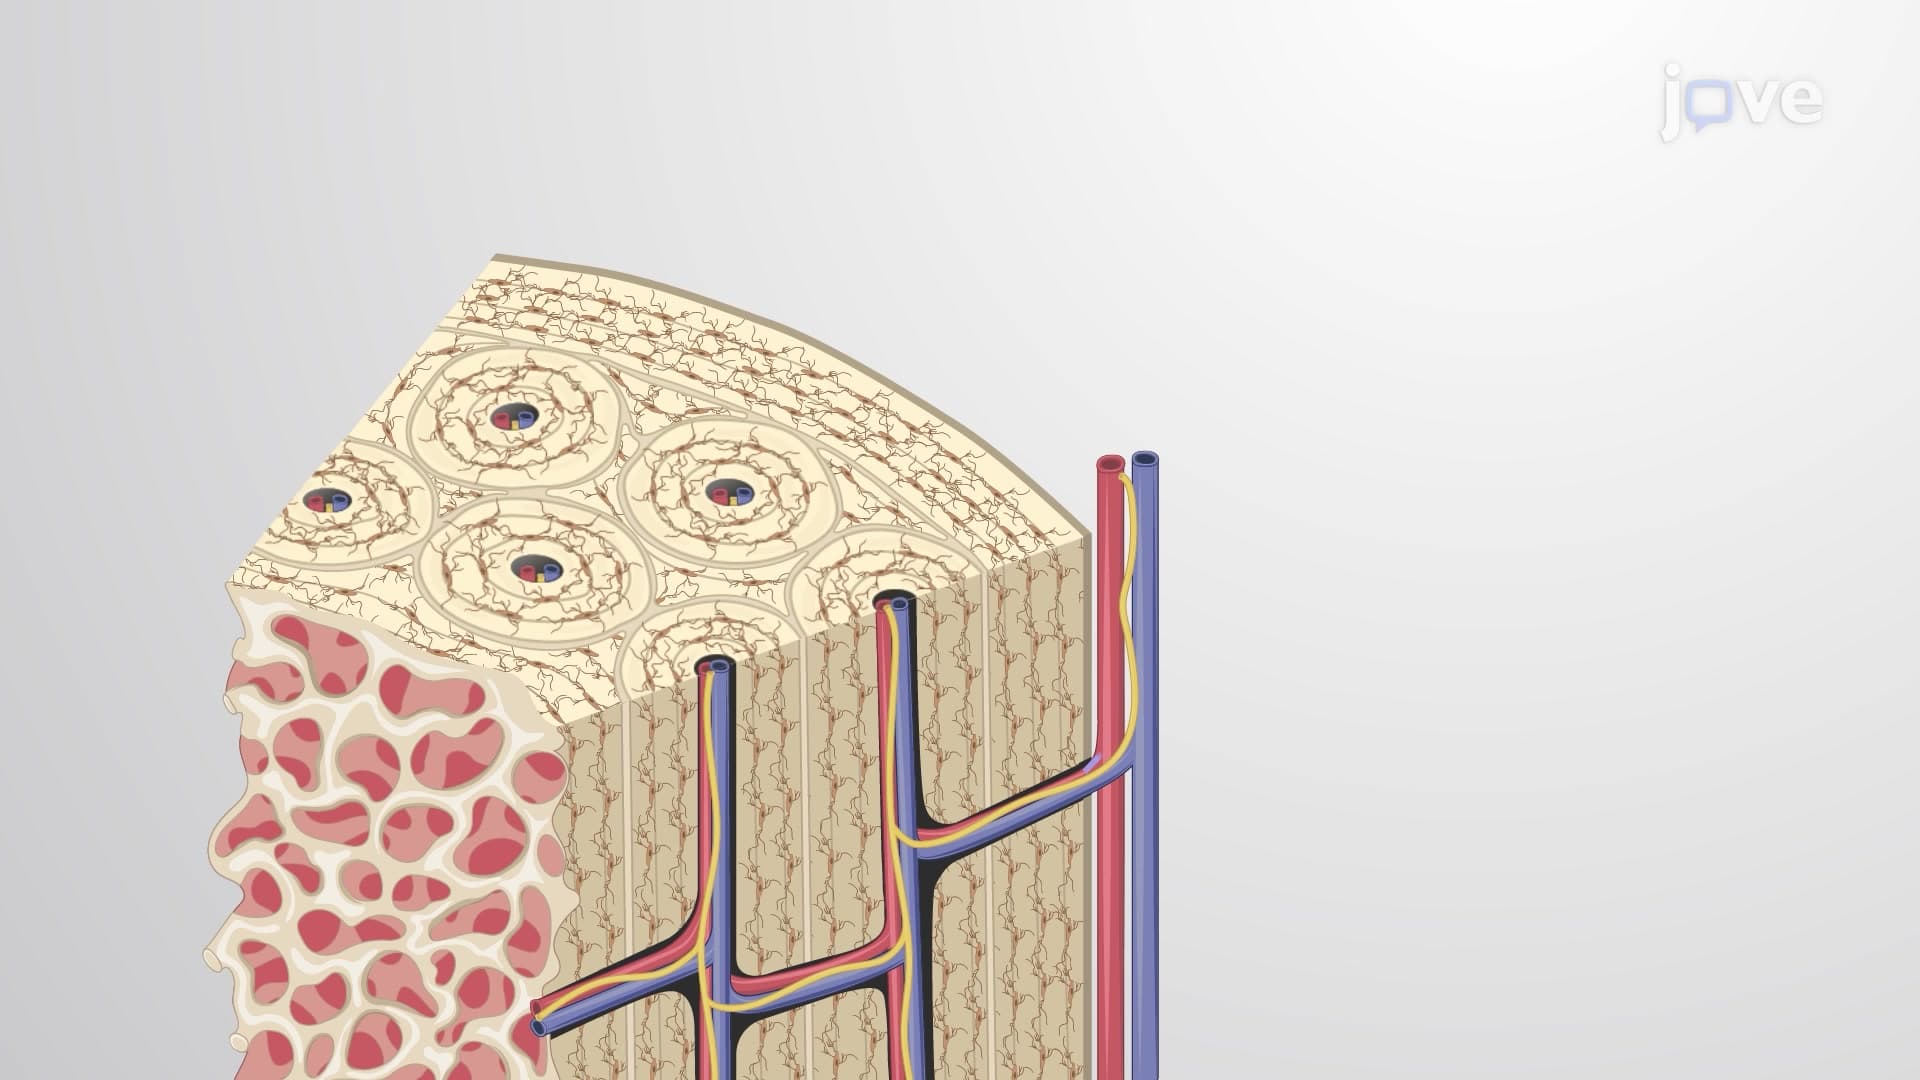
Compact Bone
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...