Related Experiment Video
Updated: Dec 16, 2025
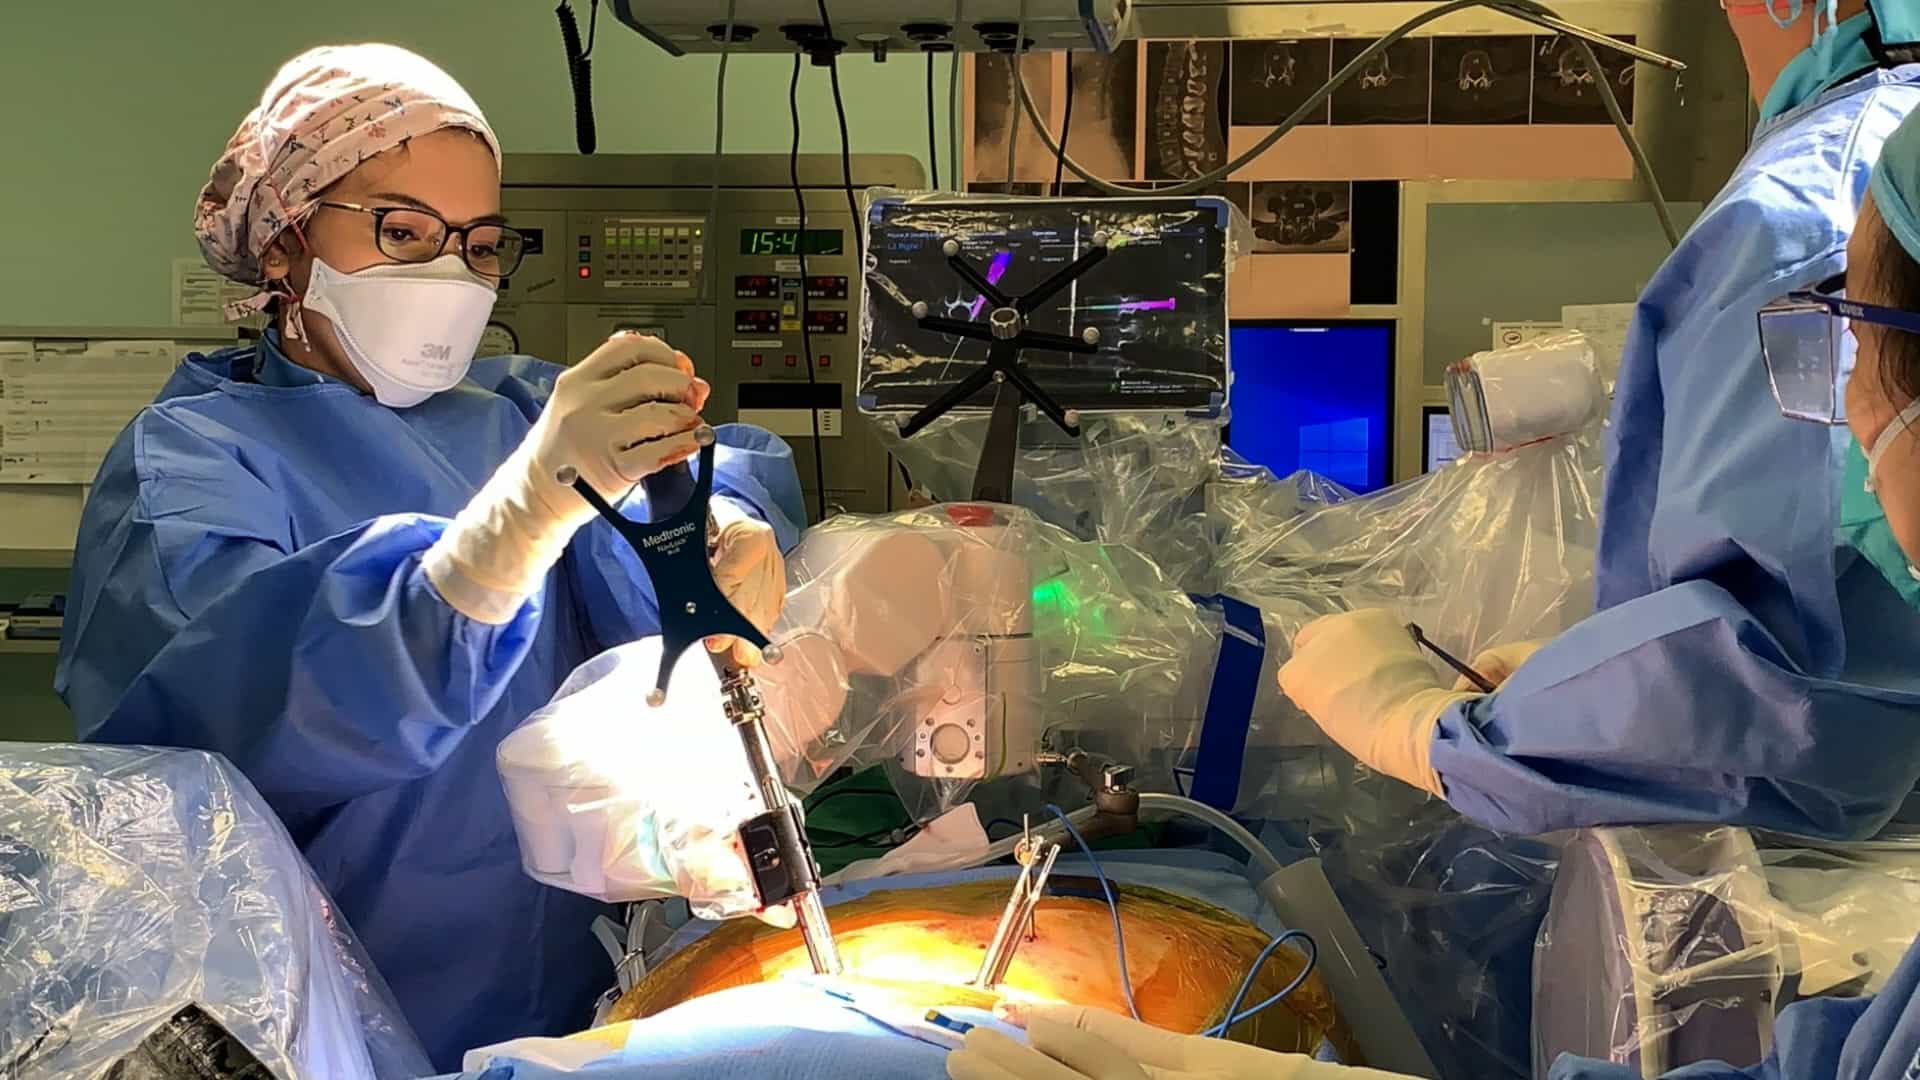

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Analysis of the Factors Affecting Lumbar Segmental Lordosis After Lateral Lumbar Interbody Fusion
Bungo Otsuki1, Shunsuke Fujibayashi1, Mitsuru Takemoto2
1Department of Orthopaedic Surgery, Graduate School of Medicine, Kyoto University, Kyoto, Japan.

Study Design:
Retrospective study.
Objective:
To elucidate factors that determine segmental lordosis after lateral retroperitoneal lumbar interbody fusion (LLIF) with percutaneous pedicle screw fixation.
Summary Of Background Data:
LLIF has been widely used in degenerative lumbar spine surgery. However, the detailed mechanisms that determine segmental lordosis are still unknown.
Methods:
A total of 69 patients who underwent LLIF with posterior pedicle screw fixation without posterior osteotomy were analyzed. Computed tomography was performed before and within 2 weeks after surgery, and segmental lordotic angle (SLA) after surgery (Post-SLA) was predicted using multiple regression analysis. Explanatory factors considered in this study included SLA before surgery (Pre-SLA), disc height before surgery (DiscH), cage position (CageP; distance between the center of the cage and the center of the disc, where a positive value indicates an anterior cage position), cage angle (CageA), cage height (CageH), CageH-DiscH (amount of lift up), previous decompression surgery, and level fused.
Results:
A total of 102 levels were analyzed. Multiple regression analysis revealed that the Post-SLA can be predicted with three independent variables, CageP, Pre-SLA, and CageH-DiscH and the adjusted R was 0.70. In cases when the cage was located anteriorly (CageP > 3 mm), Post-SLA was greater with larger CageH, larger CageA, and larger Pre-SLA. When the cage was located in the middle (3 mm ≤CageP ≤-1 mm), Post-SLA was greater with larger CageP, larger Pre-SLA, and without previous decompression surgery. If the cage was located posteriorly (CageP < -1 mm), Post-SLA was greater with smaller CageH-DiscH and greater Pre-SLA.
Conclusion:
To gain maximum segmental lordosis in LLIF, the cage should be located anteriorly. Furthermore, if the cage can be located anteriorly, a thicker cage with proper angle cage will gain segmental lordosis. If the cage is located posteriorly, a thin cage should be selected.
Level Of Evidence:
3.
More Related Videos
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
 08:38
Three-dimensional Navigation-guided, Prone, Single-position, Lateral Lumbar Interbody Fusion Technique
Published on: July 15, 2021