Related Experiment Video
Updated: Dec 16, 2025

Intracoronary Acetylcholine Provocation Testing for Assessment of Coronary Vasomotor Disorders
Published on: August 18, 2016
Different vasoreactivity of arterial bypass grafts versus native coronary arteries in response to acetylcholine
Giancarlo Pirozzolo1, Andreas Seitz2, Valeria Martínez Pereyra1
1Department of Cardiology, Robert-Bosch-Krankenhaus, Auerbachstr. 110, 70376, Stuttgart, Germany.

Insights
Coronary artery spasm, not atherosclerosis, frequently causes angina after coronary artery bypass grafting (CABG). Acetylcholine testing revealed spasm in native arteries but not bypass grafts, indicating spasm as a key post-CABG angina cause.
Area of Science:
- Cardiology
- Vascular Medicine
- Interventional Cardiology
Background:
- Coronary angiography is often used to investigate recurrent angina after coronary artery bypass grafting (CABG).
- Atherosclerosis progression is frequently sought, but often not found as the cause of symptoms.
- Coronary artery spasm is a potential, underdiagnosed cause of angina in this patient population.
Purpose of the Study:
- To investigate the role of coronary artery spasm in patients experiencing ongoing or recurrent angina after CABG.
- To assess vasoreactivity of native coronary arteries and bypass grafts using acetylcholine provocation testing.
Main Methods:
- A cohort study included 54 patients with previous left internal thoracic artery (LITA) bypass to the left anterior descending (LAD) artery, experiencing angina without significant stenosis.
- Intracoronary acetylcholine spasm provocation testing (ACh-test) was performed via the LITA bypass.
- Quantitative coronary analyses assessed vasoconstriction in native LAD and LITA grafts.
Main Results:
- Epicardial spasm occurred in 26% of patients, and microvascular spasm in 55%, with symptom reproduction.
- The ACh-test was normal in 19% of patients.
- Significant vasoconstriction was observed in the native LAD artery (52.43%) but not in the LITA bypass grafts (4.89%).
Conclusions:
- Coronary artery spasm (both epicardial and microvascular) is a common finding in patients with post-CABG angina and no significant stenosis.
- Acetylcholine testing demonstrates significantly different vasoreactivity between native LAD arteries and LITA grafts.
- Vasoconstriction predominantly affects the native LAD artery, suggesting it as the primary site of spasm-induced angina post-CABG.
Background:
Coronary angiography is often performed in patients with recurrent angina after successful coronary artery bypass grafting (CABG) in search of the progression of atherosclerosis. However, in many of these patients, no relevant stenosis can be detected. We speculate that coronary spasm may be associated with angina in these patients.
Methods:
From 2307 patients with unobstructed coronaries who underwent intracoronary acetylcholine spasm provocation testing (ACh-test) between 2012 and 2016, 54 consecutive patients who fulfilled the following inclusion criteria were included in this cohort study: previous left internal thoracic artery (LITA) bypass on the left anterior descending (LAD) coronary artery, ongoing/recurrent angina pectoris, no significant (< 50%) coronary artery or bypass stenosis. In all participants, the ACh-test was performed via the LITA bypass.
Results:
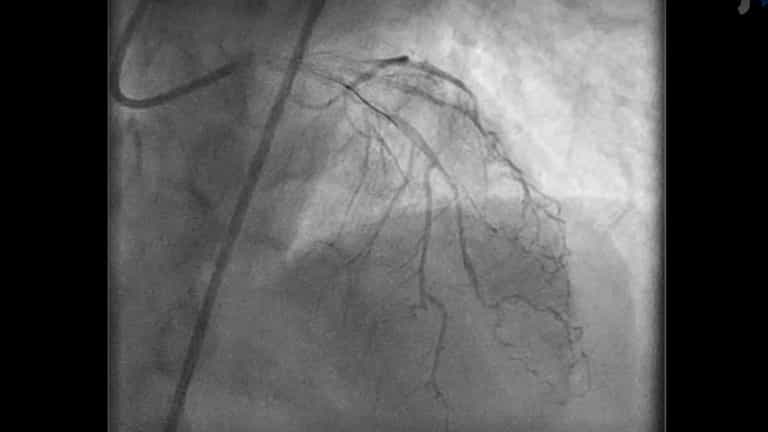
In 14 patients (26%) the ACh-test elicited epicardial spasm of the LAD distal to the anastomosis (≥ 90% diameter reduction with reproduction of the patient's symptoms and ischemic ECG shifts). Microvascular spasm (reproduction of symptoms and ischemic ECG-changes but no epicardial spasm) was seen in 30 patients (55%). The ACh-test was normal in the remaining 10 patients (19%). ACh-testing did not elicit any relevant vasoconstriction in the LITA bypasses in contrast to the LAD on quantitative coronary analyses (4.89 ± 7.36% vs. 52.43 ± 36.07%, p < 0.01).
Conclusion:
Epicardial and microvascular coronary artery spasm are frequent findings in patients with ongoing or recurrent angina after CABG but no relevant stenosis. Vasoreactivity to acetylcholine is markedly different between LITA bypasses and native LAD arteries with vasoconstriction almost exclusively occurring in the LAD.