Related Experiment Video
Updated: Dec 15, 2025

An Automated Culture System for Use in Preclinical Testing of Host-Directed Therapies for Tuberculosis
Published on: August 16, 2021
Defining treatment duration in atypical hemolytic uremic syndrome in adults: a clinical and pathological approach
1Division of Hematology & Medical Oncology, Department of Medicine, Weill Cornell Medical College, New York, New York.

Atypical hemolytic uremic syndrome (aHUS) is a thrombotic microangiopathy (TMA) that is driven by uncontrolled activation of the alternative complement pathway, classically in the context of a genetic or autoimmune complement abnormality. Initial guidelines suggested lifelong treatment with the C5 inhibitor eculizumab, which until recently was the only therapy approved by the US Food and Drug Administration and European Medicines Agency for aHUS. However, multicenter observational studies provide compelling evidence that discontinuation of eculizumab, with careful monitoring for recurrence of renal injury, is an option for some patients. Although relapse occurs in 20% to 35% of patients with aHUS after a median of 3 months (range, 1-30 months) following eculizumab cessation, ostensibly irrespective of initial treatment duration, successful rescue with reinstitution of drug has been described in small cohorts if relapse is promptly recognized and eculizumab is immediately re-started. Rates of off-treatment TMA are higher in children than in adults; they are also elevated in those with a personal or family history of aHUS, certain complement mutations or anti-complement factor H autoantibodies, a renal allograft, or extrarenal manifestations of aHUS. Given the complex and unpredictable nature of aHUS, prospective trials defining the optimal treatment duration in diverse settings are required. In the interim, this review-which excludes pediatric patients and hematopoietic stem cell transplant recipients-suggests that eculizumab may be discontinued in some groups of patients; discontinuation should be undertaken on a case-by-case basis and with careful monitoring, following 6 to 12 months of treatment for aHUS that encompasses at least 3 months of normalization of renal function or stabilization of chronic renal disease.
Atypical hemolytic uremic syndrome (aHUS) is a thrombotic microangiopathy (TMA) that is driven by uncontrolled activation of the alternative complement pathway, classically in the context of a genetic or autoimmune complement abnormality. Initial guidelines suggested lifelong treatment with the C5 inhibitor eculizumab, which until recently was the only therapy approved by the US Food and Drug Administration and European Medicines Agency for aHUS. However, multicenter observational studies provide compelling evidence that discontinuation of eculizumab, with careful monitoring for recurrence of renal injury, is an option for some patients. Although relapse occurs in 20% to 35% of patients with aHUS after a median of 3 months (range, 1-30 months) following eculizumab cessation, ostensibly irrespective of initial treatment duration, successful rescue with reinstitution of drug has been described in small cohorts if relapse is promptly recognized and eculizumab is immediately re-started. Rates of off-treatment TMA are higher in children than in adults; they are also elevated in those with a personal or family history of aHUS, certain complement mutations or anti-complement factor H autoantibodies, a renal allograft, or extrarenal manifestations of aHUS. Given the complex and unpredictable nature of aHUS, prospective trials defining the optimal treatment duration in diverse settings are required. In the interim, this review-which excludes pediatric patients and hematopoietic stem cell transplant recipients-suggests that eculizumab may be discontinued in some groups of patients; discontinuation should be undertaken on a case-by-case basis and with careful monitoring, following 6 to 12 months of treatment for aHUS that encompasses at least 3 months of normalization of renal function or stabilization of chronic renal disease.
More Related Videos
 11:17
Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
 05:23
Continuous Manual Exchange Transfusion for Patients with Sickle Cell Disease: An Efficient Method to Avoid Iron Overload
Published on: March 14, 2017
Related Concept Videos
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:28
Acute Pyelonephritis II: Diagnostic Studies and Management
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:22
Acute Kidney Injury I: Introduction
 01:15
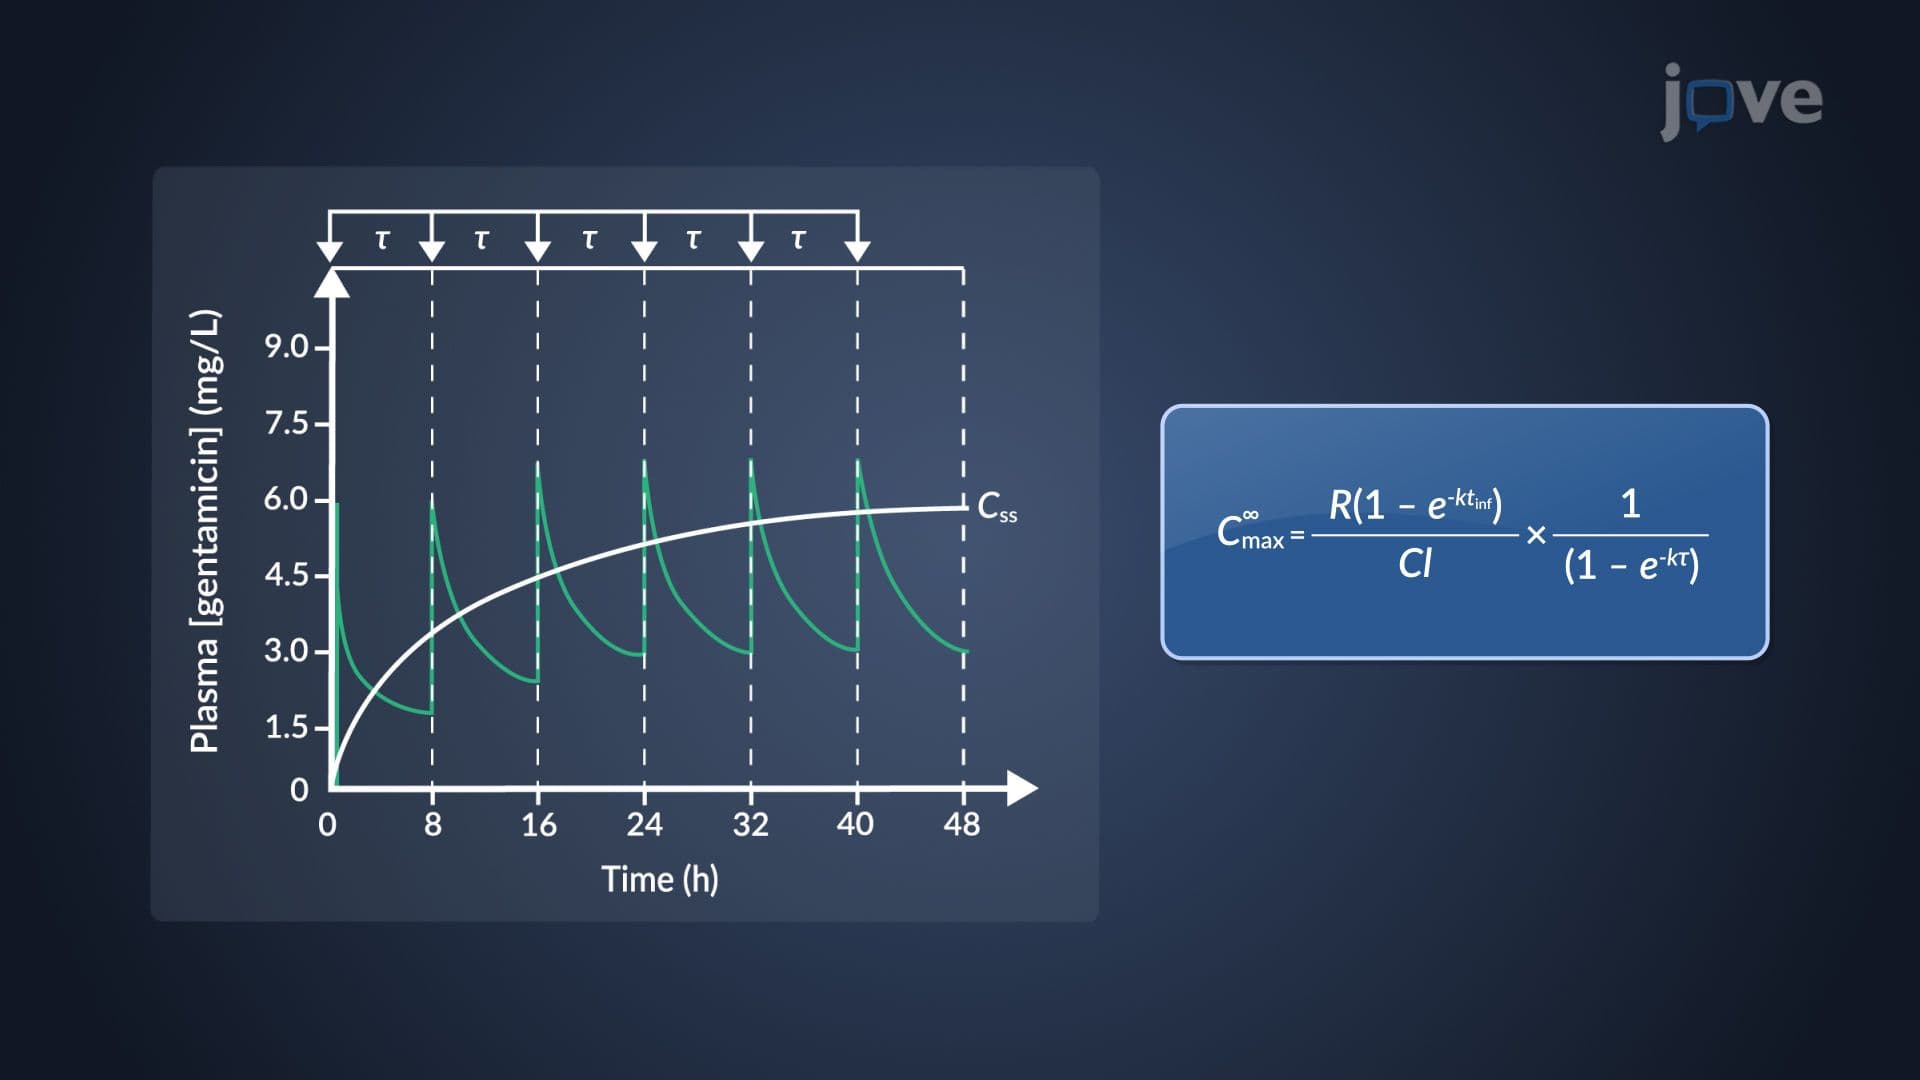
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:30
Continuous Renal Replacement Therapy