Related Experiment Video
Updated: Dec 15, 2025


Author Spotlight: Advancing Early Detection and Treatment of Gastrointestinal Tumors
Published on: February 16, 2024
Clinicopathological study of blue nevi of the gastrointestinal (GI) tract: first case series
Naziheh Assarzadegan1, Kevan Salimian2, Danielle Hutchings2
1Pathology, Johns Hopkins University, Baltimore, Maryland, USA nassarz1@jhmi.edu.

Aim:
Blue nevus (BN) is a benign melanocytic proliferation that is typically cutaneous. Extracutaneous BN is infrequent and is reported in the mucosa of various organs. Gastrointestinal (GI) tract BN is rare. Here, we describe the clinicopathological findings of the largest series of GI tract BNs.
Methods:
A search of our Pathology Data System (1984-2019) identified six GI tract blue nevi. Clinical information, pathology reports and available H&E-stained section slides were reviewed.
Results:
Lesions predominated in the middle-aged adults (mean 54, range 27-80) with a slight female predominance (66%). Most cases arose in the rectum and colon (83%), with one gastric lesion (17%). Four cases were identified during endoscopic examination performed either for screening or for unrelated symptoms (66%). Two patients presented with rectal bleeding (33%) unassociated with the BN. Endoscopically, most lesions appeared as superficial hyperpigmented areas (83%). One case was described as abnormal mucosa (17%). Microscopically, the mucosa was involved in all of the cases (100%). One case showed submucosal extension in addition to the mucosal component (17%). Lesions showed a proliferation of bland spindle cells with abundant granular pigment. No nuclear atypia or mitoses were identified. Immunostains showed immunoreactivity for melanocytic markers. Follow-up information available for five patients showed no recurrences to date (mean follow-up 1 year).
Conclusions:
BN is a benign melanocytic proliferation. It is important to be aware of the occurrence of such lesions outside of the skin and consider the possibility of BN when pigmented lesions are encountered in the GI tract.


Related Concept Videos
 01:20
Histology of the Gastrointestinal (GI) Tract
The mucosa is sometimes called a mucous membrane due to its mucus-secreting features. This membrane is composed of epithelium, which directly interacts with ingested substances, and the lamina propria, a layer...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:26
Imaging Studies III: Gastrointestinal Motility Studies and Virtual Colonoscopy
Radionuclide Testing
Radionuclide testing is a sophisticated medical technique for assessing gastrointestinal motility. It focuses on gastric emptying and colonic transit time. Radioactive markers track the movement of food through the digestive system, providing insights into gastrointestinal disorders.
In gastric emptying studies, a meal's liquid and...
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...
 01:26
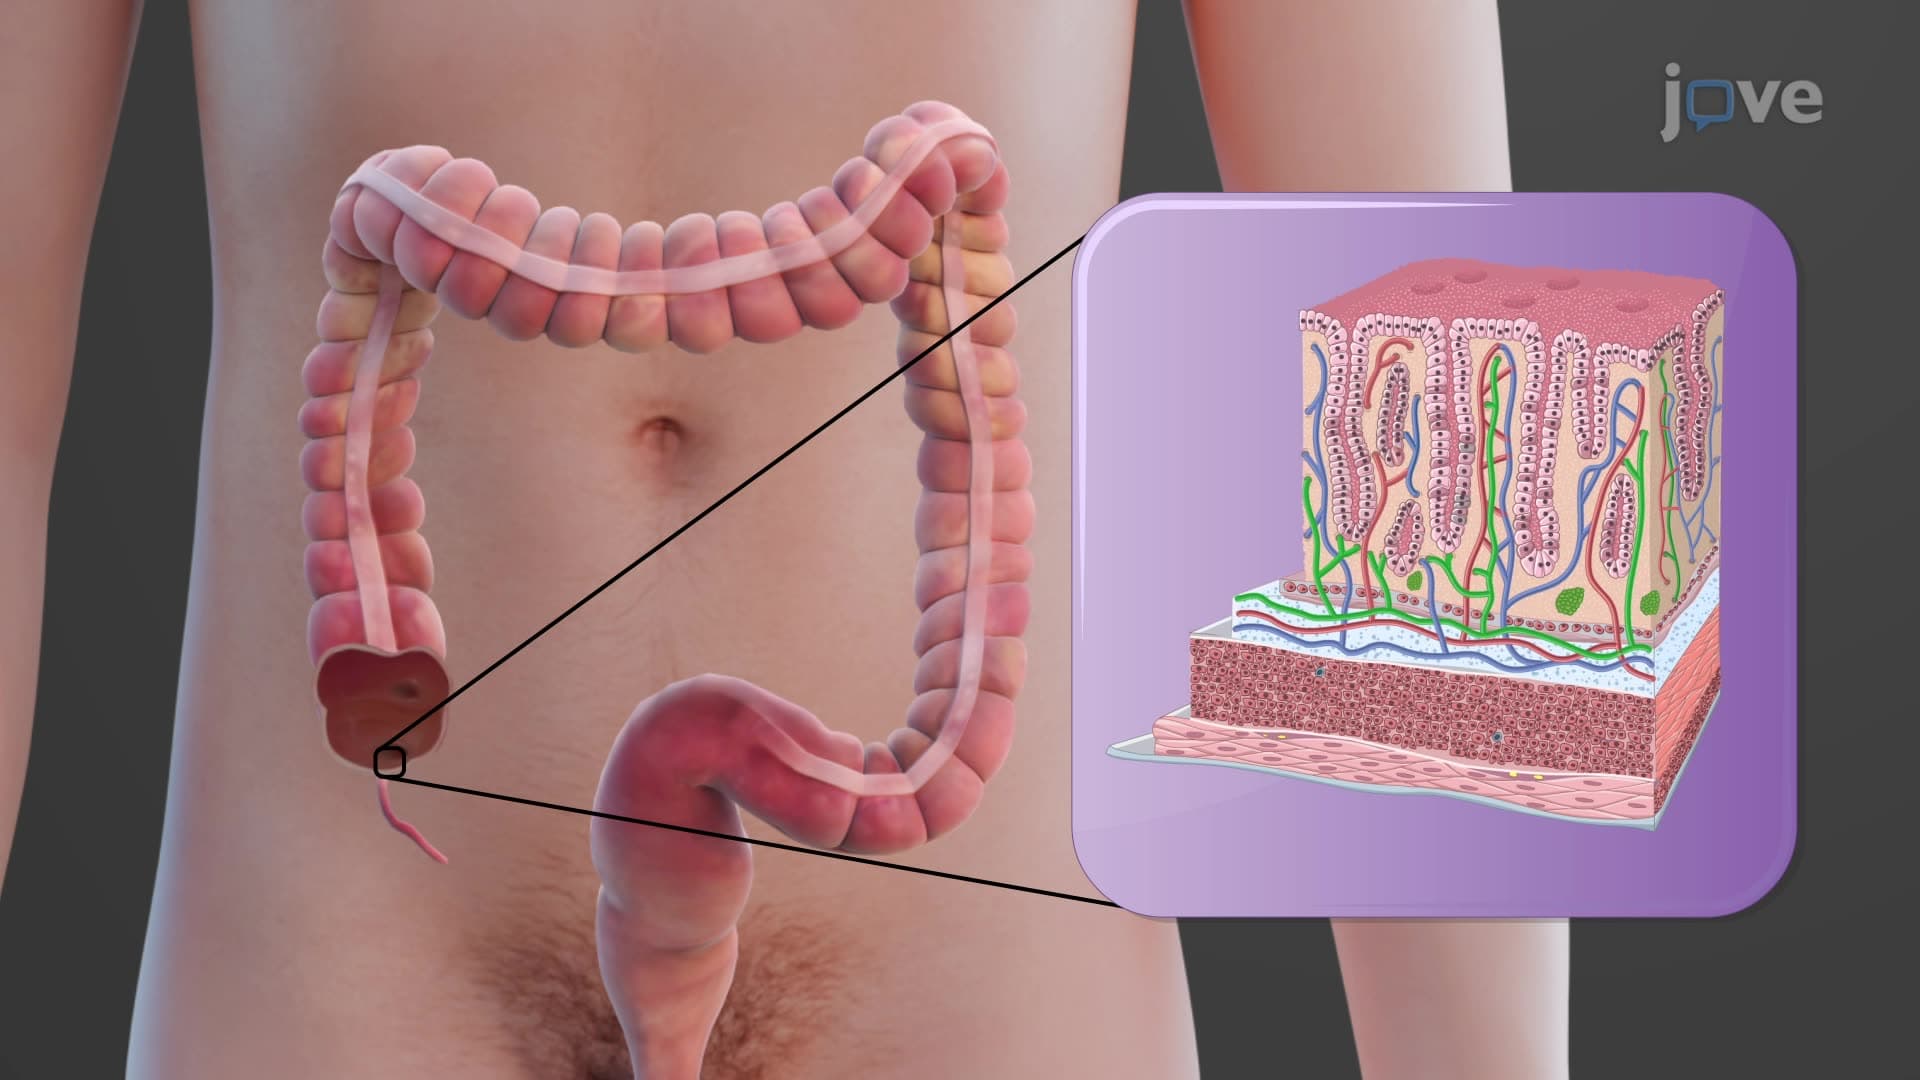
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...