Related Experiment Video
Updated: Dec 15, 2025
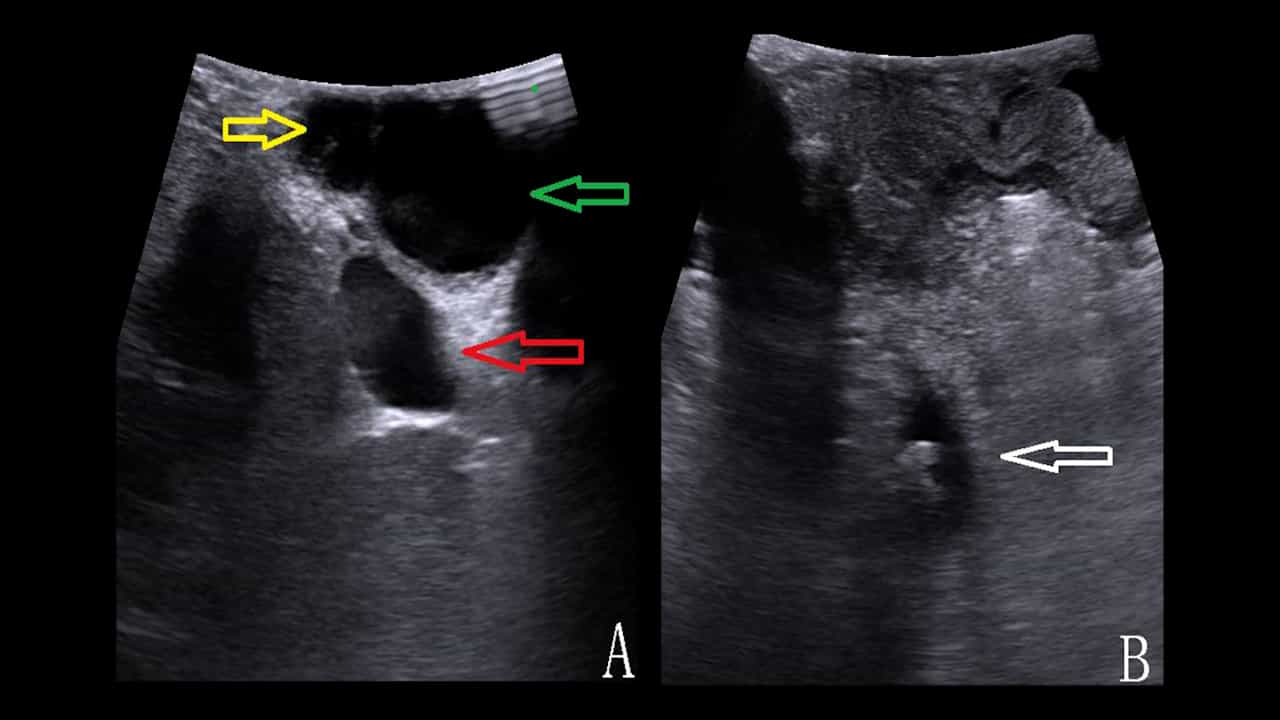
Application of Laparoscopic Ultrasonography in Primary Choledochal Suture during Combined Two-lens Surgery
Published on: March 28, 2025
One-session laparoscopic management of Mirizzi syndrome: feasible and safe in specialist units
Ahmad H M Nassar1, Mahmoud K Nassar2, Ines C Gil3
1Laparoscopic Biliary Surgery Service, Department of General Surgery, University Hospital Monklands, Airdrie, ML6 0JS, Lanarkshire, Scotland, UK. Ahmad.nassar@glasgow.ac.uk.

Background:
To evaluate the laparoscopic management of Mirizzi syndrome, seldom diagnosed preoperatively causing difficulty when performing cholecystectomy and increasing complication risks.
Methods:
Analysis of a prospective single-surgeon database of 5700 laparoscopic cholecystectomies found 58 Mirizzi syndrome cases. They were managed with an intention to treat during the index admission according to protocol of single-session management of bile duct stones.
Results:
38/58 patients were females (65.5%). The median age was 55 years. 53 cases were emergency admissions. 34 cases (58.6%) only had ultrasound scanning. Operative difficulty was Grade IV in 34 cases (58.6%) and Grade V in 20 (34.5%) (Nassar Scale). There were 33 Mirizzi Type IA, 7 Type IB, 16 Type II and one each of Type III and Type IV. Bile duct exploration was performed in 94.8% through choledochotomy/ transfistula in 58.6% or transcystic in 36.2%. Four cases required conversion to open. Postoperative morbidity occurred in 29%. Two 30-day mortalities occurred from pneumonia in two elderly patients who were late referrals.
Conclusion:
Although the utilization of the laparoscopic approach in managing bile duct stones is not currently widely practiced it was safer in this series than in reported series of open surgery in Mirizzi Syndrome. The optimal approach to Mirizzi Type II is via cholecystocholedochal fistula to explore the bile duct then drain with T-tube through the fistula. It is unnecessary to perform bilioenteric bypass in majority of cases, reducing the morbidity and mortality.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...