Related Experiment Video
Updated: Dec 15, 2025
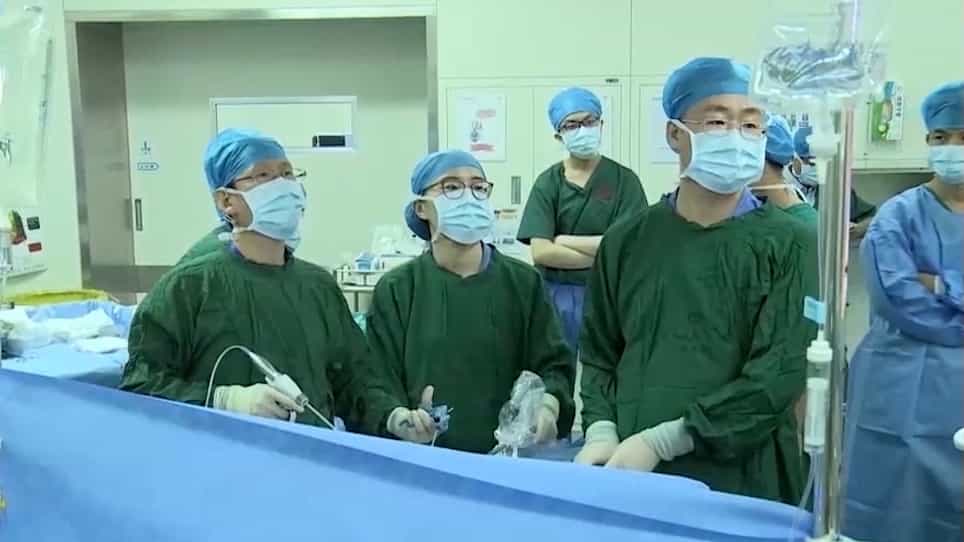

Laparoscopy-endoscopy Cooperative Surgery for the Treatment of Gastric Gastrointestinal Stromal Tumors
Published on: February 19, 2022
Large population-based study using the SEER database: is endoscopic resection appropriate for early gastric cancer
Bo Yang1, Kaidi Sun1, Yangyang Hui1
1Department of Gastroenterology and Hepatology, General Hospital, Tianjin Medical University, Tianjin, China.

Aim:
To investigate whether endoscopic treatment is applicable to American patients and explores the predictors of lymph node metastasis (LNM) in early gastric cancer (EGC).
Methods:
Patients with EGC confined to either mucosa (T1a, n = 1799) and submucosa (T1b, n = 1689) were identified from the Surveillance, Epidemiology, and End Result database. Multivariate logistic regression, Kaplan-Meier method, and univariate/multivariate Cox regression were used to assess the correlation between invasion depth and LNM or prognosis. A nomogram for predicting LNM was constructed and internally validated.
Results:
EGC limited to T1a exhibited a 2.4% incidence of LNM, which increased to 11.1% when the depth invaded T1b.LNM was present at 1.4%, 5.2%, and 5.0% for sizes ≤2, 2-5, and >5cm of low-grade T1a EGC, respectively, (p = .019) and at 4.8%, 12.4%, and 28.6% of T1b EGC, respectively (p < .001).The multivariate logistic model revealed that older age, T1b invasion, larger tumor size, and high-grade lesions were associated with a higher risk of LNM. Moreover, the T1a EGC patients had better cancer-specific survival (OS) and overall survival(CSS) compared with the T1b EGC patients (5-year OS: 77.2% versus 67.4%, p < .001; 5-year CSS: 90.6% versus 81.4%, p < .001). The discrimination of the prediction model was 0.745.
Conclusions:
Endoscopic treatment may only be suitable for patients in the US population who have low-grade T1a lesions of less than 2 cm in size. Patients with T1a lesions of greater than 2 cm in size, lesions with high-grade, and all T1b lesions may benefit from radical surgical resection with lymphadenectomy.

