Related Experiment Video
Updated: Dec 14, 2025


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Is Breast Size Related to Prevalent Thoracic Vertebral Fracture? A Cross-Sectional Study
Linda Spencer1, Leanda McKenna1, Robyn Fary1
1School of Physiotherapy and Exercise Science Curtin University Perth Western Australia Australia.

Abstract:
Large breasts may increase the likelihood of thoracic vertebral fractures by increasing the mechanical loading of the spine. We examined breast size as a factor associated with prevalent thoracic vertebral fractures, also considering its relationship with thoracic kyphosis and upper back extensor muscle endurance. Using a cross-sectional study, the design measurements collected were thoracic vertebral fractures (≥20% loss in vertebral body height on lateral radiograph), breast size (bra size converted to an ordinal breast size score), BMD (g/cm2 averaged femoral neck, DXA), upper back extensor muscle endurance (isometric chest raise test), body composition (DXA), thoracic kyphosis (radiograph), and upper back pain (numerical rating scale). Correlations and multivariable logistic regression examined relationships between characteristics and their association with vertebral fracture. Participants were 117 healthy postmenopausal women. The 17 (15%) women with ≥1 thoracic vertebral fracture had larger breast size (mean difference [MD]: 2.2 sizes; 95% CI, 0.6 to 3.8 sizes), less upper back extensor muscle endurance (MD: -38.6 s; 95% CI, -62.9 to -14.3 s), and greater thoracic kyphosis (MD: 7.3°; 95% CI, 1.7° to 12.8°) than those without vertebral fracture. There were no between group differences in age, height, weight, and BMD. Breast size (r = -0.233, p = 0.012) and thoracic kyphosis (r = -0.241, p = 0.009) correlated negatively with upper back extensor muscle endurance. Breast size was unrelated to thoracic kyphosis (r = 0.057, p = 0.542). A (final) multivariable model containing breast size (OR 1.85; 95% CI, 1.10 to 3.10) and thoracic kyphosis (OR 2.04; 95%CI, 1.12 to 3.70) explained 18% of the variance in vertebral fracture. Breast size had a significant, but weak relationship with vertebral fracture (R 2 = 0.10), which was independent of BMD and unrelated to thoracic kyphosis. Further work is needed to confirm larger breast size as a risk factor for vertebral fracture. © 2020 The Authors. JBMR Plus published by Wiley Periodicals, Inc. on behalf of American Society for Bone and Mineral Research.
More Related Videos
 07:12
Semiautomated Longitudinal Microcomputed Tomography-based Quantitative Structural Analysis of a Nude Rat Osteoporosis-related Vertebral Fracture Model
Published on: September 28, 2017
 07:56
Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Related Concept Videos
 01:17
The Thoracic Cage: Sternum
The sternum is the elongated bony structure on the anterior side of the thoracic cage. It consists of three parts: the manubrium, the body, and the xiphoid...
 01:24
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:15
Thoracic Aorta
 01:16
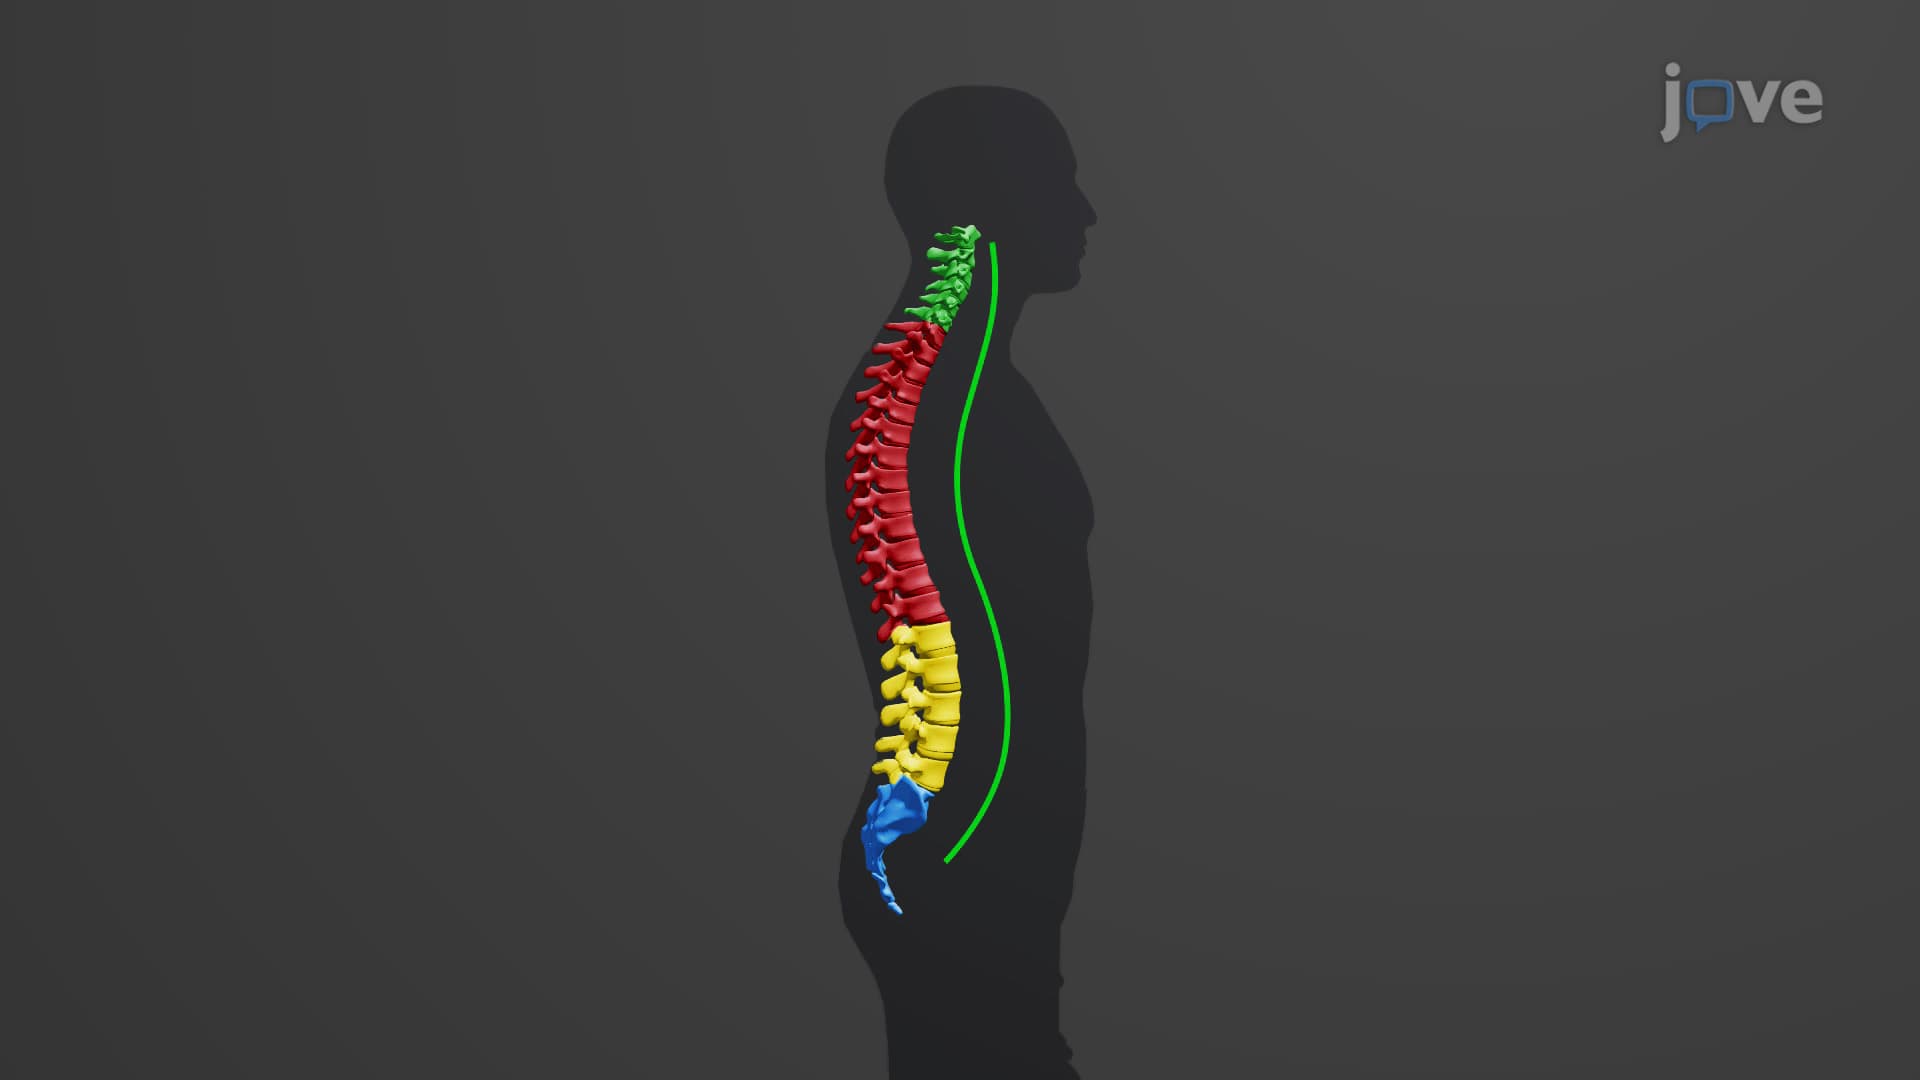
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:20
The Thoracic Cage: Ribs
Parts of a Typical Rib
A typical rib has a head, neck, and body. The posterior end of the rib is called the head, followed by a narrow neck. The head articulates primarily with the costal...
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies