Related Experiment Video
Updated: Dec 14, 2025
Measurement of Dynamic Scapular Kinematics Using an Acromion Marker Cluster to Minimize Skin Movement Artifact
Published on: February 10, 2015
Update on the Biomechanics of the Craniocervical Junction, Part II: Alar Ligament
Basem Ishak1,2,3, Alexander von Glinski1,2,4, Graham Dupont1
1526590Seattle Science Foundation, Seattle, WA, USA.

Study Design:
In vitro biomechanical study.
Objective:
The strength of the alar ligament has been described inconsistently, possibly because of the nonphysiological biomechanical testing models, and the inability to test the ligament with both attachments simultaneously. The purpose of this biomechanical model was to reevaluate the alar ligament's tensile strength with both bony attachments, while also keeping the transverse ligament intact, all in a more physiological biomechanical model that mimics the mechanism of traumatic injury closely.
Methods:
Eleven fresh-frozen occipito-atlanto-axial (C0-C1-C2) specimens were harvested from individuals whose mean age at death was 77.4 years (range 46-97 years). Only the alar and transverse ligaments were preserved, and the bony C0-C1-C2 complex was left intact. Axial tension was exerted on the dens to displace it posteriorly, while the occipito-axial complex was fixed anteriorly. A device that applies controlled increasing force was used to test the tensile strength (M2-200, Mark-10 Corporation).
Results:
The mean force required for the alar ligament to fail was 394 ± 52 N (range 317-503 N). However, both the right and left alar ligaments ruptured simultaneously in 10 specimens. The ligament failed most often at the dens (n = 10), followed by occipital condyle rupture (n = 1). The transverse ligament remained intact in all specimens.
Conclusions:
When both the right and left alar ligament were included, the total alar ligament failure occurred at an average force of 394 N. The alar ligament failed before the transverse ligament.
More Related Videos
 07:09
In situ Compressive Loading and Correlative Noninvasive Imaging of the Bone-periodontal Ligament-tooth Fibrous Joint
Published on: March 7, 2014
 07:30
A Test Bed to Examine Helmet Fit and Retention and Biomechanical Measures of Head and Neck Injury in Simulated Impact
Published on: September 21, 2017
Related Concept Videos
 01:28
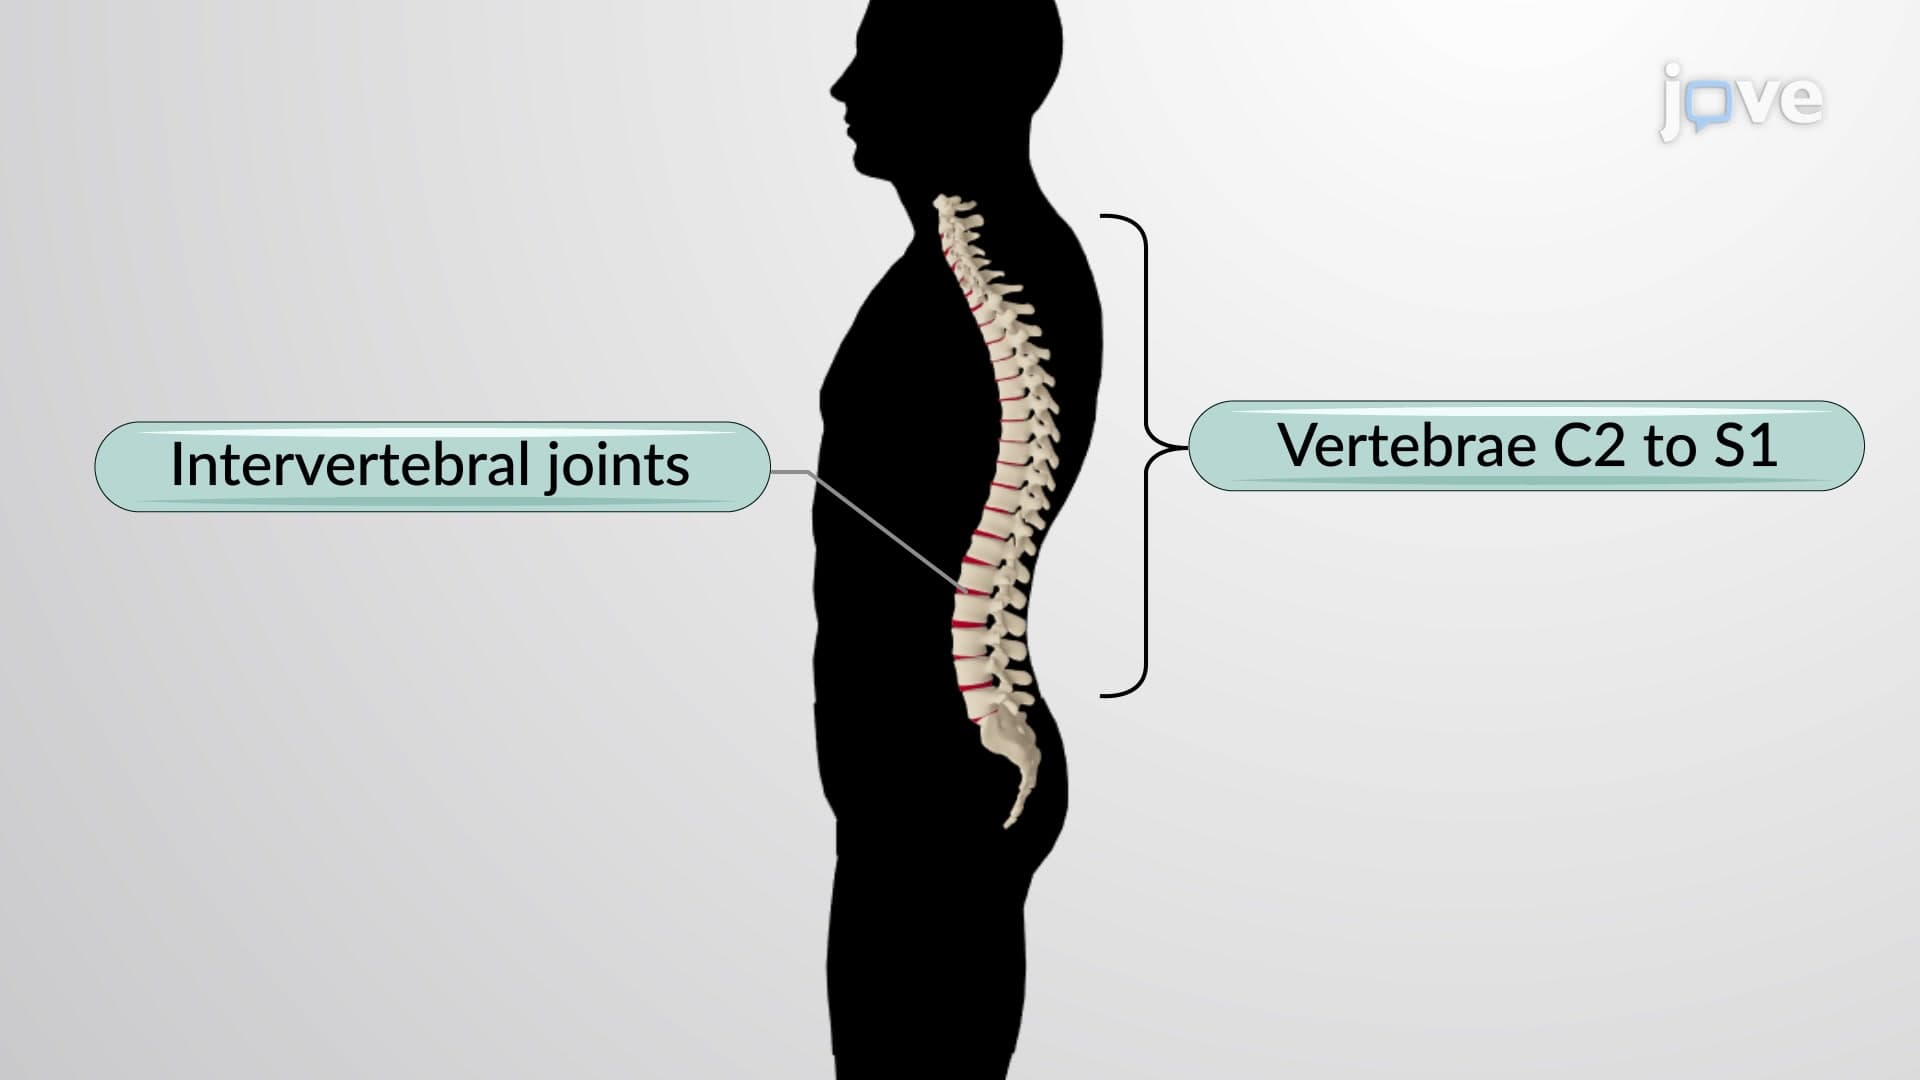
Articulations of the Vertebral Column
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:10
Ankle Joint
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:17
Structural Joints: Cartilaginous Joints
There are two types of cartilaginous joints:
Synchondrosis
A synchondrosis ("joined by cartilage") is a cartilaginous joint where bones are connected by hyaline cartilage. Synchondrosis may be temporary...