Related Experiment Video
Updated: Dec 14, 2025


Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
Nomogram to Predict Risk of Postoperative Urinary Retention in Women Undergoing Pelvic Reconstructive Surgery
Adrienne L K Li1, Alex Zajichek2, Michael W Kattan2
1Division of Urogynecology, Department of Obstetrics and Gynecology, Sunnybrook Health Sciences Centre, Toronto, ON.

Objective:
To develop a nomogram that determines an individual's risk of postoperative urinary retention (POUR) following pelvic floor reconstructive surgery.
Methods:
We performed a retrospective chart review of women who underwent reconstructive surgery for pelvic organ prolapse and/or stress urinary incontinence. Short-term POUR was defined as failure of the trial of void (post-void residual >150 mL with a void of >200 mL) on postoperative day one or the need for re-catheterization in the first 2 postoperative days. Potential pre- and intraoperative risk factors for POUR were compared between patients with and without POUR. Multivariate binary logistic regression analysis with best-subsets variable selection was used to create a predictive nomogram.
Results:
Most patients (275 of 332) had concomitant or combined procedures. The overall incidence of POUR was 31% (103 of 332 patients). The risk of POUR was higher for patients with high-grade anterior prolapse and those who had undergone anterior vaginal repair, vaginal hysterectomy, or a laparoscopic sling procedure. Patients who did not experience POUR tended to have fewer co-morbidities and were more likely to have undergone laparoscopic colposacropexy. Risk factors for POUR in the nomogram were diabetes, multiple medical co-morbidities, laparoscopic sling procedure, anterior vaginal repair, laparoscopic colposacropexy, and vaginal hysterectomy. The nomogram allows clinicians to calculate a patient's risk of POUR (range <10% to >80%).
Conclusion:
While the predictive nomogram in this study was developed using a single surgeon's case series and may not be generalizable to all surgeons, it demonstrates that the risk of POUR may be predicted based on clinical characteristics and the type of surgery performed. This kind of prediction model could help guide clinicians in preoperative patient counseling.
More Related Videos
 03:49
Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse POP Quantification System
Published on: September 20, 2018
 06:46
Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
Related Concept Videos
 01:21
Nursing Assessment of the Genitourinary System I: Health History
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:26
Nursing Assessment of the Genitourinary System II: Inspection and Palpation
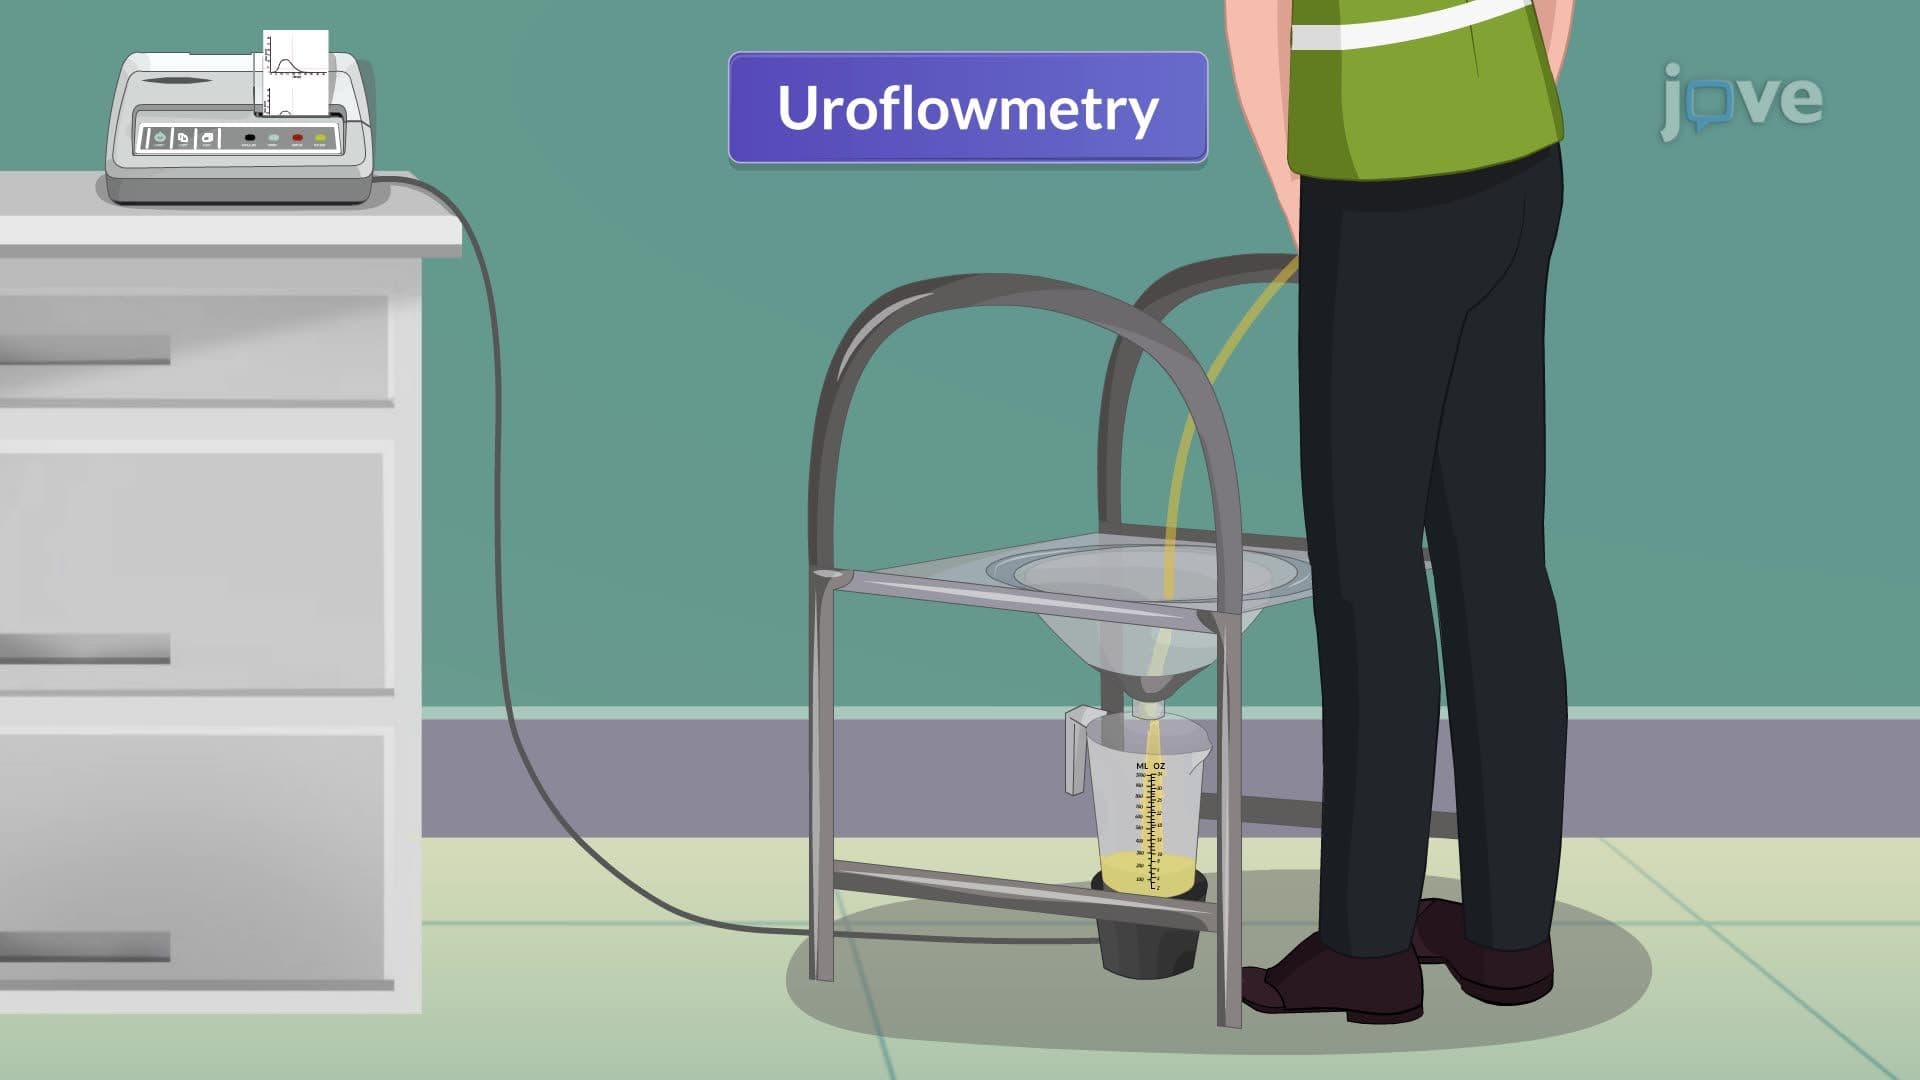 01:19
Urodynamic Studies: Uroflowmetry
 01:28
Urinary Tract Calculi V: Nursing Management
 01:22
Imaging Studies VI: Voiding Cystourethrography and Cystography