Related Experiment Video
Updated: Dec 14, 2025
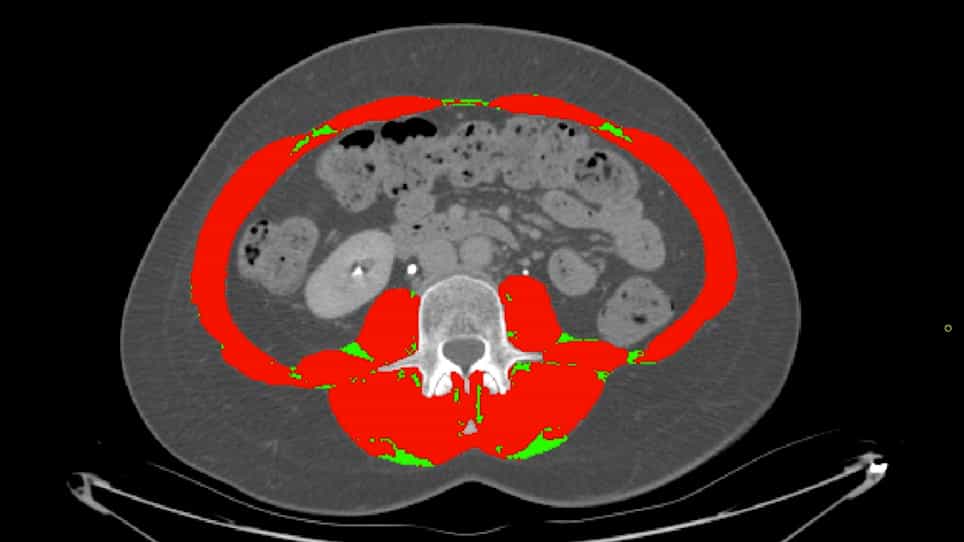
Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Worsening Disability and Hospitalization Risk in Sarcopenic Obese and Dynapenic Abdominal Obese: A 5.5 Years
Andrea P Rossi1, Silvia Urbani1, Francesco Fantin1
1Division of Geriatric, Department of Medicine, University of Verona, Verona, Italy.

Abstract:
Background/Objectives: A general lack of studies comparing the effect of both dynapenic abdominal obesity and sarcopenic obesity on worsening disability and hospitalization risk should be recognized. The aim of the current study was to evaluate, with a 5.5-year follow-up, the prognostic value of sarcopenic obesity and dynapenic abdominal obesity definitions on worsening disability and hospitalization risk in a sample of older adults. Subjects/Methods: In 177 women and 97 men aged 68-78 years, the following outcomes were evaluated at baseline: appendicular skeletal muscle mass (ASMM), percent fat mass (FM%), leg isometric strength, body mass index (BMI), lipid profile, vitamin D3, albumin, fibrinogen, glycemia, physical activity level, income, smoking status, and comorbidities. The rate of reported disabilities and hospitalization were also assessed at baseline, 1, 2, 3, and 5.5-years follow-up. The study population was classified into: (i) non-sarcopenic/obese (NS/O), sarcopenic/non-obese (S/NO), sarcopenic/obese (S/O), non-sarcopenic/non-obese (NS/NO, reference category) according to relative ASMM/FM% tertiles; (ii) non-dynapenic/abdominal obese (ND/AO), dynapenic/non-abdominal obese (D/NAO), dynapenic/abdominal obese (D/AO), non-dynapenic/non-abdominal obese (ND/NAO, reference category) according to muscle strength/waist circumference tertiles. Results: The prevalence of D/AO and S/O was 12.0 and 8.0%, respectively. Only 2 subjects were both D/NAO and S/O (0.8%). D/NAO subjects showed a worsening disability risk of 1.69 times (95% CI: 1.11-2.57), ND/AO subjects showed a 2-fold increased risk (95% CI: 1.34-2.98), while being D/AO more than trebled the risk, even after adjustment for confounding factors (HR: 3.39, 95%; CI: 1.91-6.02). By dividing the study population according to the relative ASMM/FM% tertiles, no groups showed an increased risk of worsening disability. The hospitalization risk, even after adjustment for potential confounders, was 1.84 (95% CI: 1.06-3.19) for D/AO. Dividing the study population according to the relative ASMM/FM% tertiles, no groups showed increased risk of hospitalization. Conclusions: Our results showed that dynapenic abdominal obesity and sarcopenic obesity seem to indicate two distinct phenotypes associated with different health risk profiles. The distribution of participants in waist circumference and muscle strength tertiles allowed for a more accurate risk stratification for worsening disability and hospitalization.
Related Concept Videos
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:21
Drug Dosing: Obese Patients
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...