Comparison of the effects of voluntary and involuntary breath stacking techniques on respiratory mechanics and lung function patterns in tracheostomized patients: a randomized crossover clinical trial
Related Experiment Video
Updated: Dec 14, 2025

Investigation into Deep Breathing through Measurement of Ventilatory Parameters and Observation of Breathing Patterns
Published on: September 16, 2019
Luciano Matos Chicayban1, Alice Campos Hemétrio2, Liz Tavares Rangel Azevedo2
1Laboratório de Pesquisa em Fisioterapia Pneumofuncional e Intensiva, Institutos Superiores de Ensino do Centro Educacional Nossa Senhora Auxiliadora, Campos dos Goytacazes, RJ, Brasil.

Objective:
To compare the effects of voluntary breath stacking (VBS) and involuntary breath stacking (IBS) techniques on respiratory mechanics, lung function patterns, and inspiratory capacity in tracheostomized patients.
Methods:
This was a randomized crossover clinical trial involving 20 tracheostomized patients admitted to the ICU and submitted to the VBS and IBS techniques, in random order, with an interval of 5 h between each. Ten cycles of each technique were performed with an interval of 30 s between each cycle. In VBS, patients performed successive inspirations for up to 30 s through a one-way valve, whereas in IBS, successive slow insufflations were performed with a resuscitator bag until the pressure reached 40 cmH2O. Respiratory mechanics, inspiratory capacity, and the lung function pattern were evaluated before and after the interventions.
Results:
After IBS, there was an increase in static compliance (p = 0.007), which was also higher after IBS than after VBS (p = 0.03). There was no significant difference between the pre-VBS and post-VBS evaluations in terms of static compliance (p = 0.42). Inspiratory capacity was also greater after IBS than after VBS (2,420.7 ± 480.9 mL vs. 1,211.3 ± 562.8 mL; p < 0.001), as was airway pressure (38.3 ± 2.6 cmH2O vs. 25.8 ± 5.5 cmH2O; p < 0.001). There were no changes in resistance or lung function pattern after the application of either technique.
Conclusions:
In comparison with VBS, IBS promoted greater inspiratory capacity and higher airway pressure, resulting in an increase in static compliance.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:15
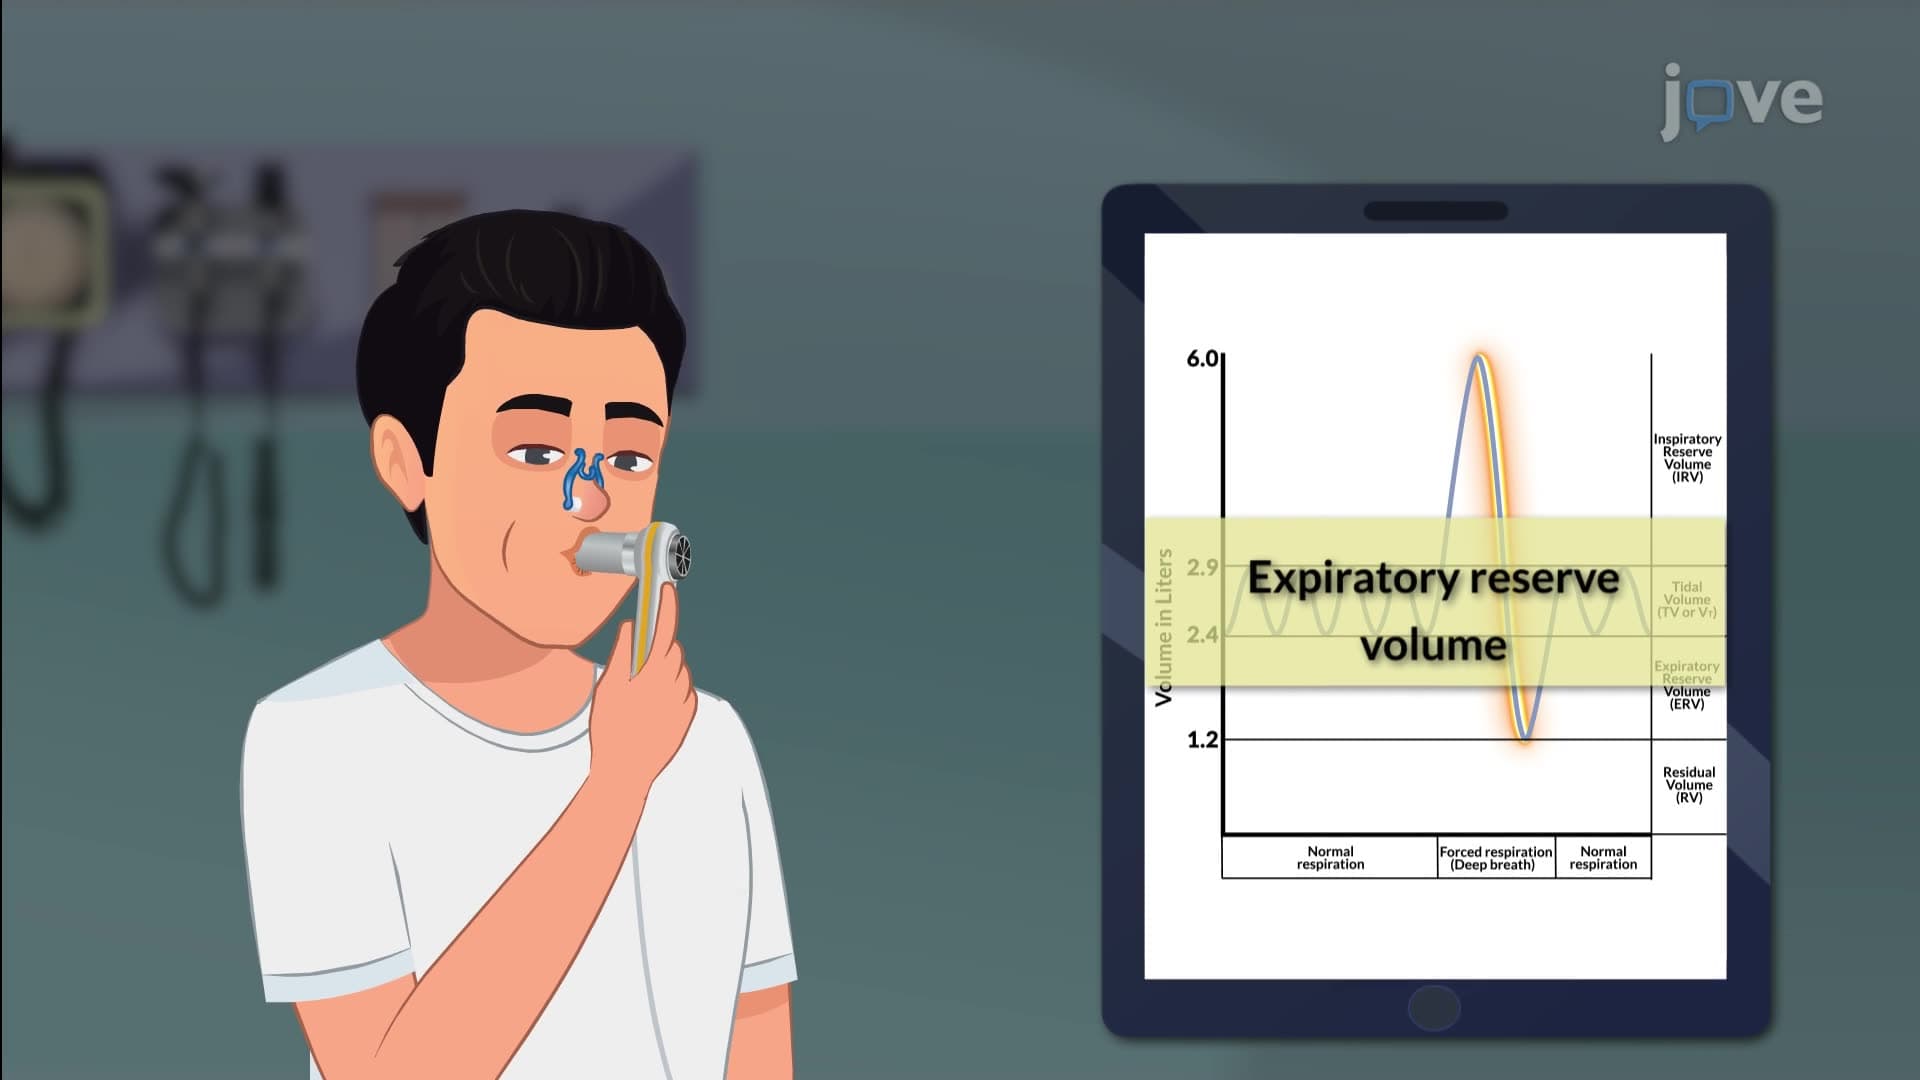
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:23
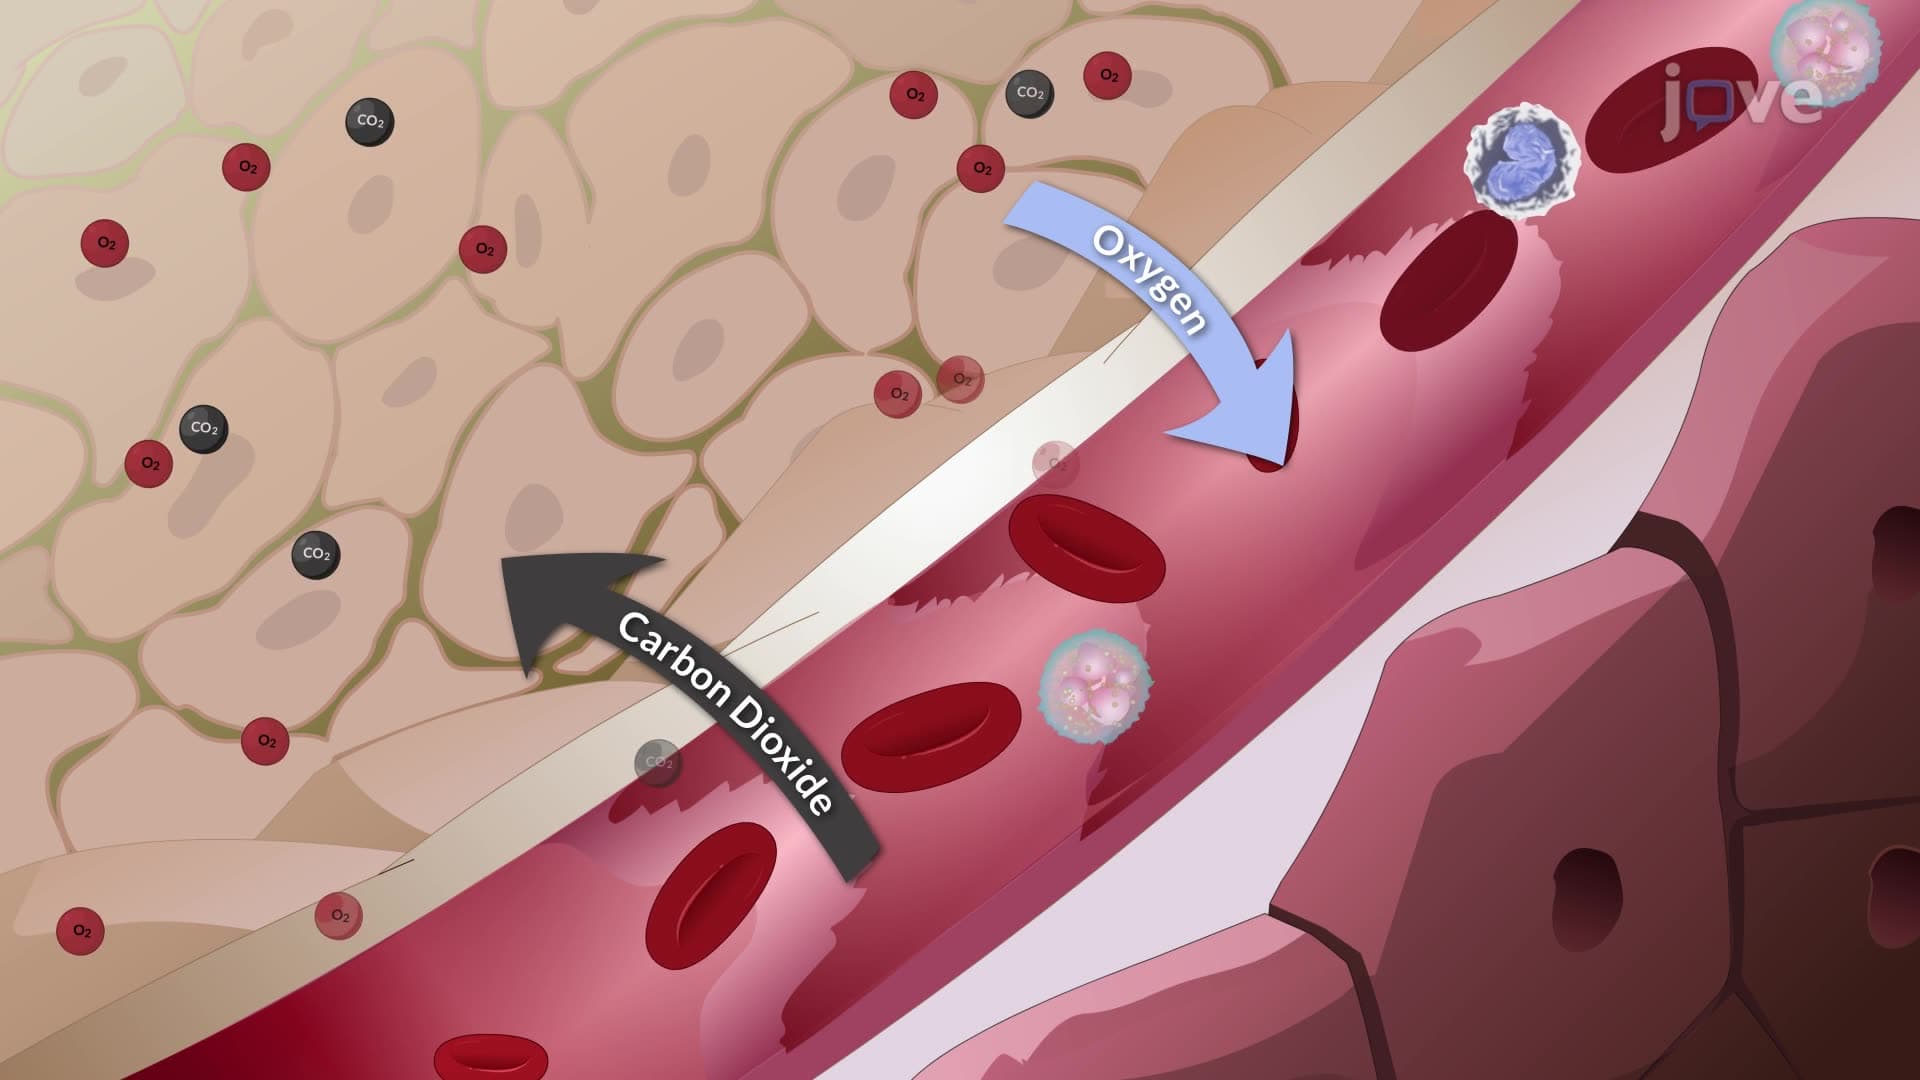
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:21
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...