Related Experiment Video
Updated: Dec 13, 2025
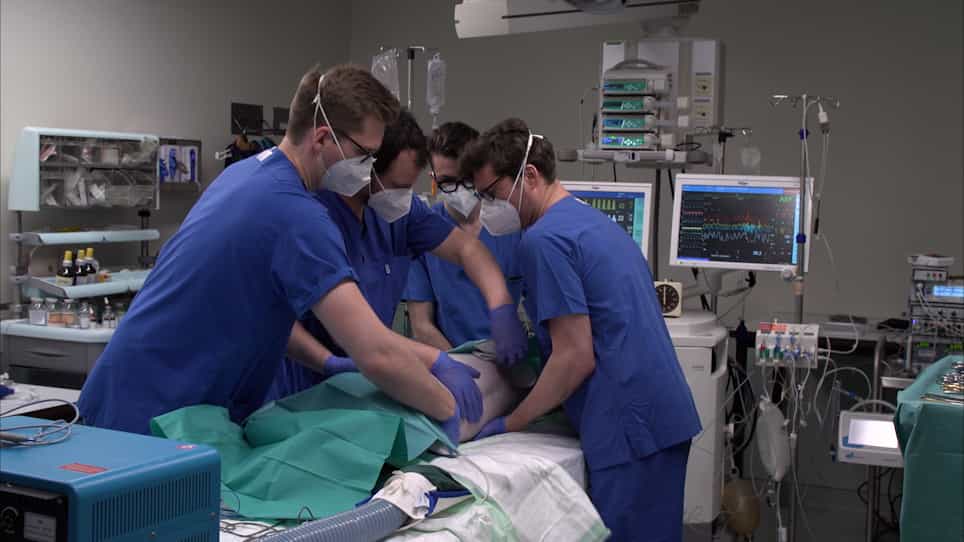
Real-Time Assessment of Spinal Cord Microperfusion in a Porcine Model of Ischemia/Reperfusion
Published on: December 10, 2020
The intraspinal arterial collateral network: a new anatomical basis for understanding and preventing paraplegia
Ulrike M Heber1,2, Marcel Mayrhofer1, Roman Gottardi3
1Center for Anatomy and Cell Biology, Division of Anatomy, MIC und CMI, Medical University of Vienna, Vienna, Austria.

Objectives:
The anatomical distribution pattern of epidural intraspinal arteries is not entirely understood but is likely to substantially impact maintaining perfusion during segmental artery sacrifice when treating acute and chronic thoraco-abdominal aortic diseases. We investigated the anatomical distribution pattern of intraspinal arteries.
Methods:
Twenty fresh, non-embalmed cadaveric human bodies were studied. Anatomical dissection and investigation of the epidural arterial network were performed according to a standardized protocol. We used a generalized mixed linear model to test whether the presence probability for certain vessels differed between vertebrae/segments.
Results:
There was craniocaudal continuity of all ipsilateral longitudinal connections from T1 to L5 by the anterior radicular artery. The mean [±standard deviation (SD)] number of transverse anastomoses was 9.7 ± 2.1. The presence probability of transverse anastomoses along the spine was different between vertebrae (P < 0.0001). There were 2 distribution peaks along the spine: 1 peak around T4-T6 and 1 around T11. The mean (±SD) number of thoracic and lumbar anterior radiculomedullary arteries (ARMAs) was 3.0 ± 1.1. The probability of the presence of ARMAs along the spine was different for each vertebral segment (P < 0.0001). Between ARMAs there were gaps of up to a maximum of 9 vertebrae. All Adamkiewicz arteries were located caudally to T7. The median segment of the Adamkiewicz presence was T10/11.
Conclusions:
The epidural collateral network shows craniocaudal continuity. The number of transverse anastomoses is high. The number of ARMAs is low, and there is considerable variation in their distribution and offspring, which is highly likely to impact perfusion during segmental artery sacrifice when treating thoraco-abdominal aortic disease.
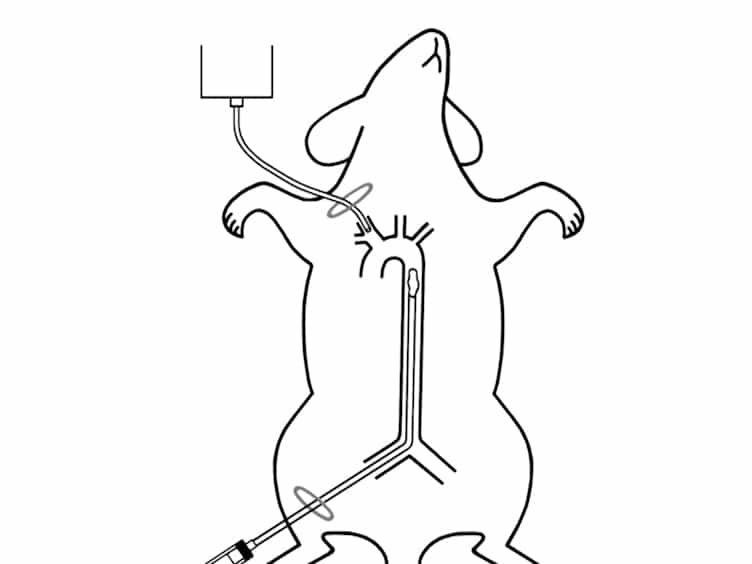

Related Concept Videos
 01:19
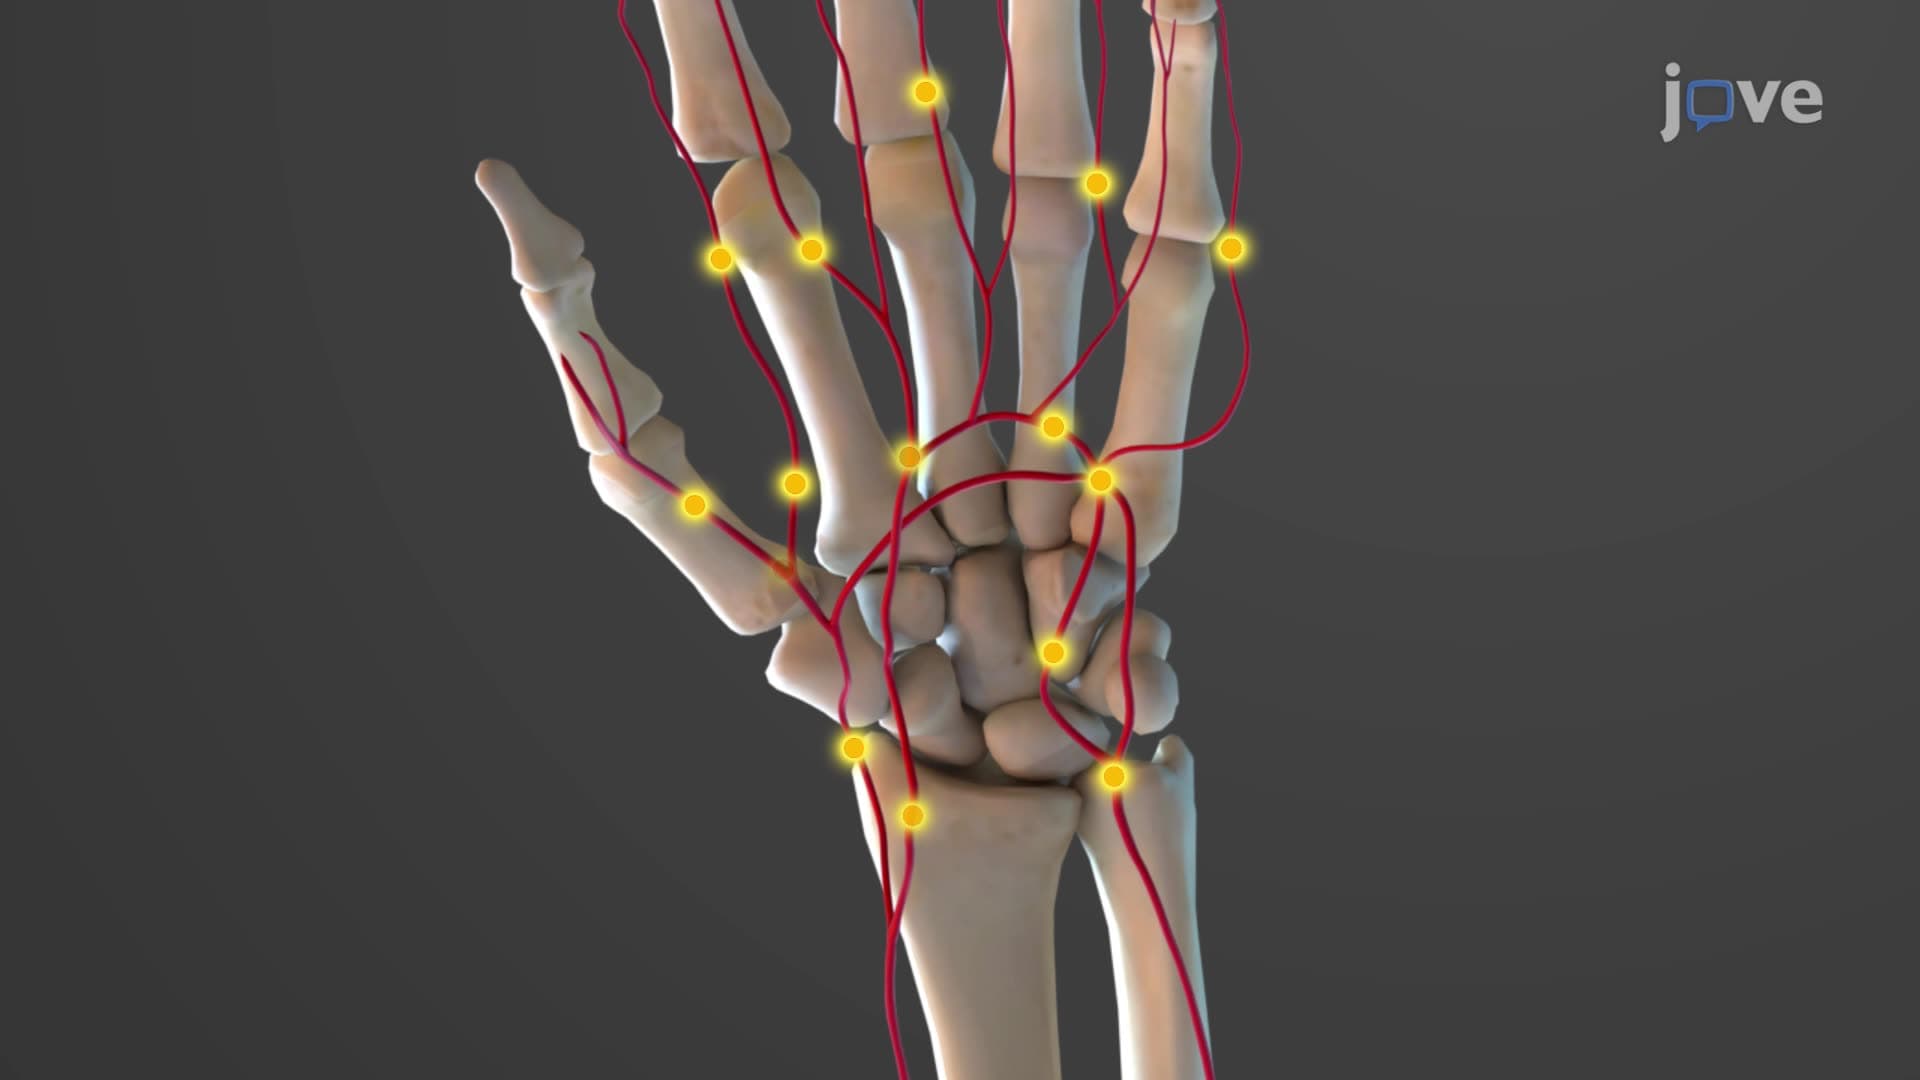
Anastomoses
Anastomoses can be formed at arterial, venous, and lymphatic vessels.
Arterial Anastomosis: These occur between arteries. They...
 01:22
Aneurysm IV: Nursing Management
 01:26
Aneurysm III: Interprofessional Care