Related Experiment Video
Updated: Dec 13, 2025
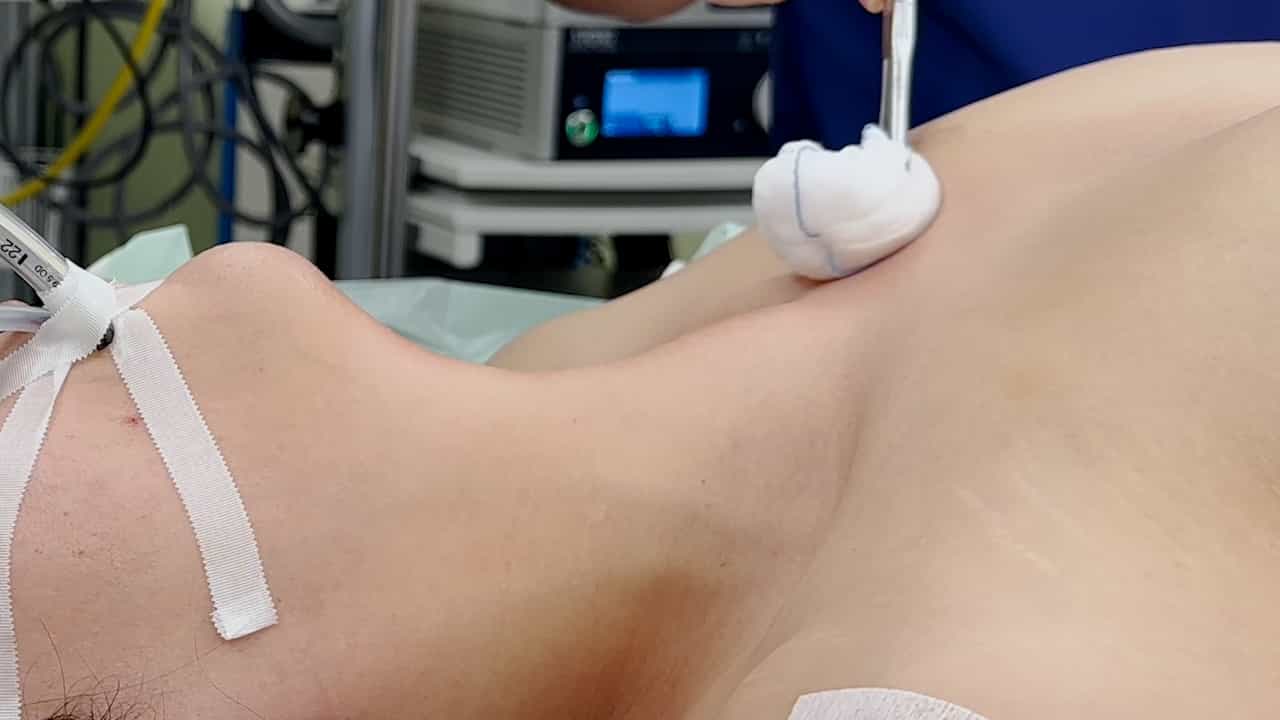

Minimal Invasive Resection of Large Retrosternal Thyroid Goiter
Published on: September 20, 2024
[Completion thyroidectomy after less than total resection for postoperatively diagnosed follicular thyroid cancer]
1Sektion Endokrine Chirurgie, Klinik für Allgemein‑, Viszeral- und Transplantationschirurgie, Universitätsklinikum Essen, Hufelandstr. 55, 45127, Essen, Deutschland. frank.weber@uk-essen.de.

Abstract:
As there are no reliable preoperative or intraoperative markers to identify follicular thyroid cancer (FTC), the postoperative histopathological diagnosis frequently raises the question of completion surgery. The oncological necessity must not be questioned by an allegedly increased morbidity. The operation is particularly indicated if there is evidence of distant or lymph node metastasis, the presence of a broadly invasive FTC, or evidence of extensive angioinvasion. Prophylactic lymphadenectomy is not indicated. There are no clear data that minimally invasive oncocytic FTC poses a special risk. Risk factors such as tumor size and age must be assessed as a biological continuum and require an individual assessment. Utilizing the technical options and thorough planning enables a completion thyroidectomy to be performed without increased risk.