Related Experiment Video
Updated: Dec 13, 2025


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Model-Informed Precision Dosing of Everolimus: External Validation in Adult Renal Transplant Recipients
Tom C Zwart1, Dirk Jan A R Moes2,3, Paul J M van der Boog4
1Department of Clinical Pharmacy and Toxicology, Leiden University Medical Center, Albinusdreef 2, 2333ZA, Leiden, The Netherlands. t.c.zwart@lumc.nl.

Background And Objective:
The immunosuppressant everolimus is increasingly applied in renal transplantation. Its extensive pharmacokinetic variability necessitates therapeutic drug monitoring, typically based on whole-blood trough concentrations (C0). Unfortunately, therapeutic drug monitoring target attainment rates are often unsatisfactory and patients with on-target exposure may still develop organ rejection. As everolimus displays erythrocyte partitioning, haematocrit-normalised whole-blood exposure has been suggested as a more informative therapeutic drug monitoring marker. Furthermore, model-informed precision dosing has introduced options for more sophisticated dose adaptation. We have previously developed a mechanistic population pharmacokinetic model, which described everolimus plasma pharmacokinetics and enabled estimation of haematocrit-normalised whole-blood exposure. Here, we externally evaluated this model for its utility for model-informed precision dosing.
Methods:
The retrospective dataset included 4123 pharmacokinetic observations from routine clinical therapeutic drug monitoring in 173 renal transplant recipients. Model appropriateness was confirmed with a visual predictive check. A fit-for-purpose analysis was conducted to evaluate whether the model accurately and precisely predicted a future C0 or area under the concentration-time curve (AUC) from prior pharmacokinetic observations. Bias and imprecision were expressed as the mean percentage prediction error (MPPE) and mean absolute percentage prediction error (MAPE), stratified on 6 months post-transplant. Additionally, we compared dose adaptation recommendations of conventional C0-based therapeutic drug monitoring and C0- or AUC-based model-informed precision dosing, and assessed the percentage of differences between observed and haematocrit-normalised C0 (∆C0) and AUC (∆AUC) exceeding ± 20%.
Results:
The model showed adequate accuracy and precision for C0 and AUC prediction at ≤ 6 months (MPPEC0: 8.1 ± 2.5%, MAPEC0: 26.8 ± 2.1%; MPPEAUC: - 9.7 ± 5.1%, MAPEAUC: 13.3 ± 3.9%) and > 6 months post-transplant (MPPEC0: 4.7 ± 2.0%, MAPEC0: 25.4 ± 1.4%; MPPEAUC: - 0.13 ± 4.8%, MAPEAUC: 13.3 ± 2.8%). On average, dose adaptation recommendations derived from C0-based and AUC-based model-informed precision dosing were 2.91 ± 0.01% and 13.7 ± 0.18% lower than for conventional C0-based therapeutic drug monitoring at ≤ 6 months, and 0.93 ± 0.01% and 3.14 ± 0.04% lower at > 6 months post-transplant. The ∆C0 and ∆AUC exceeded ± 20% on 13.6% and 14.3% of occasions, respectively.
Conclusions:
We demonstrated that our population pharmacokinetic model was able to accurately and precisely predict future everolimus exposure from prior pharmacokinetic measurements. In addition, we illustrated the potential added value of performing everolimus therapeutic drug monitoring with haematocrit-normalised whole-blood concentrations. Our results provide reassurance to implement this methodology in clinical practice for further evaluation.


Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:15
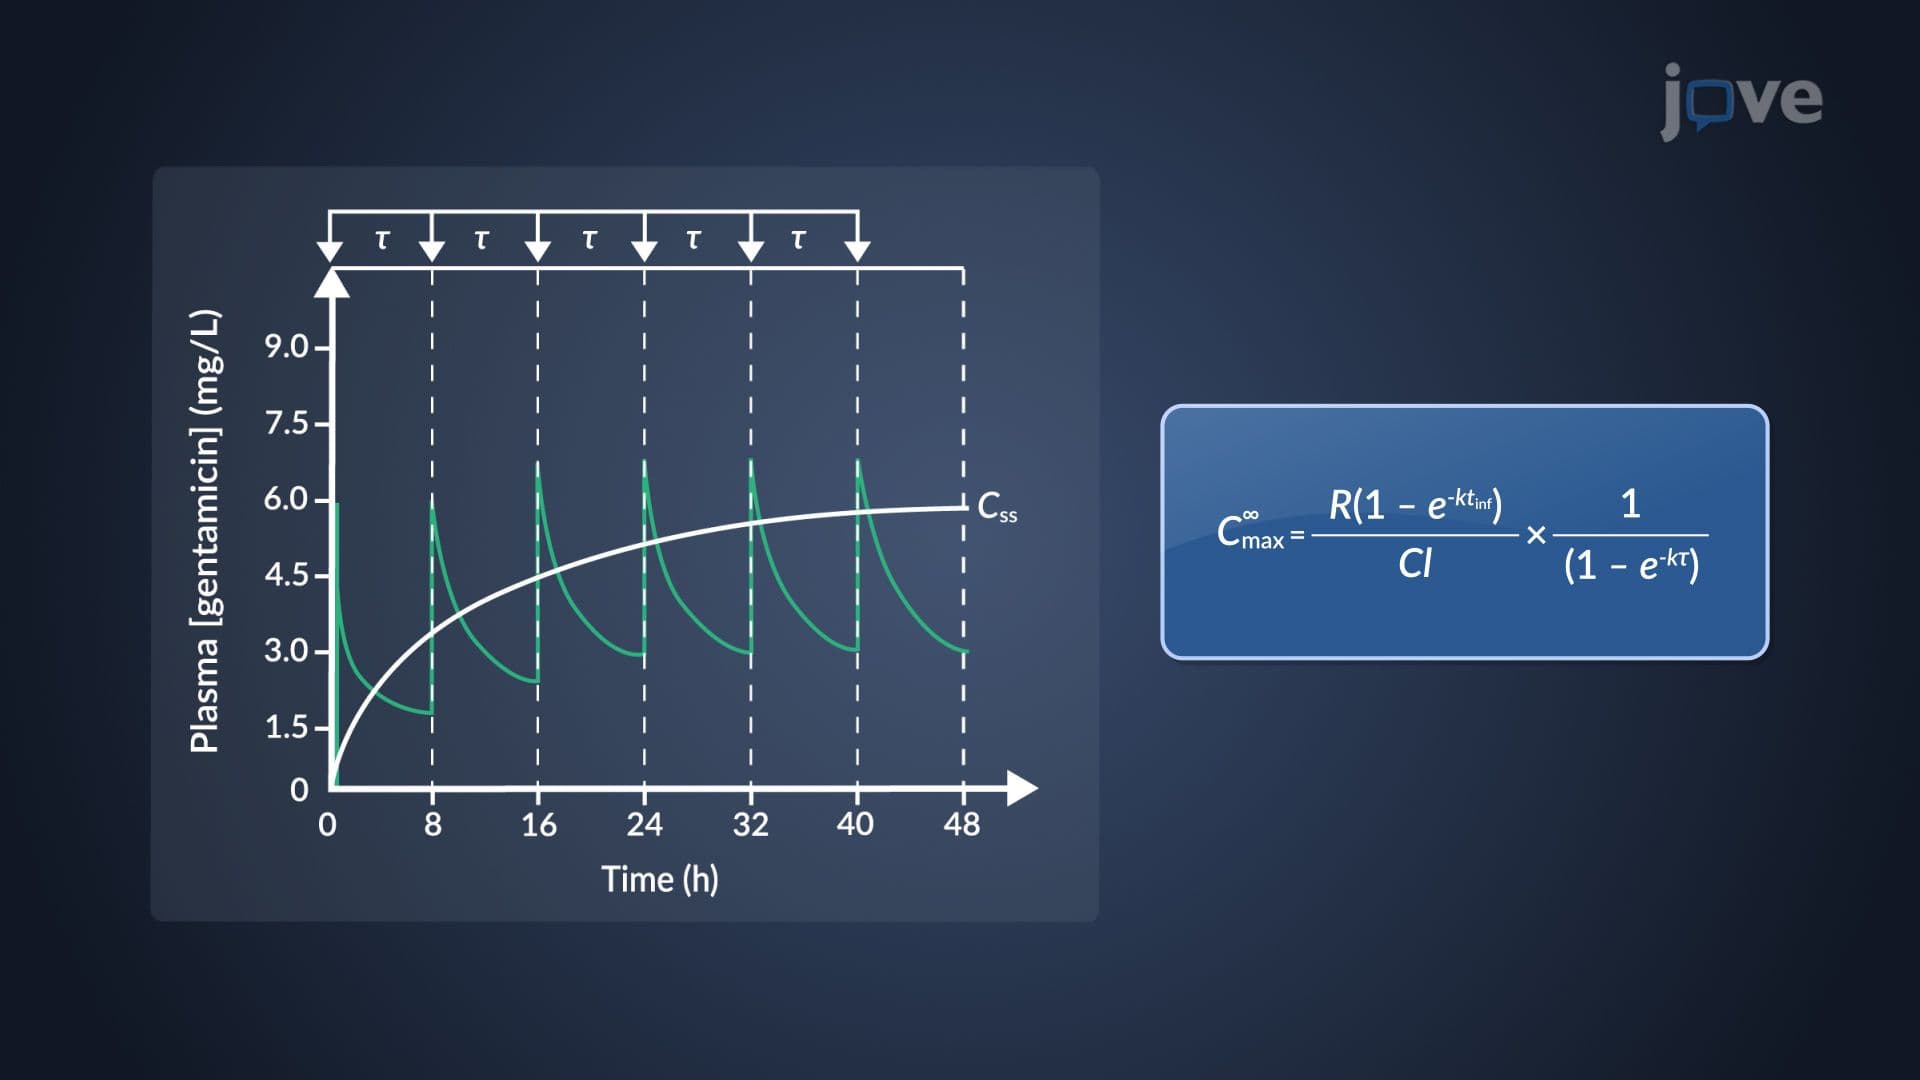
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:08
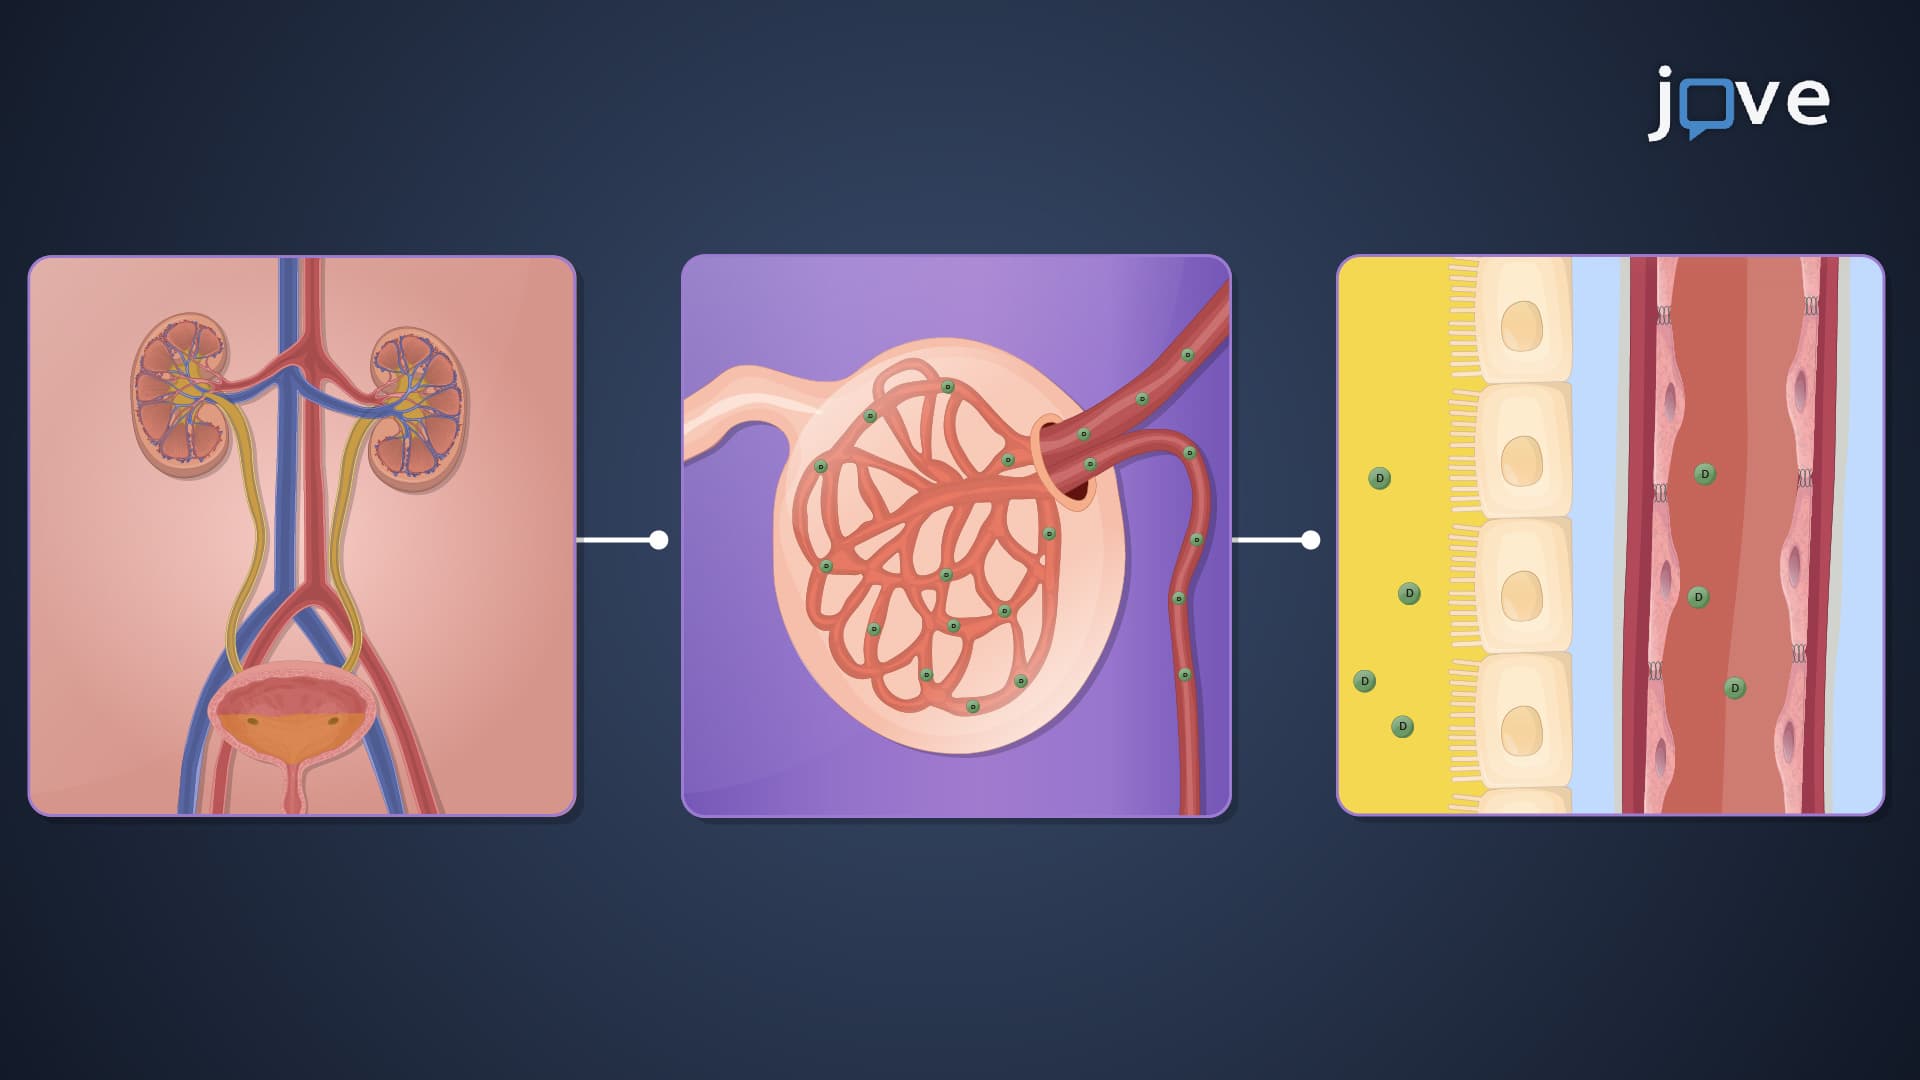
Renal Drug Clearance: Comparison Between Renal Excretion Methods
Renal clearance is often associated with the renal glomerular filtration rate (GFR), which represents the rate at which plasma is filtered through the glomeruli in the kidney. When drug reabsorption is minimal and there is no active secretion, renal clearance is closely related to the...