Related Experiment Video
Updated: Dec 13, 2025

Ischemia-reperfusion Model of Acute Kidney Injury and Post Injury Fibrosis in Mice
Published on: August 9, 2013
Spot urinary citrate-to-creatinine ratio is a marker for acid-base status in chronic kidney disease
Fabiola G Gianella1, Victor E Prado1, John R Poindexter2
1Charles and Jane Pak Center for Mineral Metabolism and Clinical Research, University of Texas Southwestern Medical Center, Dallas, Texas, USA; Department of Internal Medicine, University of Texas Southwestern Medical Center, Dallas, Texas, USA.

Abstract:
Due to multiple compensating mechanisms, the serum bicarbonate concentration is a relatively insensitive marker of acid-base status; especially in chronic kidney disease (CKD). This is a major drawback that impairs the ability to diagnose acid excess or monitor alkali therapy. We postulated that it is more logical to measure the compensatory defense mechanism(s) rather than the defended parameter, which remains normal if the compensation is successful. Therefore, a retrospective cross-sectional study was performed in 1733 stone formers along with a prospective cross-sectional study of 22 individuals with normal kidney function and 50 patients in different stages of CKD. While serum bicarbonate was flat and did not fall below the reference range until near CKD stage 5, citrate excretion (24-hour urinary citrate excretion rate; urinary citrate-to-creatinine ratio, in the retrospective analysis, and spot urinary citrate-to-creatinine ratio in the prospective study) progressively and significantly declined starting from CKD stage 2. Following an acute acid load in 25 participants with a wide range of estimated glomerular filtration rates, the urinary citrate-to-creatinine ratio inversely and significantly associated with acid accumulation, whereas serum bicarbonate did not. We compared changes in serum bicarbonate and urinary citrate-to-creatinine ratio in response to alkali therapy in patients with CKD stage 3 or 4 started on potassium citrate in our kidney stone database. With alkali therapy, there was no change in serum bicarbonate, but the urinary citrate-to-creatinine ratio rose consistently in all patients adherent to potassium citrate therapy. Thus, the urinary citrate-to-creatinine ratio (the defense mechanism) is a potential easily implementable, pragmatic, and a superior parameter to serum bicarbonate (the defended entity) to assess acid-base status, and monitor alkali therapy. Additional studies are needed before a clinical test can be devised.

Related Concept Videos
 01:24
Serum Studies: Renal Function Tests
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:29
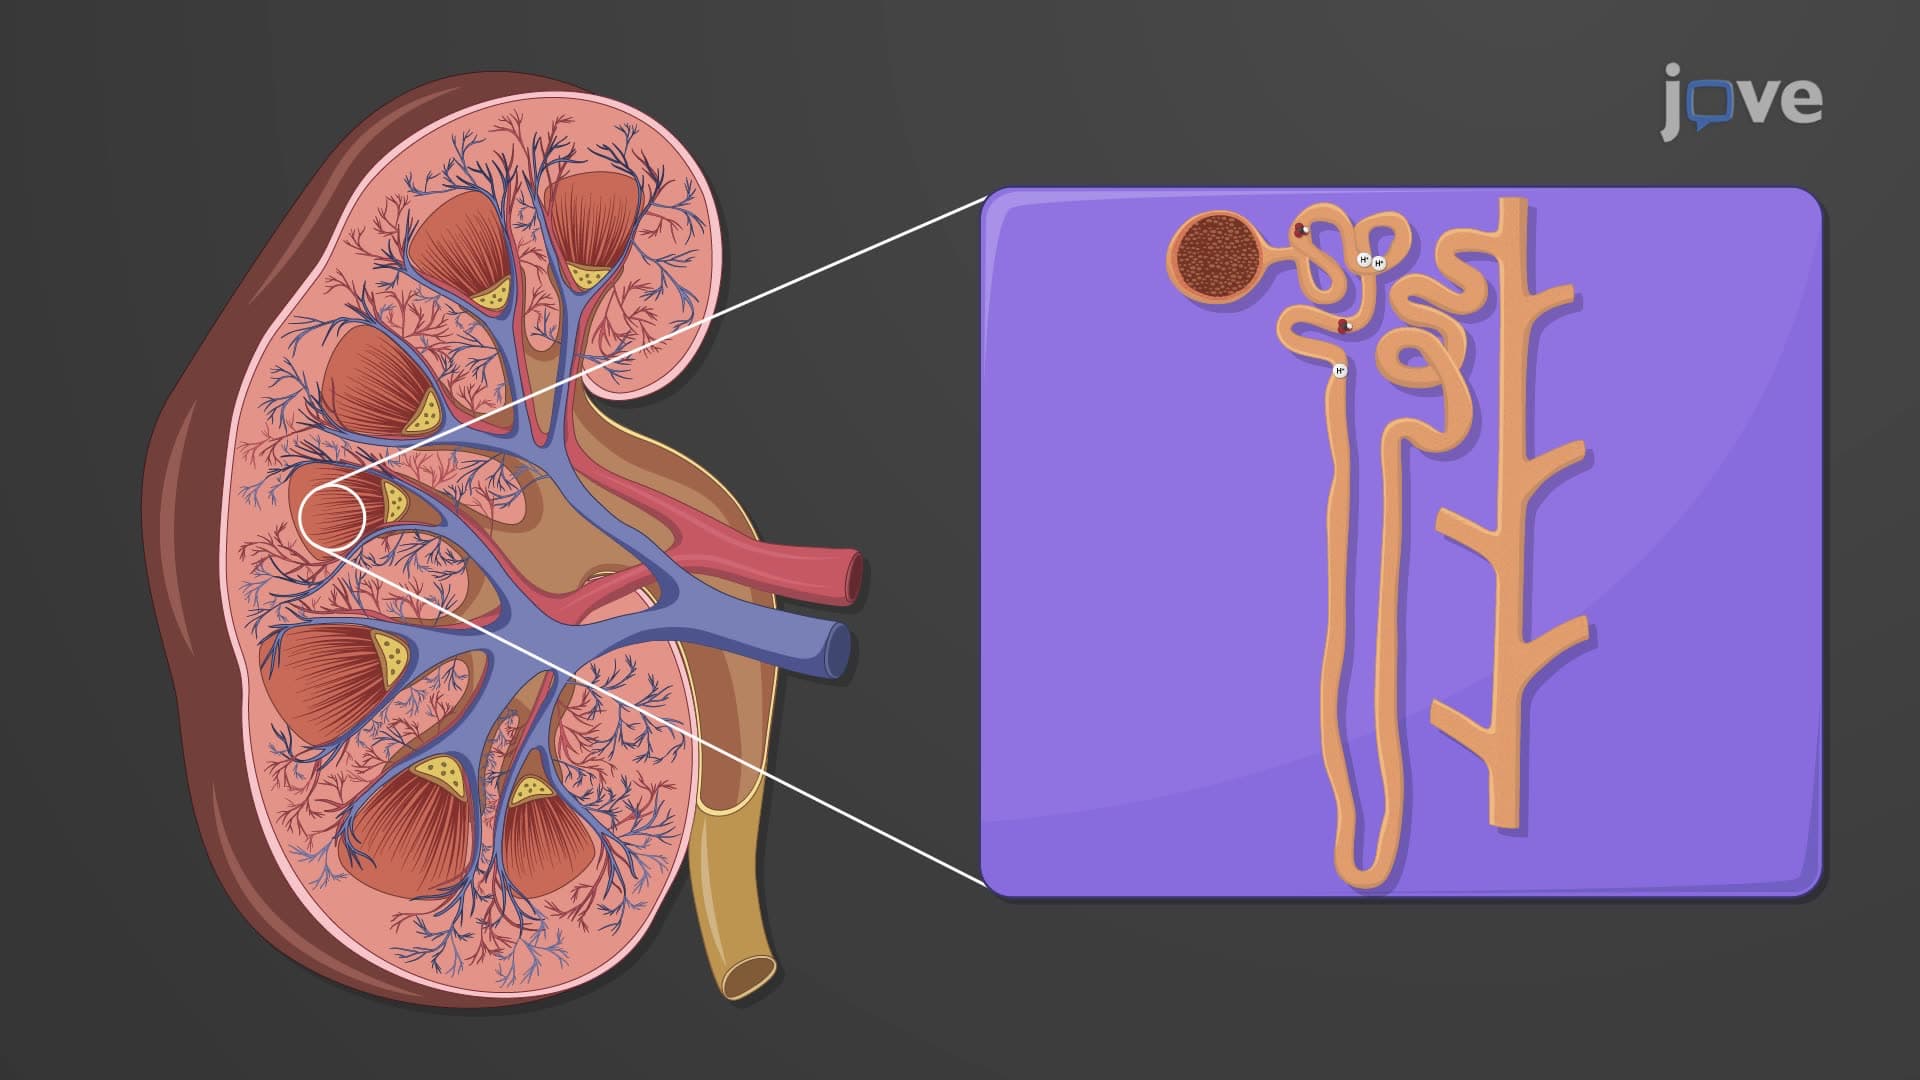
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:23
Renal Clearance
Renal clearance refers to the volume of plasma cleared of a specific substance, such as creatinine, per unit of time. To measure clearance, urine samples are collected over a 24-hour period during each bladder voiding, followed by a single blood sample at the...