Related Experiment Video
Updated: Dec 13, 2025


Author Spotlight: Advancements in Multiplex Detection of Respiratory Viruses
Published on: November 10, 2023
[Clinical characteristics and death risk factors of severe COVID-19]
1Department of Pulmonary and Critical Care Medicine,Affiliated Hospital of Jianghan University, Wuhan 430015,China.

Insights
Severe COVID-19 patients often present with fever, cough, and fatigue. Higher D-dimer, elevated NT-proBNP, and lower lymphocyte counts are key risk factors for mortality in these patients.
Area of Science:
- Infectious Diseases
- Critical Care Medicine
- Clinical Pathology
Background:
- COVID-19, caused by SARS-CoV-2, can lead to severe respiratory illness.
- Understanding clinical features and mortality predictors is crucial for patient management.
Purpose of the Study:
- To analyze clinical characteristics of severe COVID-19 cases.
- To identify independent risk factors associated with death in severe COVID-19 patients.
Main Methods:
- Retrospective analysis of 891 COVID-19 patients, focusing on 582 severe/critical cases.
- Demographic, clinical, laboratory, and imaging data were collected.
- Multivariate logistic regression was used to determine risk factors for mortality.
Main Results:
- Common symptoms included fever (79%), dry cough (62%), and fatigue (47%).
- Hypertension (33%) was the most frequent comorbidity.
- Increased D-dimer (OR: 1.095), increased NT-proBNP (OR: 4.759), and decreased lymphocyte count (OR: 0.180) were significant risk factors for death.
Conclusions:
- Severe COVID-19 patients exhibit common symptoms and comorbidities.
- Elevated D-dimer, NT-proBNP, and low lymphocyte counts are independent predictors of mortality in severe COVID-19.
Abstract:
Objective: To analyze the clinical features and death-related risk factors of COVID-19. Methods: We enrolled 891 COVID-19 patients admitted to the Affiliated Hospital of Jianghan University from December 2019 to February 2020, including 427 men and 464 women. Of the 891 cases, 582 were severe or critical, including 423(73%)severe and 159 (27%) critical cases. We compared the demographics, laboratory findings, clinical characteristics, treatments and prognosis data of the 582 severe patients. Univariate and multivariate logistic regression analysis was conducted to explore the risk factors associated with death in COVID-19 patients. Results: The 582 severe patients included 293 males and 289 females, with a median age of 64(range 24 to 106). Sixty-three patients died, including 45 males and 18 females, with a median age of 71(range 37 to 90). The average onset time of the 582 patients was 8 days, of whom 461 (79%) had fever, 358 (62%) dry cough, 274 (47%) fatigue. There were 206 cases with shortness of breath (35%), 155 cases with expectoration (27%), 83 cases with muscle pain or joint pain (14%), 71 cases with diarrhea (12%), and 29 cases with headache (4%). Underlying diseases were present in 267 (46%) patients, most commonly hypertension (194, 33%), followed by diabetes (69, 12%), coronary atherosclerotic heart disease (37, 6%), tumor (18, 3%), and chronic obstructive pulmonary disease (5, 1%). Chest CT showed bilateral lung involvement in 505 patients (87%). Upon admission, the median lymphocyte count of the 582 patients was 0.8(IQR, 0.6-1.1)×10(9)/L, the median D-dimer was 0.5 (IQR, 0.4- 0.8) mg/L, the median N-terminal brain natriuretic peptide precursor (NT-proBNP) was 433 (IQR, 141- 806) pg/L, and the median creatinine was 70.3 (IQR, 56.9-87.9) μmol/L. The death group had a median lymphocyte count of 0.5 (0.4-0.8)×10(9)/L, D-dimer 1.1 (0.7-10.0)mg/L, N-terminal brain natriuretic peptide precursor 1479(893-5 087) pg/ml, and creatinine 89.9(67.1-125.3) μmol/L. Multivariate logistic analysis showed that increased D-dimer (OR: 1.095, 95% CI: 1.045-1.148, P<0.001), increased NT-proBNP (OR: 4.759, 95% CI: 2.437-9.291, P<0.001), and decreased lymphocyte count (OR: 0.180, 95% CI: 0.059-0.550, P=0.003) were the risk factors of death in COVID-19 patients. Conclusions: The average onset time of severe COVID-19 was 8 days, and the most common symptoms were fever, dry cough and fatigue. Comorbidities such as hypertension were common and mostly accompanied by impaired organ functions on admission. Higher D-dimer, higher NT-proBNP, and lower lymphocyte count were the independent risk factors of death in COVID-19 patients.
More Related Videos
 08:05
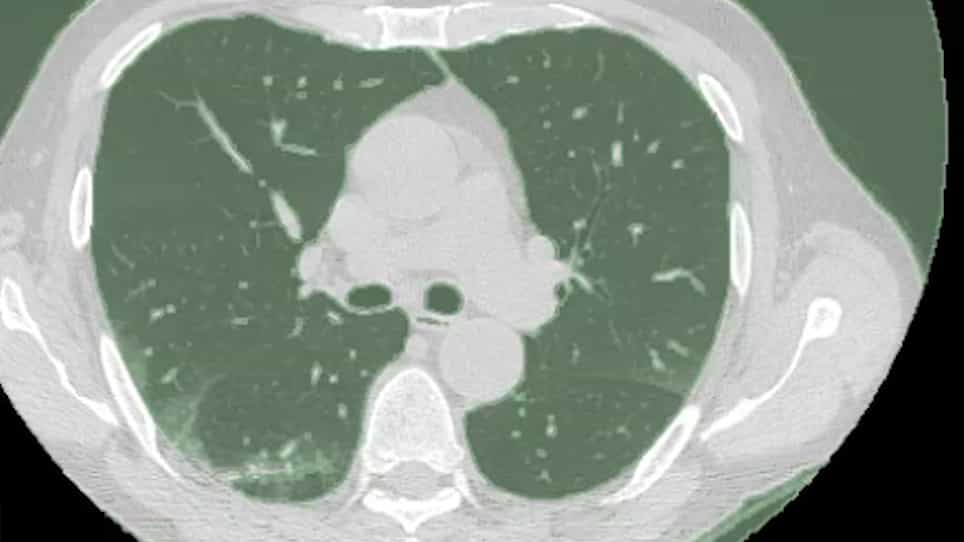
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
 08:41
Live Imaging and Quantification of Viral Infection in K18 hACE2 Transgenic Mice Using Reporter-Expressing Recombinant SARS-CoV-2
Published on: November 5, 2021
Related Concept Videos
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:30
Pneumonia III: Complications and Assessment
 01:30
Coronary Artery Disease III: Clinical Manifestations
 01:29
Pneumonia II: Pathophysiology
 01:30
Acute Respiratory Failure-III
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...