Related Experiment Video
Updated: Dec 13, 2025
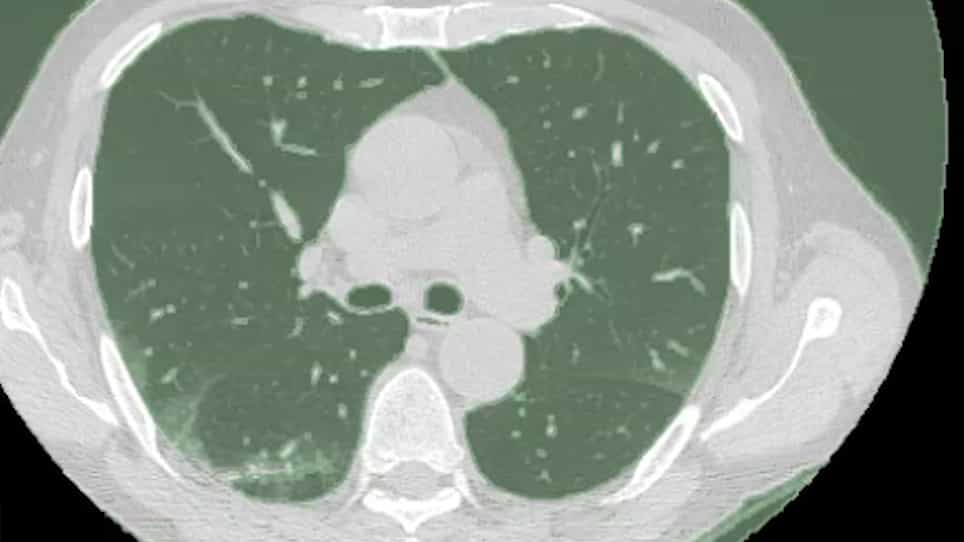

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
[Clinical characteristics and outcome of 64 patients with severe COVID-19]
1Department of Tuberculosis, Wuhan Pulmonary Hospital, Wuhan 430030, China.

Insights
Severe COVID-19 patients often died from acute respiratory distress syndrome (ARDS) due to pneumonia or heart failure and atrial fibrillation from viral myocarditis. Early intervention for myocardial injury is crucial for reducing mortality.
Area of Science:
- Critical Care Medicine
- Infectious Diseases
- Cardiology
Background:
- Severe COVID-19 poses significant mortality risks.
- Understanding the specific causes of death is crucial for developing effective treatments.
- Underlying comorbidities are prevalent in severe COVID-19 cases.
Purpose of the Study:
- To investigate the primary causes of mortality in patients with severe COVID-19.
- To compare clinical characteristics between non-survivors and survivors of severe COVID-19.
- To identify key laboratory and clinical indicators associated with fatal outcomes.
Main Methods:
- Retrospective analysis of 64 severe COVID-19 patients admitted to Wuhan Pulmonary Hospital.
- Comparison of clinical data, laboratory results, imaging features, and treatments between death and survival groups.
- Statistical analysis using independent t-tests, Mann Whitney tests, chi-squared tests, and Fisher exact tests.
Main Results:
- Elevated levels of creatine kinase isozyme (CK-MB), cardiac troponin I (cTnI), myoglobin, D-dimer, lactate dehydrogenase (LDH), and alanine aminotransferase were observed in the death group.
- Significantly higher incidence of abnormal electrocardiograms (ECG) in the non-survivor group (62% vs. 29%).
- Primary causes of death included severe pneumonia with acute respiratory distress syndrome (ARDS), acute heart failure, atrial fibrillation, and multiple organ dysfunction syndrome (MODS).
Conclusions:
- Severe pneumonia leading to ARDS and acute viral myocarditis causing heart failure and atrial fibrillation are major drivers of mortality in severe COVID-19.
- Myocardial injury markers and ECG abnormalities are associated with increased risk of death.
- Early prevention of myocardial damage and timely treatment of viral myocarditis are vital for improving outcomes in severe COVID-19 patients.
Abstract:
Objective: To investigate the causes of death in patients with severe COVID-19. Methods: A retrospective analysis was performed on 64 patients with severe COVID-19 admitted to Wuhan Pulmonary Hospital from January 12, 2020 to February 28, 2020. There were 36 males and 28 females, aging from 44 to 85 years[median 68 (62, 72)]. Fifty-two patients (81%) had underlying comorbidities. The patients were divided into the death group (n=40) and the survival group (n=24) according to the treatment outcomes. In the death group, 24 were male, and 16 were female, aging from 49 to 85 years [median 69 (62, 72)], with 31 cases (78%) complicated with underlying diseases. In the survival group, there were 12 males and 12 females, aging from 44 to 82 years[median 66 (61,73)], with 21 cases (88%) with comorbidities. Clinical data of the two groups were collected and compared, including general information, laboratory examinations, imaging features and treatments. For normally distributed data, independent group t test was used; otherwise, Mann Whitney test was used to compare the variables. χ(2) test and Fisher exact test was used when analyzing categorical variables. Results: The median of creatine kinase isozyme (CK-MB) in the death group was 19.0 (17.0,23.0) U/L, which was higher than that in the survival group 16.5 (13.5,19.6) U/L. The median level of cTnI in the death group was 0.03 (0.03, 0.07) μg/L, which was significantly higher than that in the survival group (0.02, 0.03) μg/L, with a statistically significant difference between the two groups (P=0.007). The concentration of myoglobin in the death group was 79.5 (28.7, 189.0) μg/L, which was higher than 33.1 (25.7, 54.5) μg/L in the survival group. The level of D-dimer in the death group was 2.0 (0.6, 5.2) mg/L, which was higher than 0.7 (0.4, 2.0) mg/L in the survival group. The LDH level of the death group was 465.0 (337.5,606.5) U/L, which was higher than that of the survibal group, 341.0 (284.0,430.0) U/L, the difference being statistically significant (P=0.006). The concentration of alanine aminotransferase in the death group was 40.0 (30.0, 48.0) U/L, which was higher than 32.5 (24.0, 40.8) U/L in the survival group, and the difference was statistically significant (P=0.047).Abnormal ECG was found in 16 cases (62%) in the death group, which was significantly higher than that in the survival group (29%), the difference being statistically significant (P=0.024) .The main causes of death were severe pneumonia with acute respiratory distress syndrome (ARDS, n=20), acute heart failure(n=9), atrial fibrillation(n=3) and multiple organ dysfunction syndrome (MODS, n=3). Conclusions: ARDS caused by severe pneumonia and acute heart failure and atrial fibrillation caused by acute viral myocarditis were the main causes of death in severe COVID-19 patients. Early prevention of myocardial injury and treatment of acute viral myocarditis complicated with disease progression may provide insights into treatment and reduction of mortality in patients with severe COVID-19.


Related Concept Videos
 01:30
Pneumonia III: Complications and Assessment
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:23
Acute Respiratory Failure-IV
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...