Related Experiment Video
Updated: Dec 13, 2025
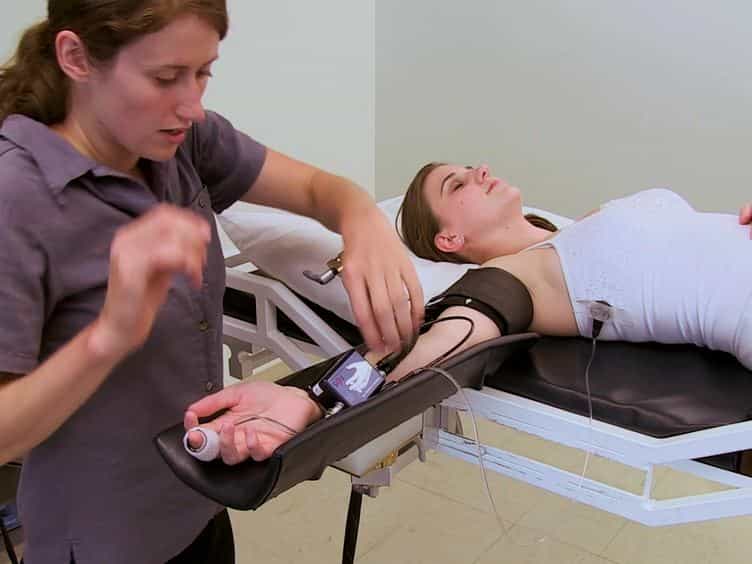
Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Orthostatic hypotension, dizziness, neurology outcomes, and death in older adults
Stephen P Juraschek1, W T Longstreth2, Oscar L Lopez2
1From the Department of Medicine (S.P.J., L.A.L., K.J.M.), Beth Israel Deaconess Medical Center, Boston, MA; Departments of Neurology and Epidemiology (W.T.L.), University of Washington, Seattle; Department of Neurology (O.L.L.) and Department of Epidemiology, Graduate School of Public Health (L.H.K.), University of Pittsburgh, PA; Department of Medicine (J.S.G.), University of Maryland, Baltimore; and Hinda and Arthur Marcus Institute for Aging Research (L.A.L.), Hebrew SeniorLife, Roslindale, MA. sjurasch@bidmc.harvard.edu.

Objective:
To test the hypothesis that orthostatic hypotension (OH) might cause cerebral hypoperfusion and injury, we examined the longitudinal relationship between OH or orthostatic symptoms and incident neurologic outcomes in a community population of older adults.
Methods:
Cardiovascular Health Study participants (≥65 years) without dementia or stroke had blood pressure (BP) measured after lying down for 20 minutes and after standing 3 for minutes. Participants reported dizziness immediately upon standing and any dizziness in the past 2 weeks. OH was defined as a drop in standing systolic/diastolic BP ≥20/≥10 mm Hg. We determined the association between OH or dizziness with (1) MRI brain findings (ventricular size, white matter hyperintensities, brain infarcts) using linear or logistic regression, (2) cognitive function (baseline and over time) using generalized estimating equations, and (3) prospective adjudicated events (dementia, stroke, death) using Cox models. Models were adjusted for demographic characteristics and OH risk factors. We used multiple imputation to account for missing OH or dizziness (n = 534).
Results:
Prior to imputation, there were 5,007 participants (mean age 72.7 ± 5.5 years, 57.6% women, 10.9% Black, 16% with OH). OH was modestly associated with death (hazard ratio [HR] 1.11; 95% confidence interval 1.02-1.20), but not MRI findings, cognition, dementia, or stroke. In contrast, dizziness upon standing was associated with lower baseline cognition (β = -1.20; -1.94 to -0.47), incident dementia (HR 1.32; 1.04-1.62), incident stroke (HR 1.22; 1.06-1.41), and death (HR 1.13; 1.06-1.21). Similarly, dizziness over the past 2 weeks was associated with higher white matter grade (β = 0.16; 0.03-0.30), brain infarcts (OR 1.31; 1.06-1.63), lower baseline cognition (β = -1.18; -2.01 to -0.34), and death (HR 1.13; 1.04-1.22).
Conclusions:
Dizziness was more consistently associated with neurologic outcomes than OH 3 minutes after standing. Delayed OH assessments may miss pathologic information related to cerebral injury.


Related Concept Videos
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart...
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:15
Drug Dosing: Geriatric Patients
 01:00
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Distribution
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Metabolism