Related Experiment Video
Updated: Dec 13, 2025


Non-invasive Assessment of Microvascular and Endothelial Function
Published on: January 29, 2013
AHA/ACC-defined stage 1 hypertensive adults do not display cutaneous microvascular endothelial dysfunction
Gabrielle A Dillon1, Jody L Greaney1,2, Sean Shank1
1Noll Laboratory, Department of Kinesiology, The Pennsylvania State University, University Park, Pennsylvania.

Insights
Stage 1 hypertension (HTN1) does not show impaired nitric oxide-mediated dilation, unlike stage 2 hypertension (HTN2). However, reduced endothelium-dependent dilation occurs in adults with hypertension who do not experience a nighttime blood pressure dip.
Area of Science:
- Cardiovascular Science
- Hypertension Research
- Endothelial Function Studies
Background:
- The 2017 AHA/ACC guidelines redefined stage 1 hypertension, but its impact on microvascular endothelial dysfunction is unclear.
- Endothelial dysfunction, particularly nitric oxide (NO)-dependent dilation, is a key factor in hypertension pathogenesis.
- Assessing endothelial function across hypertension stages is crucial for understanding disease progression.
Purpose of the Study:
- To determine if cutaneous microvascular endothelial dysfunction is present in stage 1 hypertension (HTN1) compared to normotensive adults (NTN).
- To compare the severity of endothelial dysfunction in HTN1 and stage 2 hypertension (HTN2).
- To investigate if impairments in NO-dependent dilation mediate this graded dysfunction.
Main Methods:
- Retrospective analysis of 20 NTN, 22 HTN1, and 44 HTN2 adults.
- 24-h ambulatory blood pressure monitoring to assess BP and nocturnal dipping status.
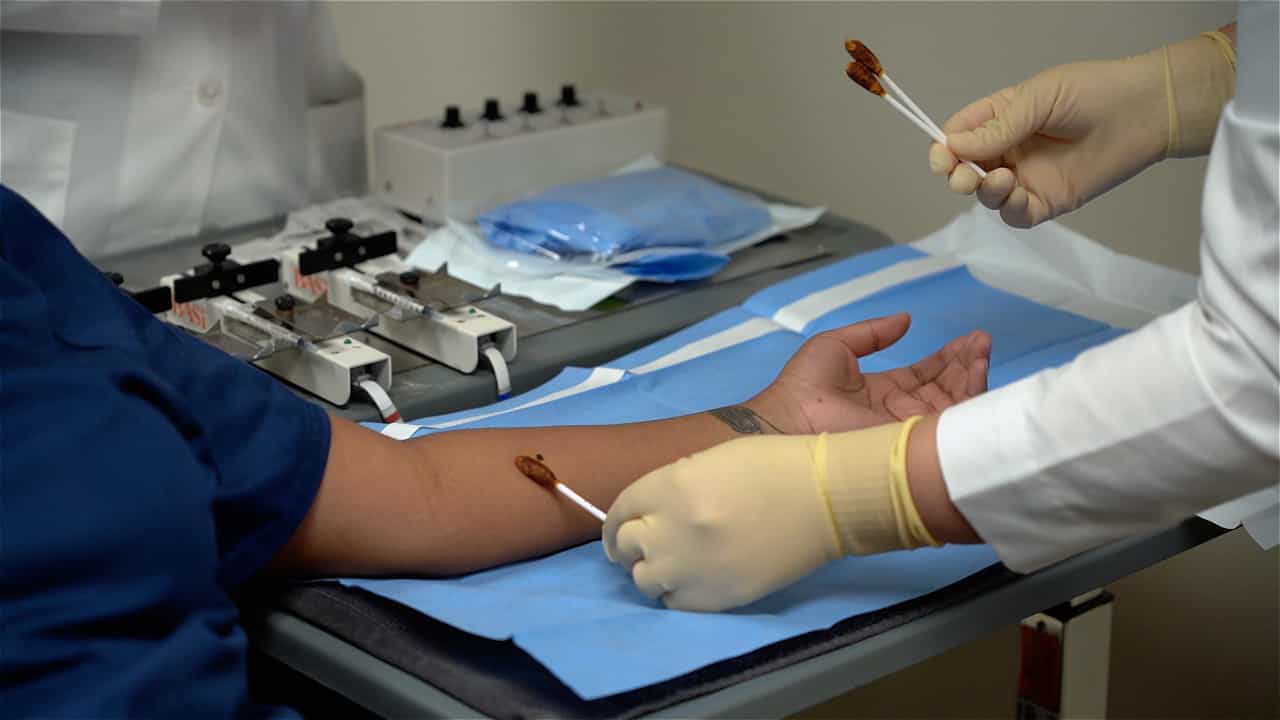
- Laser Doppler flowmetry during microdialysis with acetylcholine (ACh) and L-NAME to measure NO-dependent dilation.
Main Results:
- ACh-induced vasodilation was impaired in HTN2 (P < 0.01) but not HTN1 (P = 0.85) compared to NTN.
- Reductions in NO-dependent dilation were observed in HTN2 (P < 0.01) but not HTN1 (P = 0.76).
- Endothelium-dependent dilation was impaired in non-dippers, irrespective of hypertension classification (P < 0.05).
Conclusions:
- Functional impairments in NO-mediated endothelium-dependent dilation are not evident in stage 1 hypertension.
- Lack of nocturnal blood pressure dipping is associated with blunted endothelium-dependent dilation, regardless of hypertension stage.
- This study provides the first pharmacological assessment of endothelial function in adults classified by 2017 AHA/ACC hypertension guidelines.
Abstract:
In 2017, the American Heart Association (AHA) and American College of Cardiology (ACC) redefined stage 1 hypertension to systolic blood pressure (BP) 130-139 mmHg or diastolic BP 80-89 mmHg; however, the degree to which microvascular endothelial dysfunction is evident in adults with stage 1 hypertension remains equivocal. We tested the hypotheses that cutaneous microvascular endothelial dysfunction would be present in adults with stage 1 hypertension (HTN1) compared with normotensive adults (NTN; BP <120/<80 mmHg) but would be less severe compared with adults with stage 2 hypertension (HTN2; systolic BP ≥140 mmHg or diastolic BP ≥90 mmHg) and that this graded impairment would be mediated by reductions in nitric oxide (NO)-dependent dilation. This retrospective analysis included 20 NTN (5 men; 45-64 yr; BP 94-114/60-70 mmHg), 22 HTN1 (11 men; 40-74 yr; BP 110-134/70-88 mmHg), and 44 HTN2 (27 men; 40-74 yr; BP 128-180/80-110 mmHg). BP and nocturnal dipping status were also assessed using 24-h ambulatory BP monitoring. Red cell flux (laser Doppler flowmetry) was measured during intradermal microdialysis perfusion of acetylcholine (ACh; 10-10 to 10-1M) alone and concurrently with the nonspecific nitric oxide (NO) synthase inhibitor N-nitro-l-arginine methyl ester (l-NAME; 15 mM). ACh-induced dilation was impaired in HTN2 (P < 0.01), but not in HTN1 (P = 0.85), compared with NTN. Furthermore, reductions in NO-dependent dilation were evident in HTN2 (P < 0.01) but not in HTN1 (P = 0.76). Regardless of BP, endothelium-dependent dilation was impaired in nondippers (nighttime drop in systolic BP <10%) compared with dippers (nighttime drop in systolic BP ≥10%, P < 0.05). In conclusion, functional impairments in NO-mediated endothelium-dependent dilation were not evident in HTN1. However, regardless of BP classification, the lack of a nocturnal dip in BP was associated with blunted endothelium-dependent dilation.NEW & NOTEWORTHY This is the first study to pharmacologically assess the mechanistic regulation of endothelial function in adults with hypertension, classified according to the 2017 clinical guidelines set for by the American Heart Association (AHA) and American College of Cardiology (ACC). Compared with that in normotensive adults, nitric oxide-mediated endothelium-dependent dilation is impaired in adults with stage 2, but not stage 1, hypertension. Adults lacking a nighttime dip in blood pressure demonstrated reductions in endothelium-dependent dilation.
More Related Videos
 08:21
Author Spotlight: A Pharmacodissection Approach to Uncover Mechanisms in Cardiovascular Disease Risk Populations
Published on: July 21, 2023
 08:41
Assessment of Vascular Tone Responsiveness using Isolated Mesenteric Arteries with a Focus on Modulation by Perivascular Adipose Tissues
Published on: June 3, 2019
Related Concept Videos
 01:28
Hypertension I: Introduction
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies
 01:29
Hypertension II: Pathophysiology
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:30
Peripheral Artery Disease I: Introduction