Related Experiment Video
Updated: Dec 13, 2025
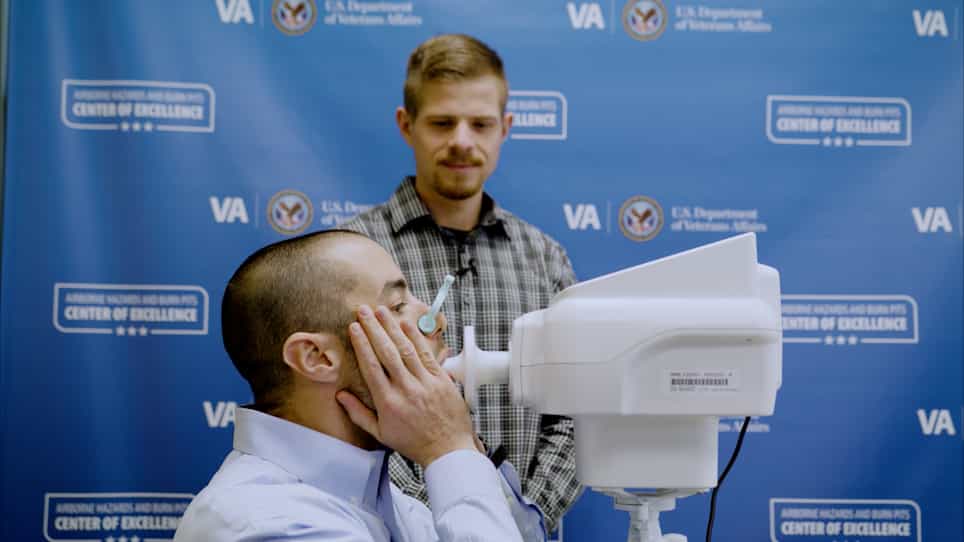
Employing the Forced Oscillation Technique for the Assessment of Respiratory Mechanics in Adults
Published on: February 9, 2022
Prediction of air trapping or pulmonary hyperinflation by forced spirometry in COPD patients: results from COSYCONET
Peter Alter1, Jan Orszag2, Christina Kellerer3
1Dept of Medicine, Pulmonary and Critical Care Medicine, Philipps University of Marburg (UMR), member of the German Center for Lung Research (DZL), Marburg, Germany.

Background:
Air trapping and lung hyperinflation are major determinants of prognosis and response to therapy in chronic obstructive pulmonary disease (COPD). They are often determined by body plethysmography, which has limited availability, and so the question arises as to what extent they can be estimated via spirometry.
Methods:
We used data from visits 1-5 of the COPD cohort COSYCONET. Predictive parameters were derived from visit 1 data, while visit 2-5 data was used to assess reproducibility. Pooled data then yielded prediction models including sex, age, height, and body mass index as covariates. Hyperinflation was defined as ratio of residual volume (RV) to total lung capacity (TLC) above the upper limit of normal. (ClinicalTrials.gov identifier: NCT01245933).
Results:
Visit 1 data from 1988 patients (Global Initiative for Chronic Obstructive Lung Disease grades 1-4, n=187, 847, 766, 188, respectively) were available for analysis (n=1231 males, 757 females; mean±sd age 65.1±8.4 years; forced expiratory volume in 1 s (FEV1) 53.1±18.4 % predicted (% pred); forced vital capacity (FVC) 78.8±18.8 % pred; RV/TLC 0.547±0.107). In total, 7157 datasets were analysed. Among measures of hyperinflation, RV/TLC showed the closest relationship to FEV1 % pred and FVC % pred, which were sufficient for prediction. Their relationship to RV/TLC could be depicted in nomograms. Even when neglecting covariates, hyperinflation was predicted by FEV1 % pred, FVC % pred or their combination with an area under the curve of 0.870, 0.864 and 0.889, respectively.
Conclusions:
The degree of air trapping/hyperinflation in terms of RV/TLC can be estimated in a simple manner from forced spirometry, with an accuracy sufficient for inferring the presence of hyperinflation. This may be useful for clinical settings, where body plethysmography is not available.
More Related Videos
 08:25
Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: