The Geriatric Nutritional Risk Index is a powerful predictor of adverse outcome in the elderly emergency surgery patient
Related Experiment Video
Updated: Dec 13, 2025
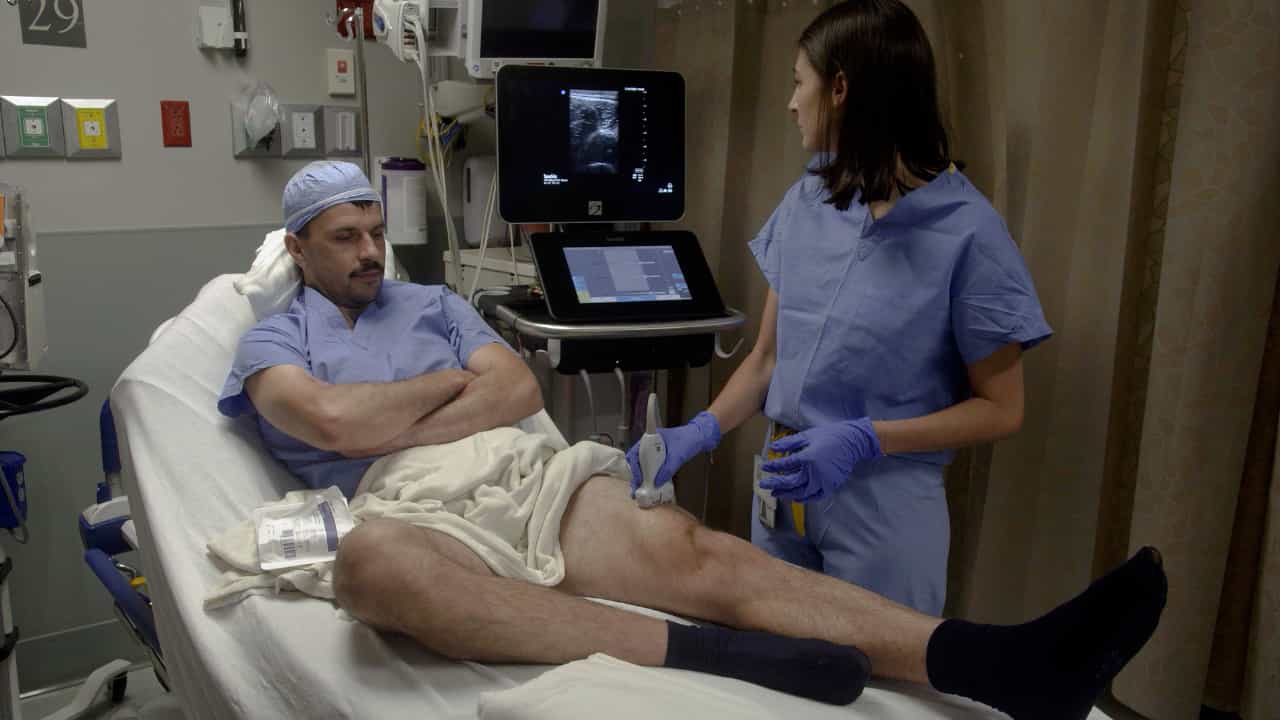
Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Zhenyi Jia1, Mohamad El Moheb, Ask Nordestgaard
1From the Division of Trauma, Emergency Surgery and Surgical Critical Care (Z.J., M.E.M., A.N., J.M.L., K.M., N.K., K.H., M.W.E.H., A.M., D.K., P.F., N.S., M.R., G.V., H.M.A.K.), Massachusetts General Hospital, Boston, Massachusetts; and Department of General Surgery(Z.J.), Shanghai Sixth People's Hospital Affiliated to Shanghai Jiao Tong University, Shanghai, China.

Background:
The degree to which malnutrition impacts perioperative outcomes in the elderly emergency surgery (ES) patient remains unknown. We aimed to study the relationship between malnutrition, as measured by the Geriatric Nutritional Risk Index (GNRI), and postoperative outcomes in elderly patients undergoing ES.
Methods:
Using the 2007 to 2016 American College of Surgeons National Surgical Quality Improvement Program database, all patients 65 years or older undergoing ES were included in our study. The GNRI, defined as (1.489 × albumin [g/L]) + (41.7 × [weight/ideal weight]) was calculated for each patient in the database. Patients with missing height, weight, or preoperative albumin data were excluded. Patients were divided into four malnutrition groups: very severe (GNRI < 73), severe (GNRI, 73-82), moderate (GNRI, 82-92), and mild (GNRI, 92-98). Geriatric Nutritional Risk Index greater than 98 constituted the normal nutrition group. Risk-adjusted multivariable logistic regressions were performed to study the relationship between malnutrition-measured using either GNRI, albumin level, or body mass index less than 18.5 kg/m-and the following postoperative outcomes: 30-day mortality, 30-day morbidity (including infectious and noninfectious complications), and hospital length of stay. The relationship between GNRI score and 30-day mortality for six common ES procedures was then assessed.
Results:
A total of 82,725 patients were included in the final analyses. Of these, 55,214 were malnourished with GNRI less than 98 (66.74%). Risk-adjusted multivariable analyses showed that, as malnutrition worsened from mild to very severe, the risk of mortality, morbidity, and the hospital length of stay progressively increased (all p < 0.05). Patients with very severe malnutrition had at least a twofold increased likelihood of mortality (odds ratio [OR], 2.79; 95% confidence interval [CI], 2.57-3.03), deep vein thrombosis (OR, 2.07; 95% CI, 1.77-2.42), and respiratory failure (OR, 1.95; 95% CI, 1.81-2.11). Geriatric Nutritional Risk Index predicted mortality better than albumin or body mass index alone for ES.
Conclusion:
Malnutrition, measured using GNRI, is a strong independent predictor of adverse outcomes in the elderly ES patient and could be used to assess the nutrition status and counsel patients (and families) preoperatively.
Level Of Evidence:
Prognostic study, Level IV.

Related Concept Videos
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:15
Drug Dosing: Geriatric Patients
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:00
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Distribution
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age