Related Experiment Video
Updated: Dec 13, 2025
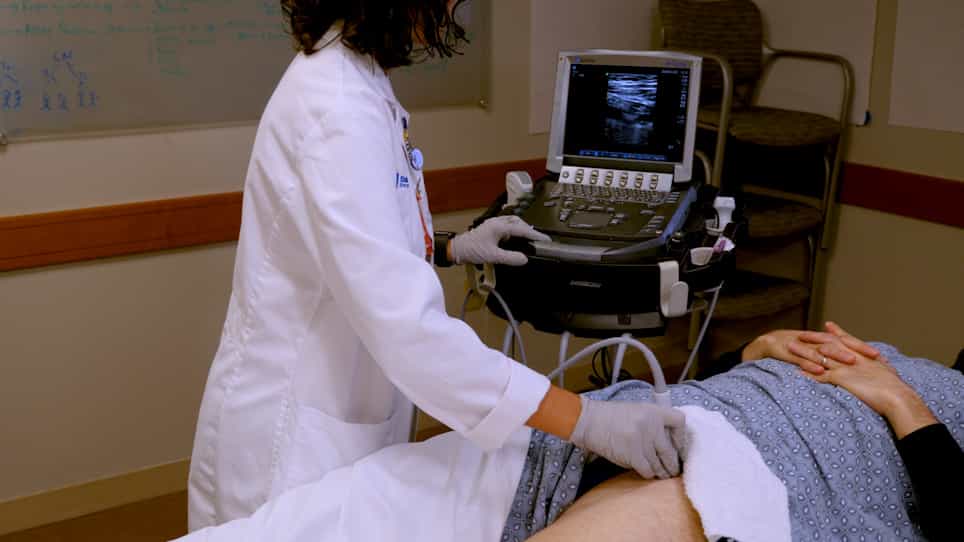

Point-Of-Care Ultrasound Screening for Proximal Lower Extremity Deep Venous Thrombosis
Published on: February 10, 2023
Postdischarge venous thromboembolism following hospital admission with COVID-19
Lara N Roberts1, Martin B Whyte2, Loizos Georgiou1
1King's Thrombosis Centre, Department of Haematological Medicine, and.

Insights
Hospitalized COVID-19 patients do not have a higher risk of post-discharge venous thromboembolism (VTE) compared to other medical admissions. Further trials are needed to determine if extended VTE prevention after discharge is beneficial.
Area of Science:
- Medicine
- Pulmonology
- Critical Care Medicine
Background:
- Severe coronavirus disease 2019 (COVID-19) is associated with an increased risk of venous thromboembolism (VTE), particularly in critically ill patients.
- Current guidelines for VTE prevention and management in COVID-19 patients are inconsistent, especially regarding post-discharge thromboprophylaxis.
Purpose of the Study:
- To evaluate the incidence of hospital-associated VTE (HA-VTE) in COVID-19 patients within 42 days of discharge.
- To compare the post-discharge HA-VTE risk in COVID-19 patients with that of patients discharged following other acute medical illnesses.
Main Methods:
- A quality improvement program tracked post-discharge HA-VTE data for COVID-19 patients.
- Data from 1877 COVID-19 discharges were analyzed, comparing outcomes to 18,159 medical discharges from 2019.
- Root-cause analysis was incorporated to understand hospital-associated VTE events.
Main Results:
- The post-discharge HA-VTE rate for COVID-19 patients was 4.8 per 1000 discharges (9 episodes within 42 days).
- The 2019 medical admission cohort had an HA-VTE rate of 3.1 per 1000 discharges (56 episodes within 42 days).
- The odds ratio for post-discharge HA-VTE in COVID-19 patients compared to 2019 medical admissions was 1.6 (95% CI, 0.77-3.1), indicating no statistically significant increase.
Conclusions:
- Hospitalization for COVID-19 does not appear to confer a higher risk of post-discharge HA-VTE compared to other acute medical conditions.
- The uncertain risk-benefit ratio of extended thromboprophylaxis necessitates further investigation.
- Randomized controlled trials are required to ascertain the efficacy of continuing thromboprophylaxis in COVID-19 patients post-discharge.
Abstract:
The association of severe coronavirus disease 2019 (COVID-19) with an increased risk of venous thromboembolism (VTE) has resulted in specific guidelines for its prevention and management. The VTE risk appears highest in those with critical care admission. The need for postdischarge thromboprophylaxis remains controversial, which is reflected in conflicting expert guideline recommendations. Our local protocol provides thromboprophylaxis to COVID-19 patients during admission only. We report postdischarge VTE data from an ongoing quality improvement program incorporating root-cause analysis of hospital-associated VTE (HA-VTE). Following 1877 hospital discharges associated with COVID-19, 9 episodes of HA-VTE were diagnosed within 42 days, giving a postdischarge rate of 4.8 per 1000 discharges. Over 2019, following 18 159 discharges associated with a medical admission; there were 56 episodes of HA-VTE within 42 days (3.1 per 1000 discharges). The odds ratio for postdischarge HA-VTE associated with COVID-19 compared with 2019 was 1.6 (95% confidence interval, 0.77-3.1). COVID-19 hospitalization does not appear to increase the risk of postdischarge HA-VTE compared with hospitalization with other acute medical illness. Given that the risk-benefit ratio of postdischarge thromboprophylaxis remains uncertain, randomized controlled trials to evaluate the role of continuing thromboprophylaxis in COVID-19 patients following hospital discharge are required.

Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:27
Pulmonary Embolism III: Nursing Management
 01:30
Venous Thrombosis I: Introduction
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care