Related Experiment Video
Updated: Dec 13, 2025


A Protocol to Acquire the Degenerative Tenocyte from Humans
Published on: June 9, 2018
Botulinum Toxin for Chronic Lateral Epicondylitis (LE)
Stephan Grüner1, Axel Schulz2, Klaus Schlüter-Brust3
1Practice of Dr. Grüner, Cologne.

Abstract:
Lateral epicondylitis is a common disease in orthopaedic practice. Although the majority of cases do not become chronic, patients who do not respond to the initial treatment may suffer from pain in the long term and effective treatment is challenging. The off-label use of botulinum toxin is one of the common potential indications for the substance in orthopaedics and traumatology. In a literature review of 2000 - 2019, eight EBM ≥ level 3 studies evaluating the use of botulinum toxin in lateral epicondylitis were found. Five of these studies evaluated botulinum toxin versus placebo in chronic cases; two other studies compared botulinum toxin with corticosteroids in acute cases and classic Hohmann surgery in chronic cases; the eighth study compared botulinum toxin in two different injection sites and corticosteroids by classic injection. Our findings suggest that the use of this substance may be a treatment option in refractory chronic cases before surgery is indicated. The working group on botulinum toxin in O & T of the International Musculoskeletal Pain Society (IMPS/IGOST) introduced an alternative injection schedule, which combines findings from the recent clinical literature with practical experience in order to reduce the risk of side effects while ensuring treatment effectiveness. Using 2 simple tests of function and, if necessary, sonographic verification, 2 separate injection sites in the extensor carpi radialis or the extensor digitorum can be identified by palpation. The tendon level on the lateral epicondyle acts as the third injection site. With optimal use of the ampoule content, the 3 injection sites can be infiltrated individually, depending on the muscle status. On the one hand, this enables treatment to take place after a dual therapy approach and, on the other hand, the risk of overdose in a muscle with subsequent unnecessary muscle weakening can be reduced.
More Related Videos
 05:18
Author Spotlight: Ultrasound-Guided Needle Release Combined with Corticosteroid Injection for the Treatment of Supinator Syndrome
Published on: May 26, 2023
 06:13
Author Spotlight: Insights into Remotely Supervised Neuromodulation Procedure for Phantom Limb Pain
Published on: March 1, 2024
Related Concept Videos
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:20
Myasthenia Gravis: Overview and Treatment
These antibodies interfere with the function of the nicotinic receptors in three ways: by binding to the receptor and disrupting acetylcholine binding; by causing cross-linking of receptors which...
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:09
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:24
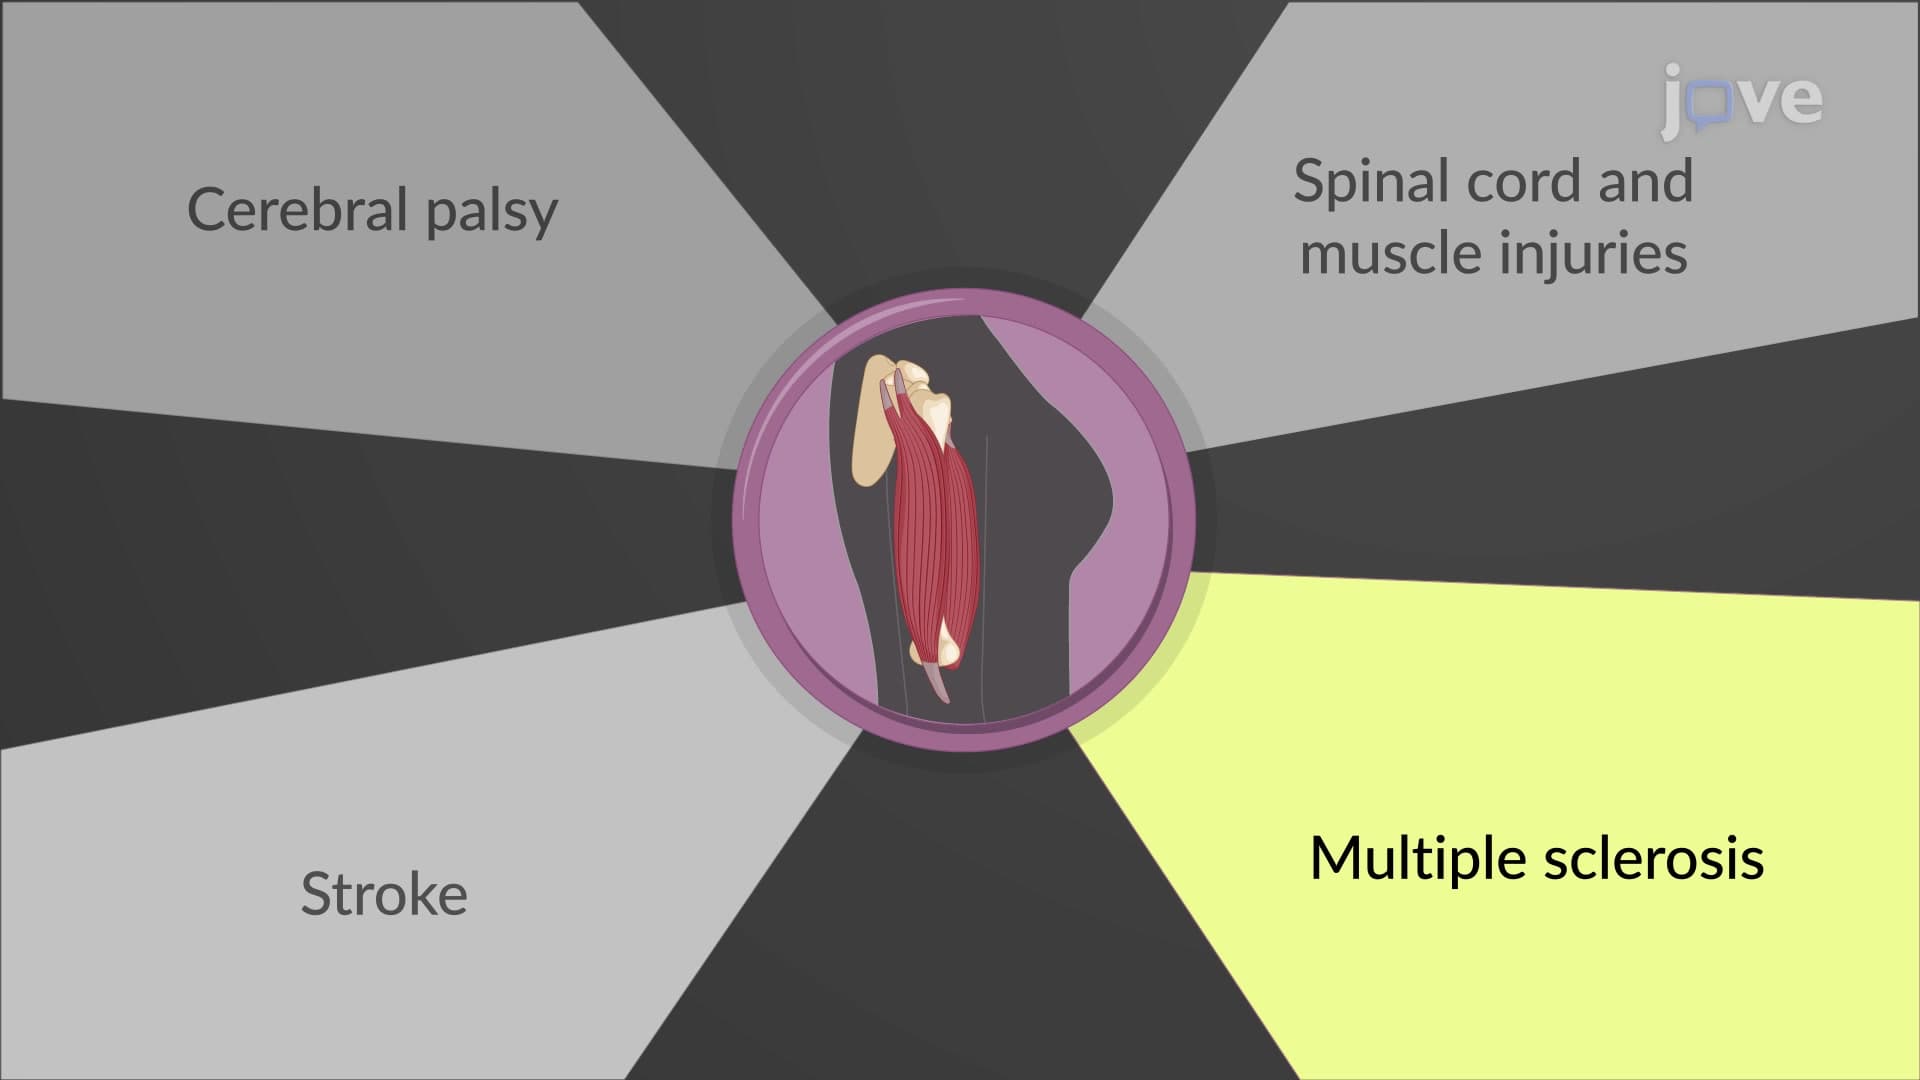
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...