Related Experiment Video
Updated: Dec 12, 2025
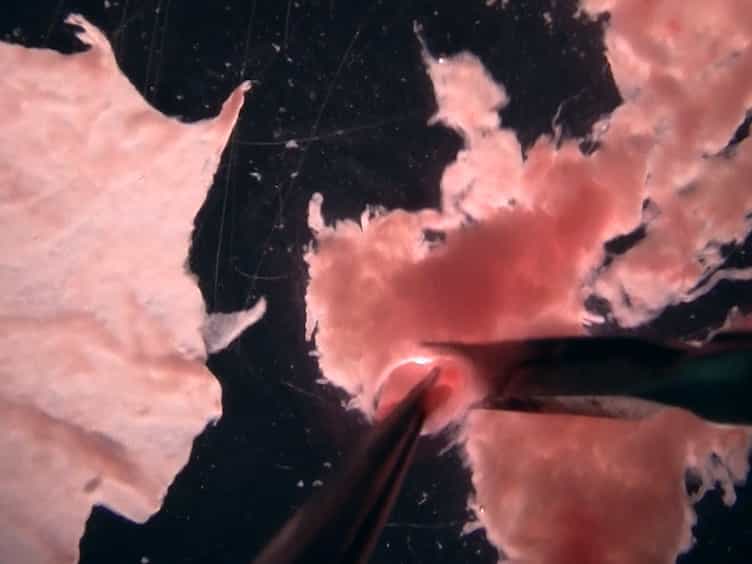
Human Placental and Decidual Organ Cultures to Study Infections at the Maternal-fetal Interface
Published on: July 21, 2016
Placental barrier against COVID-19
Shihoko Komine-Aizawa1, Kazuhide Takada1, Satoshi Hayakawa1
1Division of Microbiology, Department of Pathology and Microbiology, Nihon University School of Medicine, Tokyo, Japan.

Vertical transmission of severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) and possible induction of pregnancy complications, including miscarriage, fetal malformations, fetal growth restriction and/or stillbirth, are serious concerns for pregnant individuals with COVID-19. According to clinical information, the incidence of vertical transmission of SARS-CoV-2 is limited to date. However, even if a neonate tests negative for SARS-CoV-2, frequent abnormal findings, including fetal and maternal vascular malperfusion, have been reported in cases of COVID-19-positive mothers. Primary receptor of SARS-CoV-2 is estimated as angiotensin-converting enzyme 2 (ACE2). It is highly expressed in maternal-fetal interface cells, such as syncytiotrophoblasts, cytotrophoblasts, endothelial cells, and the vascular smooth muscle cells of primary and secondary villi. However other route of transplacental infection cannot be ruled out. Pathological examinations have demonstrated that syncytiotrophoblasts are often infected with SARS-CoV-2, but fetuses are not always infected. These findings suggest the presence of a placental barrier, even if it is not completely effective. As the frequency and molecular mechanisms of intrauterine vertical transmission of SARS-CoV-2 have not been determined to date, intensive clinical examinations by repeated ultrasound and fetal heart rate monitoring are strongly recommended for pregnant women infected with COVID-19. In addition, careful investigation of placental samples after delivery by both morphological and molecular methods is also strongly recommended.
Vertical transmission of severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) and possible induction of pregnancy complications, including miscarriage, fetal malformations, fetal growth restriction and/or stillbirth, are serious concerns for pregnant individuals with COVID-19. According to clinical information, the incidence of vertical transmission of SARS-CoV-2 is limited to date. However, even if a neonate tests negative for SARS-CoV-2, frequent abnormal findings, including fetal and maternal vascular malperfusion, have been reported in cases of COVID-19-positive mothers. Primary receptor of SARS-CoV-2 is estimated as angiotensin-converting enzyme 2 (ACE2). It is highly expressed in maternal-fetal interface cells, such as syncytiotrophoblasts, cytotrophoblasts, endothelial cells, and the vascular smooth muscle cells of primary and secondary villi. However other route of transplacental infection cannot be ruled out. Pathological examinations have demonstrated that syncytiotrophoblasts are often infected with SARS-CoV-2, but fetuses are not always infected. These findings suggest the presence of a placental barrier, even if it is not completely effective. As the frequency and molecular mechanisms of intrauterine vertical transmission of SARS-CoV-2 have not been determined to date, intensive clinical examinations by repeated ultrasound and fetal heart rate monitoring are strongly recommended for pregnant women infected with COVID-19. In addition, careful investigation of placental samples after delivery by both morphological and molecular methods is also strongly recommended.
More Related Videos
 05:31
Author Spotlight: Modeling an Aspect of Preeclampsia in Female Mice Using Hypoxic Human Placenta-Derived Small Extracellular Vesicles
Published on: January 26, 2024
 04:17
Author Spotlight: Advancing Research Through Single Cell Sequencing and Spatial Histology in Placental Tissues
Published on: September 8, 2023
Related Concept Videos
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:23
Factors Affecting Drug Distribution: Physiological Barriers
The capillary endothelial barrier allows only smaller molecules below 600 Da (Daltons) to pass through. It also restricts drugs like heparin that are bound to blood components, limiting their movement within the bloodstream.
The...
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...