Related Experiment Video
Updated: Dec 12, 2025

Rapid Molecular Detection and Differentiation of Influenza Viruses A and B
Published on: January 30, 2017
Factors associated with single-room assignment among patients admitted through the emergency department during
Donia Bouzid1,2, Benoit Visseaux1,3, Anne Perozziello1
1IAME, INSERM, Université de Paris, Paris, France.

Introduction:
Every winter, emergency departments (EDs) face overcrowding with patients presenting influenza-like symptoms, and organisational issues such as single room assignment and droplet precautions to avoid hospital-acquired influenza. Our main objective was to assess the impact of PCR results and patient's severity on single room assignment.
Methods:
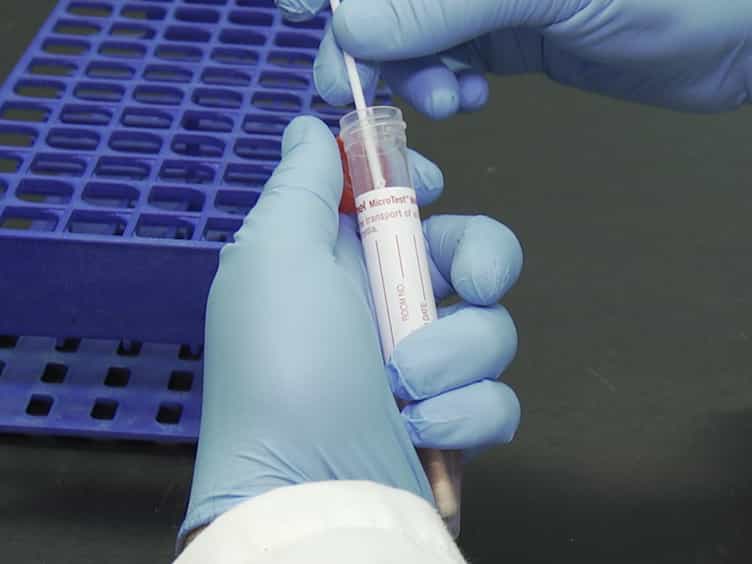
All patients admitted to Bichat-Claude Bernard Hospital through the ED and tested for influenza by PCR (GenXpert, Cepheid) or (FilmArray, BioMérieux) on a nasopharyngeal swab were retrospectively included during three influenza seasons (2015-2018.
Results:
Of 1,330 included patients, 278 (20.9%) had a positive PCR for influenza. The median time to obtain a PCR result was 19 hours, and 238 (18.3%) patients were assigned a single room. Among patients with positive and negative influenza PCR, 22.3% and 16.7% were assigned a single room (p = 0.03). The multivariable analysis was performed on the two first epidemic periods, excluding the third epidemic because of the concomitant use of influenza immune-chromatic test. Only level 1 of the Emergency severity index (ESI) (aOR, 1.9; 95% CI, 1.3-2.8; p < 0.01) was associated with single-room assignment. PCR result was not statistically associated with the decision of single room assignment (aOR, 1.4; 95%CI, 1.0-1.4; p = 0.07).
Conclusion:
A PCR positive for influenza was not significantly associated with single-room assignment. Less than one quarter of influenza patients were adequately assigned a single room, likely due to the long turnaround time of PCR result and other conflicting indications for single room-assignment. Accelerating biological diagnosis could improve single-room assignment.
More Related Videos
 12:21
A Mouse Model for the Transition of Streptococcus pneumoniae from Colonizer to Pathogen upon Viral Co-Infection Recapitulates Age-Exacerbated Illness
Published on: September 28, 2022
 13:45
A Precise Pathogen Delivery and Recovery System for Murine Models of Secondary Bacterial Pneumonia
Published on: September 21, 2019
Related Concept Videos
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:18
Factors Affecting Illness
For instance, risk factors are connected to illness,...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include: