Related Experiment Video
Updated: Dec 12, 2025

Treatment of Facial Deformities using 3D Planning and Printing of Patient-Specific Implants
Published on: May 23, 2020
Displaced odontoid synchondrosis fracture with C1-2 dysjunction in an 18-month-old child: challenges and solutions
Pravin Salunke1, Parth Jani1, Sushanta K Sahoo2
1Neurosurgery, PGIMER, Chandigarh, Sector 12, Chandigarh, 1600l2, India.

Insights
Odontoid synchondral fractures in young children are unstable and require surgery. This case highlights cautious traction and fixation techniques for successful pediatric spinal stabilization.
Area of Science:
- Pediatric Orthopedics
- Neurosurgery
- Spinal Surgery
Background:
- Odontoid synchondral fractures with displacement/angulation in young children present significant instability.
- The small, soft bones in this age group pose challenges for surgical instrumentation and manipulation due to poor pull-out strength.
Observation:
- An 18-month-old child with an odontoid synchondral fracture experienced neurological worsening after minimal traction, revealing C1-2 dysjunction.
- Surgical intervention involved fixation of the C1-2 facets using a short plate and facetal screws.
Findings:
- The case demonstrates that even minimal traction can exacerbate instability in pediatric odontoid fractures.
- Successful surgical fixation of the C1-2 facets was achieved using specialized instrumentation.
Implications:
- Traction in pediatric spinal trauma must be applied with extreme caution to prevent distraction injuries.
- Meticulous intraoperative planning and execution are crucial for successful realignment and fixation, minimizing risks of hardware failure or further injury.
Background:
Odontoid synchondral fractures in very young children with displacement/angulation are highly unstable and require surgical intervention. Soft and small bones with poor pull-out strengths make instrumentation and manipulation difficult.
Case Report:
We report an 18-month-old child with such a fracture where minimal traction made C1-2 dysjunction apparent with neurological worsening. The C1-2 facets were fixed with a short plate and facetal screws. The child had a good outcome.
Conclusion:
Traction should be applied cautiously to avoid distraction injuries. Careful intraoperative manipulation should be planned to avoid any pull outs/fractures while realigning the spine and fixing it.
More Related Videos
 12:25
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:28
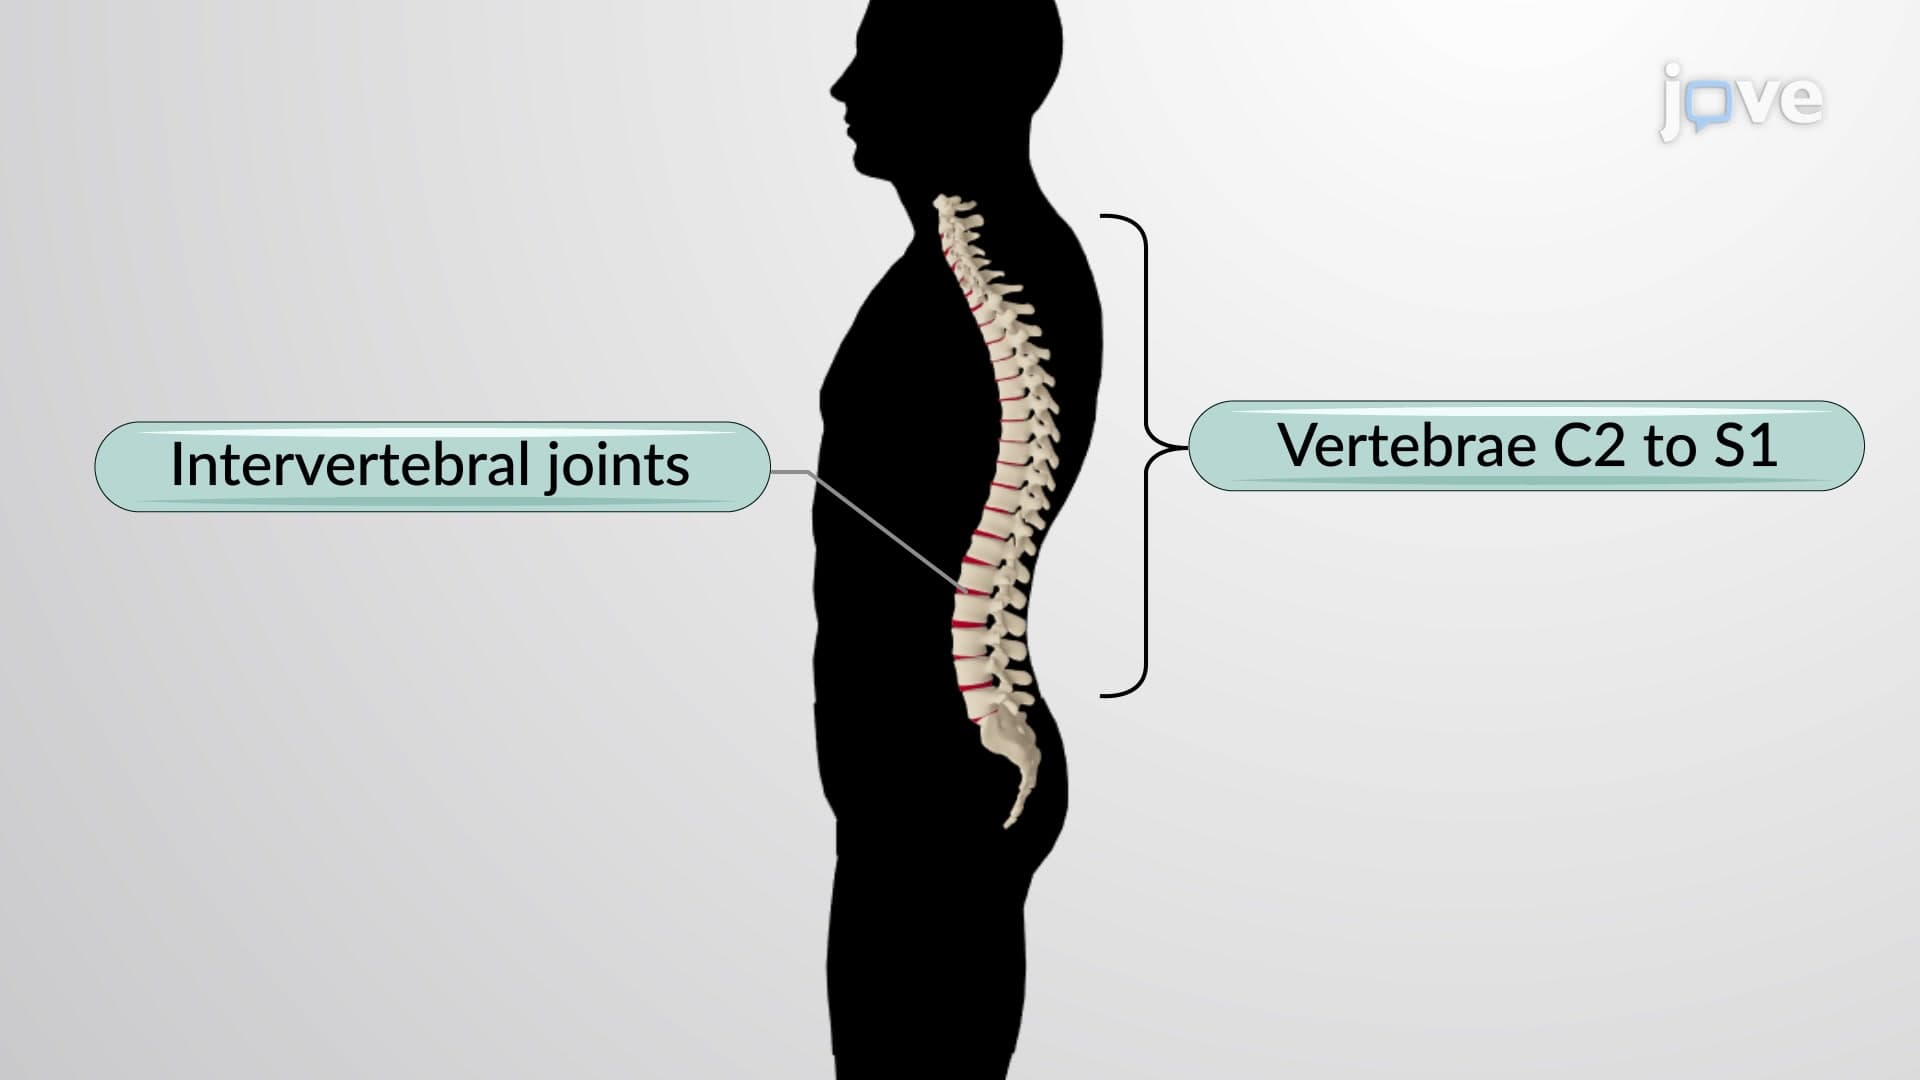
Articulations of the Vertebral Column
 01:17
Structural Joints: Cartilaginous Joints
There are two types of cartilaginous joints:
Synchondrosis
A synchondrosis ("joined by cartilage") is a cartilaginous joint where bones are connected by hyaline cartilage. Synchondrosis may be temporary...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:12
The Hyoid Bone
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...