Related Experiment Video
Updated: Dec 12, 2025
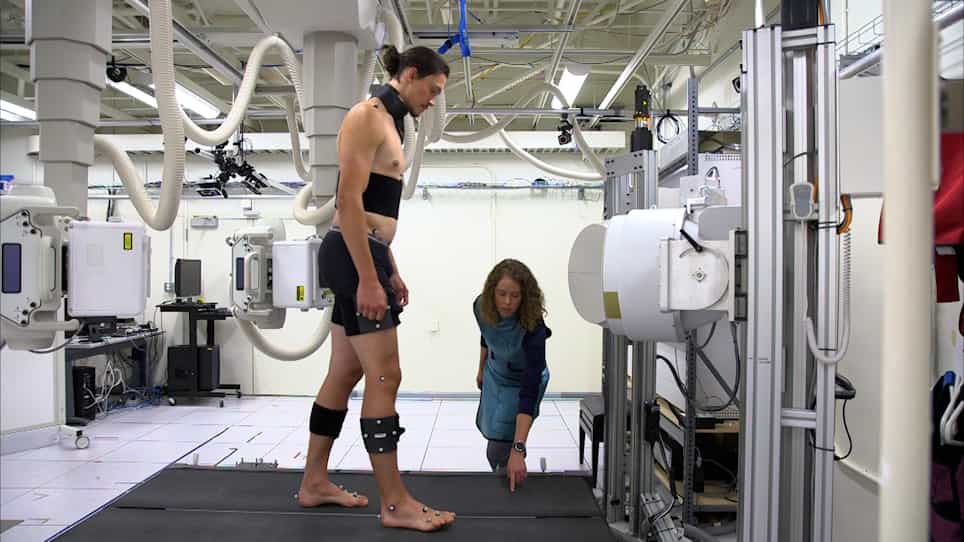

In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Increased incidence, morbidity, and mortality in cirrhotic patients with hip fractures: A nationwide population-based
Chih-Hsiang Chang1,2,3,4, Chee-Jen Chang4,5,6, Yi-Chun Wang5
1Bone and Joint Research Center, 38014Chang Gung Memorial Hospital, Linkou, Taiwan.

Insights
Patients with cirrhosis have a significantly higher risk of hip fractures and worse outcomes, including increased complications and mortality. This highlights the need for targeted preventive strategies and vigilant clinical management in this vulnerable population.
Area of Science:
- Orthopedics
- Hepatology
- Public Health
Background:
- Hip fractures are a major cause of morbidity and mortality, often requiring surgical intervention.
- Patients with cirrhosis exhibit compromised bone density and immune function, predisposing them to fractures and surgical complications.
Purpose of the Study:
- To evaluate the prevalence, complication rates, and mortality associated with hip fractures in patients diagnosed with liver cirrhosis.
- To compare these outcomes against a general population experiencing hip fractures.
Main Methods:
- A population-based study utilizing data from the Taiwan National Health Insurance Research Database (2004-2010).
- Inclusion of 117,129 hip fracture patients, with 4,048 identified as having cirrhosis.
- Comparative analysis of incidence, morbidity, and mortality rates between the cirrhosis and general hip fracture groups.
Main Results:
- Cirrhotic patients with hip fractures were younger (71.2 vs. 73.96 years) and had a 6.95 times higher annual incidence rate.
- Higher rates of infection (3.46% vs. 1.91%), urinary tract infections (9.56% vs. 9.11%), and peptic ulcer disease (8.05% vs. 3.55%) were observed in the cirrhosis group.
- Mortality rates were significantly elevated: 8.76-12.64% within 3 months and 29.72-37.99% within 1 year for the cirrhosis group, compared to 4.96-5.30% and 12.84-14.57% for the general group, respectively.
Conclusions:
- Cirrhotic patients face a substantially higher incidence of hip fractures and poorer post-fracture outcomes, including increased complications and mortality.
- These findings underscore the critical need for heightened clinical vigilance regarding osteoporosis and hip fracture risk in individuals with liver cirrhosis.
- Targeted interventions and management strategies are essential to mitigate the adverse effects of hip fractures in this high-risk population.
Objectives:
Hip fractures mostly require surgical treatment and are associated with increased health-care costs and mortality rates. Patients with cirrhosis have low bone marrow density and inferior immune status which contribute to a higher fracture rate and higher surgical complication rate. This population-based study evaluated the prevalence, complication, and mortality rates due to hip fractures in cirrhotic patients.
Methods:
Taiwan National Health Insurance Research Database data were used. The study group included 117,129 patients with hip fractures diagnosed from 2004 to 2010, including 4048 patients with cirrhosis. The overall prevalence, morbidity, and mortality rates of the cirrhosis group with hip fractures were compared with the rates of a general group with hip fractures.
Results:
The cirrhosis group patients were younger than the general group patients (71.2 vs. 73.96 years, p < 0.001). The annual incidence of hip fractures in the cirrhosis and general groups was 46-54 and 7-7.5 per 10,000 person-years, respectively, with an incidence rate ratio of 6.95 (95% confidence interval 6.74-7.18). The rates of infection, urinary tract infection, and peptic ulcer disease were higher in the cirrhosis group (3.46% vs. 1.91%, 9.56% vs. 9.11%, and 8.05% vs. 3.55%, respectively; all p < 0.001). The mortality rate after hip fracture was also higher in the cirrhosis group than in the general group (within 3 months: 8.76-12.64% vs. 4.96-5.30% and within 1 year: 29.72-37.99% vs. 12.84-14.57%). Conclusion: Cirrhotic patients with hip fractures were relatively younger; had a seven times higher annual hip fracture incidence; had higher complication rates of infection, urinary tract infection, and peptic ulcer disease; and had two to three times higher a mortality rate at 3 months and 1 year. Clinicians should pay particular attention to the possibility of osteoporosis and hip fractures in patients with liver cirrhosis.
Level Of Evidence:
Level III, case-control study.


Related Concept Videos
 01:26
Effect of Hepatic Disease on Pharmacokinetics: Drug Dosing and Hepatic Blood Flow
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...