Related Experiment Video
Updated: Dec 11, 2025

Estimation of Urinary Nanocrystals in Humans using Calcium Fluorophore Labeling and Nanoparticle Tracking Analysis
Published on: February 9, 2021
Effects of Oxalobacter formigenes in subjects with primary hyperoxaluria Type 1 and end-stage renal disease: a Phase
Bernd Hoppe1, Patricia A Pellikka2, Bastian Dehmel3
1Division of Pediatric Nephrology, Department of Pediatrics, University Hospital Bonn, Bonn, Germany.

Background:
In primary hyperoxaluria Type 1 (PH1), endogenous oxalate overproduction significantly elevates urinary oxalate excretion, resulting in recurrent urolithiasis and/or progressive nephrocalcinosis and often early end-stage renal disease (ESRD). In ESRD, dialysis cannot sufficiently remove oxalate; plasma oxalate (Pox) increases markedly, inducing systemic oxalate deposition (oxalosis) and often death. Interventions to reduce Pox in PH1 subjects with ESRD could have significant clinical impact. This ongoing Phase II, open-label trial aimed to evaluate whether long-term Oxabact™ (Oxalobacter formigenes, OC5, OxThera Intellectual Property AB, Sweden) lowers Pox in PH1 ESRD subjects, ameliorating clinical outcome.
Methods:
PH1 ESRD subjects on stable dialysis regimens were examined. Subjects were administered one OC5 capsule twice daily for up to 36 months or until transplantation. Total Pox values, cardiac function and safety were evaluated. Free Pox was evaluated in a comparative non-treated PH1 dialysis group using retrospective chart reviews and analyses.
Results:
Twelve subjects enrolled in an initial 6-week treatment phase. Following a washout of up to 4 weeks, eight subjects entered a continuation study; outcomes after 24 months of treatment are presented. After 24 months, all subjects had reduced or non-elevated Pox compared with baseline. Cardiac function improved, then stabilized. No treatment-related serious adverse events were reported.
Conclusions:
Compared with an untreated natural control cohort, 24 months OC5 administration was beneficial to PH1 ESRD subjects by substantially decreasing Pox concentrations, and improving or stabilizing cardiac function and clinical status, without increasing dialysis frequency. OC5 was safe and well-tolerated.
More Related Videos
 11:47
Using 2-Photon Microscopy to Quantify the Effects of Chronic Unilateral Ureteral Obstruction on Glomerular Processes
Published on: March 4, 2022
 09:40
Isolation, Characterization, And High Throughput Extracellular Flux Analysis of Mouse Primary Renal Tubular Epithelial Cells
Published on: June 20, 2018
Related Concept Videos
 01:19
Phase I Oxidative Reactions: Overview
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:29
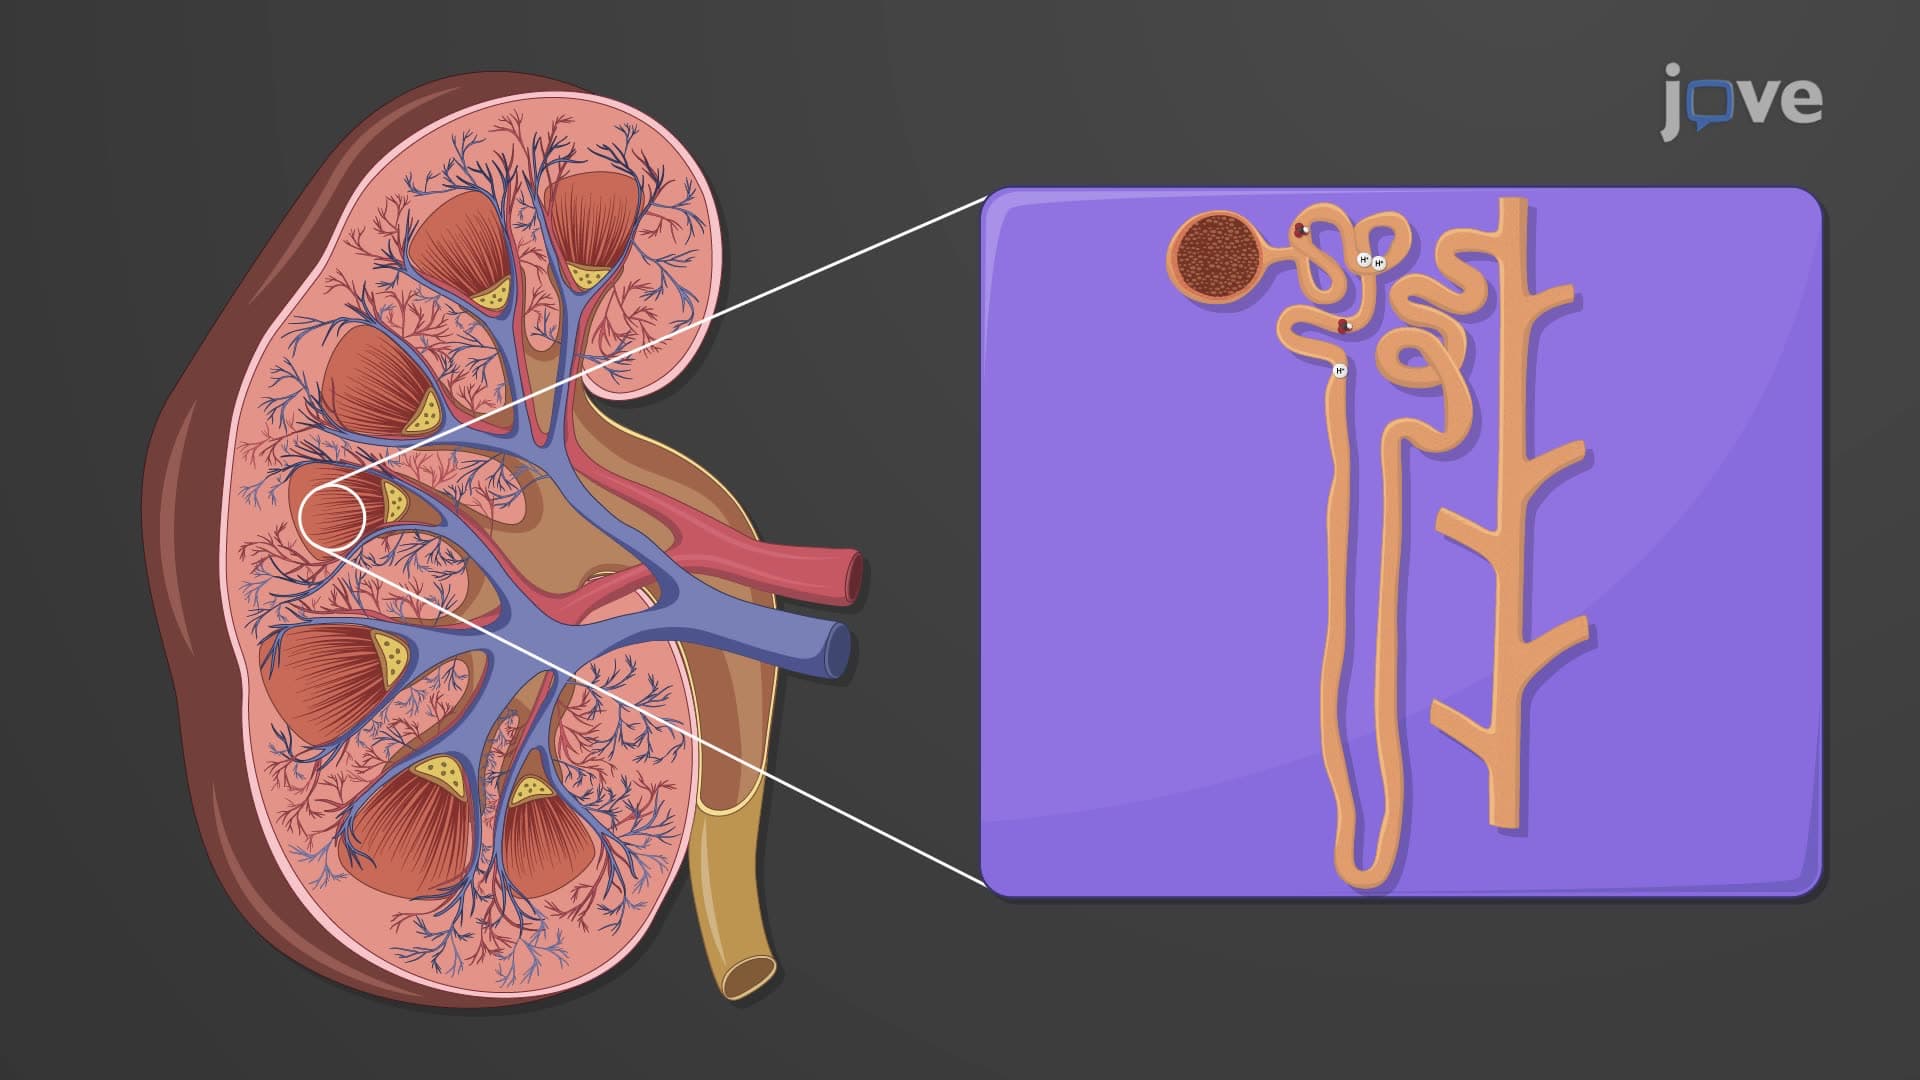
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:17
Drug Metabolism: Phase I Reactions
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations