Related Experiment Video
Updated: Dec 11, 2025
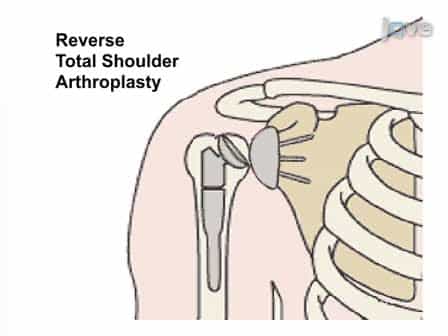

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Reoperation Risk After Total Elbow Arthroplasty Versus Open Reduction Internal Fixation for Distal Humerus Fractures
Nitin Goyal1, Daniel D Bohl1, Kevin L Ong2
1Department of Orthopedic Surgery, Rush University Medical Center, Chicago, IL; and.

Objective:
To compare reoperation risk after total elbow arthroplasty (TEA) and open reduction internal fixation (ORIF) for intra-articular distal humerus fractures in elderly patients.
Design:
Retrospective comparative.
Setting:
Five percent Medicare Part B claims database.
Patients:
Patients older than 65 years of age with closed distal humerus fractures undergoing TEA or ORIF from 1996 to 2016.
Intervention:
TEA and ORIF.
Main Outcome Measure:
Reoperation risk based on multivariate Cox proportional hazards modeling.
Results:
A total of 142 TEA and 522 ORIF cases were identified. TEA patients had a greater age and Charlson Comorbidity Index , as well as a higher prevalence of rheumatoid arthritis and osteoporosis than ORIF patients (P < 0.05). Although reoperation risk was lower for TEA than that for ORIF within the entire cohort (11.3% vs. 25.1%; hazard ratio = 0.49; P = 0.014), no significant difference was found for TEA and ORIF performed between 2006 and 2016 (12.6% vs. 18.4%; hazard ratio = 0.73; P = 0.380). The death rate was 65.5% in the TEA group at 3.6 years and 55.7% in the ORIF group at 4.9 years.
Conclusions:
TEA was associated with a decreased reoperation risk compared with ORIF, although this difference did not exist for more recent procedures after popularization of the locking plate technology and half of the reoperations after ORIF were for instrumentation removal. The high death rate within several years of the index procedure may contribute to the low TEA revision rate beyond the short-term when following patients into the medium and long term. Further study comparing TEA and locked plating using prospective, randomized data with long-term follow-up and functional outcomes is warranted.
Level Of Evidence:
Therapeutic Level III. See Instructions for Authors for a complete description of levels of evidence.

