Related Experiment Video
Updated: Jun 30, 2026

Functional Transcranial Doppler Ultrasound for Monitoring Cerebral Blood Flow
Published on: March 15, 2021
Transcranial Doppler as a Predictor of Ischemic Events in Vertebral Artery Dissection
Alejandro M Brunser1,2, Pablo M Lavados2, Gabriel Cavada3
1Department of General Emergency, Clínica Alemana de Santiago, Facultad de Medicina Clínica Alemana - Universidad del Desarrollo, Santiago, Chile.

Insights
Transcranial Doppler (TCD) can identify patients with vertebral arterial dissection (VAD) at risk of ischemic events (IEs). Post-stenotic flow in the basilar artery (PFB) on TCD is a significant predictor of IE in VAD patients.
Area of Science:
- Neurology
- Vascular Medicine
- Diagnostic Imaging
Background:
- Vertebral arterial dissection (VAD) carries a risk of ischemic events (IEs).
- Predictors of IE in VAD are not well-established.
- Transcranial Doppler (TCD) is used for carotid dissections, but its role in VAD is less clear.
Purpose of the Study:
- To investigate clinical and ultrasound predictors of IE in VAD patients.
- To determine the utility of TCD in identifying high-risk VAD patients.
Main Methods:
- Retrospective evaluation of 88 VAD patients (June 2017-February 2020).
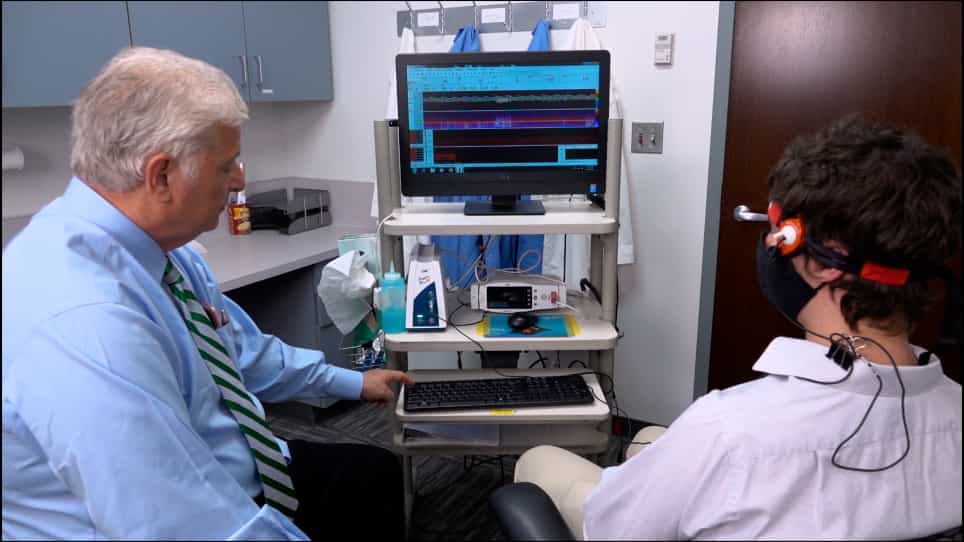
- Clinical assessment and TCD including sonographic curves, microembolic signals (MES), and breath-holding index (BHI) test.
- Multivariable regression analysis to identify independent IE predictors.
Main Results:
- 23.9% of VAD patients had abnormal TCD findings.
- No IE occurred in patients with normal TCD.
- Post-stenotic flow in the basilar artery (PFB) was the sole independent predictor of IE (OR: 68.6).
Conclusions:
- TCD is a valuable tool for predicting IE risk in VAD.
- PFB identified on TCD is a strong predictor of IE in VAD patients.
Background And Purpose:
Transcranial Doppler (TCD) helps identify patients with carotid dissections at risk of ischemic events (IEs). There is paucity of data identifying independent predictors of IE in vertebral arterial dissection (VAD). We sought to investigate the clinical and ultrasound predictors of IE.
Methods:
Patients with VAD admitted between June 2017 and February 2020 were evaluated clinically and with TCD; sonographic curves, microembolic signals (MES), and the breath-holding index (BHI) test were applied. Covariates found on univariate screen (P < .25) were included in a multivariable linear regression to identify independent predictors of IEs.
Results:
Of 88 patients with 100 VAD, 75 (85.2%) were females with a mean age 37.9 ± 7.5 years. All patients received antiplatelet treatment. TCD monitoring lasted an average of 21 ± 2.1 minutes. TCD was abnormal in 23 cases (26.1%); 21 patients had abnormal sonographic curves in the vertebral/basilar arteries, while in 4 cases, MES were present and in 5 (4.5%), BHI was abnormal. None of the patients with a normal TCD had an IE. Six strokes occurred during follow up. On univariate analysis, male sex, diabetes, dyslipidemia, a previous myocardial infarct, migraine, time of consultation to the ER, bilateral VAD, MES, BHI abnormalities, post stenotic flow in the basilar artery (PFB), and basilar/vertebral velocities were significantly associated with the risk of IEs. In the multivariate analysis, only the presence of PFB was a significant predictor of IE (OR: 68.6, 95% CI 5-937, <.001).
Conclusions:
TCD in VAD predicts patients at high risk of IE.