Related Experiment Video
Updated: Dec 10, 2025


Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
Surgical diversion of enterohepatic circulation in pediatric cholestasis
Caroline Lemoine1, Riccardo Superina1
1Division of Transplant Surgery, Ann & Robert H. Lurie Children's Hospital of Chicago, Northwestern University Feinberg School of Medicine, 225 E. Chicago Ave. Box 57, Chicago, IL 60611, USA.

Insights
Biliary diversion surgery offers a safe and effective option for children with Progressive Familial Intrahepatic Cholestasis (PFIC) and Alagille Syndrome (AS). This procedure can alleviate symptoms and potentially delay or prevent the need for a liver transplant.
Area of Science:
- Hepatology
- Pediatric Gastroenterology
- Surgical Innovation
Background:
- Progressive Familial Intrahepatic Cholestasis (PFIC) and Alagille Syndrome (AS) are genetic cholestatic liver diseases.
- These conditions cause jaundice and severe pruritus, often leading to end-stage liver disease in childhood.
- Liver transplantation improves survival but carries risks like disease recurrence and extra-hepatic manifestations.
Purpose of the Study:
- To evaluate the efficacy and safety of biliary diversion techniques in managing pediatric cholestatic liver diseases.
- To assess the potential of these procedures in improving patient symptoms and reducing the need for liver transplantation.
Main Methods:
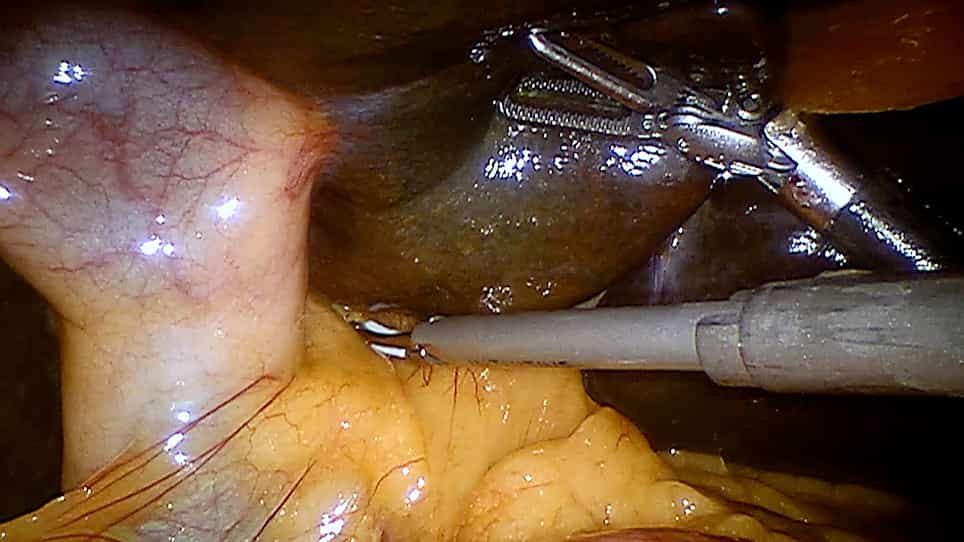
- Review of surgical techniques including partial external biliary diversion, ileal exclusion, and partial internal biliary diversion.
- Analysis of patient outcomes, focusing on symptom improvement, bile acid levels, and impact on liver disease progression.
- Assessment of procedural safety, morbidity, and mortality rates.
Main Results:
- Biliary diversion techniques have shown success in improving cholestasis symptoms and reducing serum bile acid concentrations.
- These procedures are generally safe with low morbidity and mortality in pediatric patients.
- Diversion can reduce liver inflammation and injury, potentially delaying or avoiding liver transplantation.
Conclusions:
- Biliary diversion represents a valuable therapeutic option for PFIC and AS, offering symptomatic relief and liver protection.
- While effective, further comparative studies are needed to establish the optimal diversion technique.
- These surgical interventions can significantly improve the quality of life and long-term outcomes for affected children.
Abstract:
Progressive familial intrahepatic cholestasis (PFIC) and Alagille syndrome (AS) are conditions caused by either an autosomal recessive or an autosomal dominant genetic defect, and they are both characterized by cholestasis, jaundice, and severe debilitating pruritus refractory to medical management. Before the advent of liver transplantation, most PFIC patients would die from end-stage liver disease in the first decade of life. Although liver transplantation has led to patients' survival, disease recurrence (PFIC-2) and severe extra-hepatic manifestations of the disease (PFIC-1) occurred post transplant. In the late 1980s, Whitington described the use of partial external biliary diversion in PFIC and AS patients as a successful way to improve symptoms and decrease circulating bile acid serum concentrations. Since then, other diversion techniques have been described (ileal exclusion and partial internal biliary diversion). These techniques have the benefit of avoiding a stoma, but equivalent results have not been demonstrated (recurrence of cholestasis after ileal exclusion, limited follow up after internal biliary diversion). Overall, studies have showed that biliary diversions in children with cholestasis are safe procedures with low morbidity and mortality, and that they can reduce inflammation and ongoing liver injury, therefore delaying or avoiding the need for liver transplantation in some patients.