Related Experiment Video
Updated: Dec 10, 2025
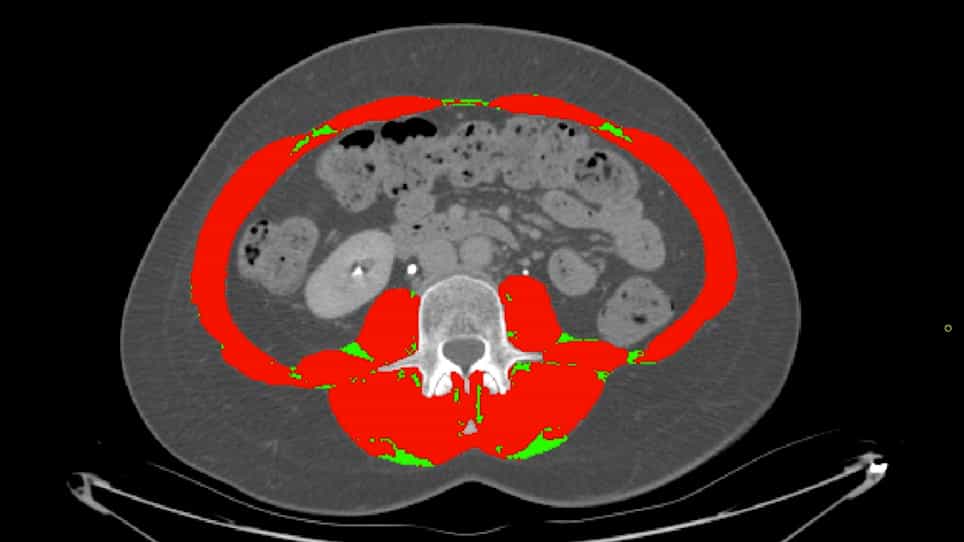

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Diagnosis, prevalence, and clinical impact of sarcopenia in COPD: a systematic review and meta-analysis
Walter Sepúlveda-Loyola1,2,3,4, Christian Osadnik5,6, Steven Phu3,4
1Department of Physiotherapy, Londrina State University, Londrina, Paraná, Brazil.

Abstract:
Sarcopenia prevalence and its clinical impact are reportedly variable in chronic obstructive pulmonary disease (COPD) due partly to definition criteria. This review aimed to identify the criteria used to diagnose sarcopenia and the prevalence and impact of sarcopenia on health outcomes in people with COPD. This review was registered in PROSPERO (CRD42018092576). Five electronic databases were searched to August 2018 to identify studies related to sarcopenia and COPD. Study quality was assessed using validated instruments matched to study designs. Sarcopenia prevalence was determined using authors' definitions. Comparisons were made between people who did and did not have sarcopenia for pulmonary function, exercise capacity, quality of life, muscle strength, gait speed, physical activity levels, inflammation/oxidative stress, and mortality. Twenty-three studies (70% cross-sectional) from Europe (10), Asia (9), and North and South America (4) involving 9637 participants aged ≥40 years were included (69.5% men). Sarcopenia criteria were typically concordant with recommendations of hEuropean and Asian consensus bodies. Overall sarcopenia prevalence varied from 15.5% [95% confidence interval (CI) 11.8-19.1; combined muscle mass, strength, and/or physical performance criteria] to 34% (95%CI 20.6-47.3; muscle mass criteria alone) (P = 0.009 between subgroups) and was greater in people with more severe [37.6% (95%CI 24.8-50.4)] versus less severe [19.1% (95%CI 10.2-28.0)] lung disease (P = 0.020), but similar between men [41.0% (95%CI 26.2-55.9%)] and women [31.9% (95%CI 7.0-56.8%)] (P = 0.538). People with sarcopenia had lower predicted forced expiratory volume in the first second (mean difference -7.1%; 95%CI -9.0 to -5.1%) and poorer exercise tolerance (standardized mean difference -0.8; 95%CI -1.4 to -0.2) and quality of life (standardized mean difference 0.26; 95%CI 0.2-0.4) compared with those who did not (P < 0.001 for all). No clear relationship was observed between sarcopenia and inflammatory or oxidative stress biomarkers. Incident mortality was unreported in the literature. Sarcopenia is prevalent in a significant proportion of people with COPD and negatively impacts upon important clinical outcomes. Opportunities exist to optimize its early detection and management and to evaluate its impact on mortality in this patient group.

Related Concept Videos
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD:
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...