Related Experiment Video
Updated: Dec 10, 2025


Basophil Activation Test for Allergy Diagnosis
Published on: May 31, 2021
Component resolved diagnostics in peanut sensitized children with and without a history of clinical reaction
Yasmin Hamzavi Abedi1,2, Cristina P Sison3,4, Punita Ponda1,2
1Department of Medicine and Pediatrics, Donald and Barbara Zucker School of Medicine at Hofstra/Northwell, Hempstead, New York.

Insights
Serum peanut-specific IgE (PN-sIgE) correlates with peanut component-resolved diagnostics (CRD) levels. High PN-sIgE may indicate that CRD is unnecessary, potentially streamlining peanut allergy diagnosis.
Area of Science:
- Allergy and Immunology
- Diagnostic Medicine
- Pediatric Research
Background:
- Peanut-specific IgE (PN-sIgE) and component-resolved diagnostics (CRD) are standard in peanut allergy evaluation.
- The clinical utility of CRD at varying PN-sIgE levels remains unclear.
- A common CRD threshold for predicting challenge outcomes is 0.35 kUA/L for Ara h2.
Purpose of the Study:
- To assess the diagnostic utility of CRD in relation to PN-sIgE levels.
- To compare CRD and PN-sIgE utility in children with and without a history of clinical reactivity to peanuts.
- To evaluate the correlation between peanut component-resolved diagnostics (ARAH) and serum PN-sIgE.
Main Methods:
- Retrospective chart review of 196 children undergoing PN-sIgE and CRD testing.
- Statistical analysis including Fisher's exact test, McNemar test, Gwet's AC1 statistic, and logistic regression.
- Comparison of CRD and PN-sIgE results between patients with and without documented clinical reactivity to peanuts.
Main Results:
- Peanut component-resolved diagnostics (ARAH) levels ≤0.35 kUA/L were significantly associated with PN-sIgE <2 kUA/L (p < 0.0001).
- Higher ARAH thresholds (1 and 2 kUA/L) also correlated significantly with lower PN-sIgE levels (<2, <5, <14 kUA/L).
- These correlations were consistent regardless of the patient's history of clinical reactivity.
Conclusions:
- Peanut component-resolved diagnostics (ARAH) levels demonstrate a strong correlation with serum PN-sIgE levels.
- ARAH levels are unlikely to be below 0.35, 1, or 2 kUA/L if PN-sIgE is >2 kUA/L, irrespective of clinical history.
- Consideration of PN-sIgE levels may reduce the need for routine CRD, and reflex CRD ordering at PN-sIgE ≤5 kUA/L could be beneficial, pending further validation.
Abstract:
Background: Serum Peanut-specific-IgE (PN-sIgE) and peanut-component-resolved-diagnostics (CRD) are often ordered simultaneously in the evaluation for peanut allergy. Results often guide the plans for peanut oral challenge. However, the clinical utility of CRD at different total PN-sIgE levels is unclear. A commonly used predefined CRD Ara h2 cutoff value in the literature predicting probability of peanut challenge outcomes is 0.35kUA/L. Objective: To examine the utility of CRD in patients with and without a history of clinical reactivity to peanut (PN). Methods: This was a retrospective chart review of 196 children with PN-sIgE and CRD testing, of which, 98 patients had a clinical history of an IgE-mediated reaction when exposed to PN and 98 did not. The Fisher's exact test was used to assess the relationship between CRD and PN-sIgE at different cutoff levels, McNemar test and Gwet's approach (AC1 statistic) were used to examine agreement between CRD and PN-sIgE, and logistic regression was used to assess differences in the findings between patients with and without reaction history. Results: Ara h 1, 2, 3, or 9 (ARAH) levels ≤0.35 kUA/L were significantly associated with PN-sIgE levels <2 kUA/L rather than ≥2 kUA/L (p < 0.0001). When the ARAH threshold was increased to 1 kUA/L and 2 kUA/L, these thresholds were still significantly associated with PN-sIgE levels of <2, <5, and <14 kUA/L. These findings were not significantly different in patients with and without a history of clinical reactivity. Conclusion: ARAH values correlated with PN-sIgE. Regardless of clinical history, ARAH levels are unlikely to be below 0.35, 1, or 2 kUA/L if the PN-sIgE level is >2 kUA/L. Thus, if possible, practitioners should consider PN-sIgE rather than automatically ordering CRD with PN-sIgE every time. Laboratory procedures that allow automatically and reflexively adding CRD when the PN-sIgE level is ≤5 kUA/L can be helpful. However, further studies are needed in subjects with challenge-proven PN allergy.


Related Concept Videos
 02:06
Allergic Reactions
 01:27
Allergic Drug Reactions
 00:42
Cross-reactivity
 01:30
Hypersensitivities
Types of Hypersensitivities
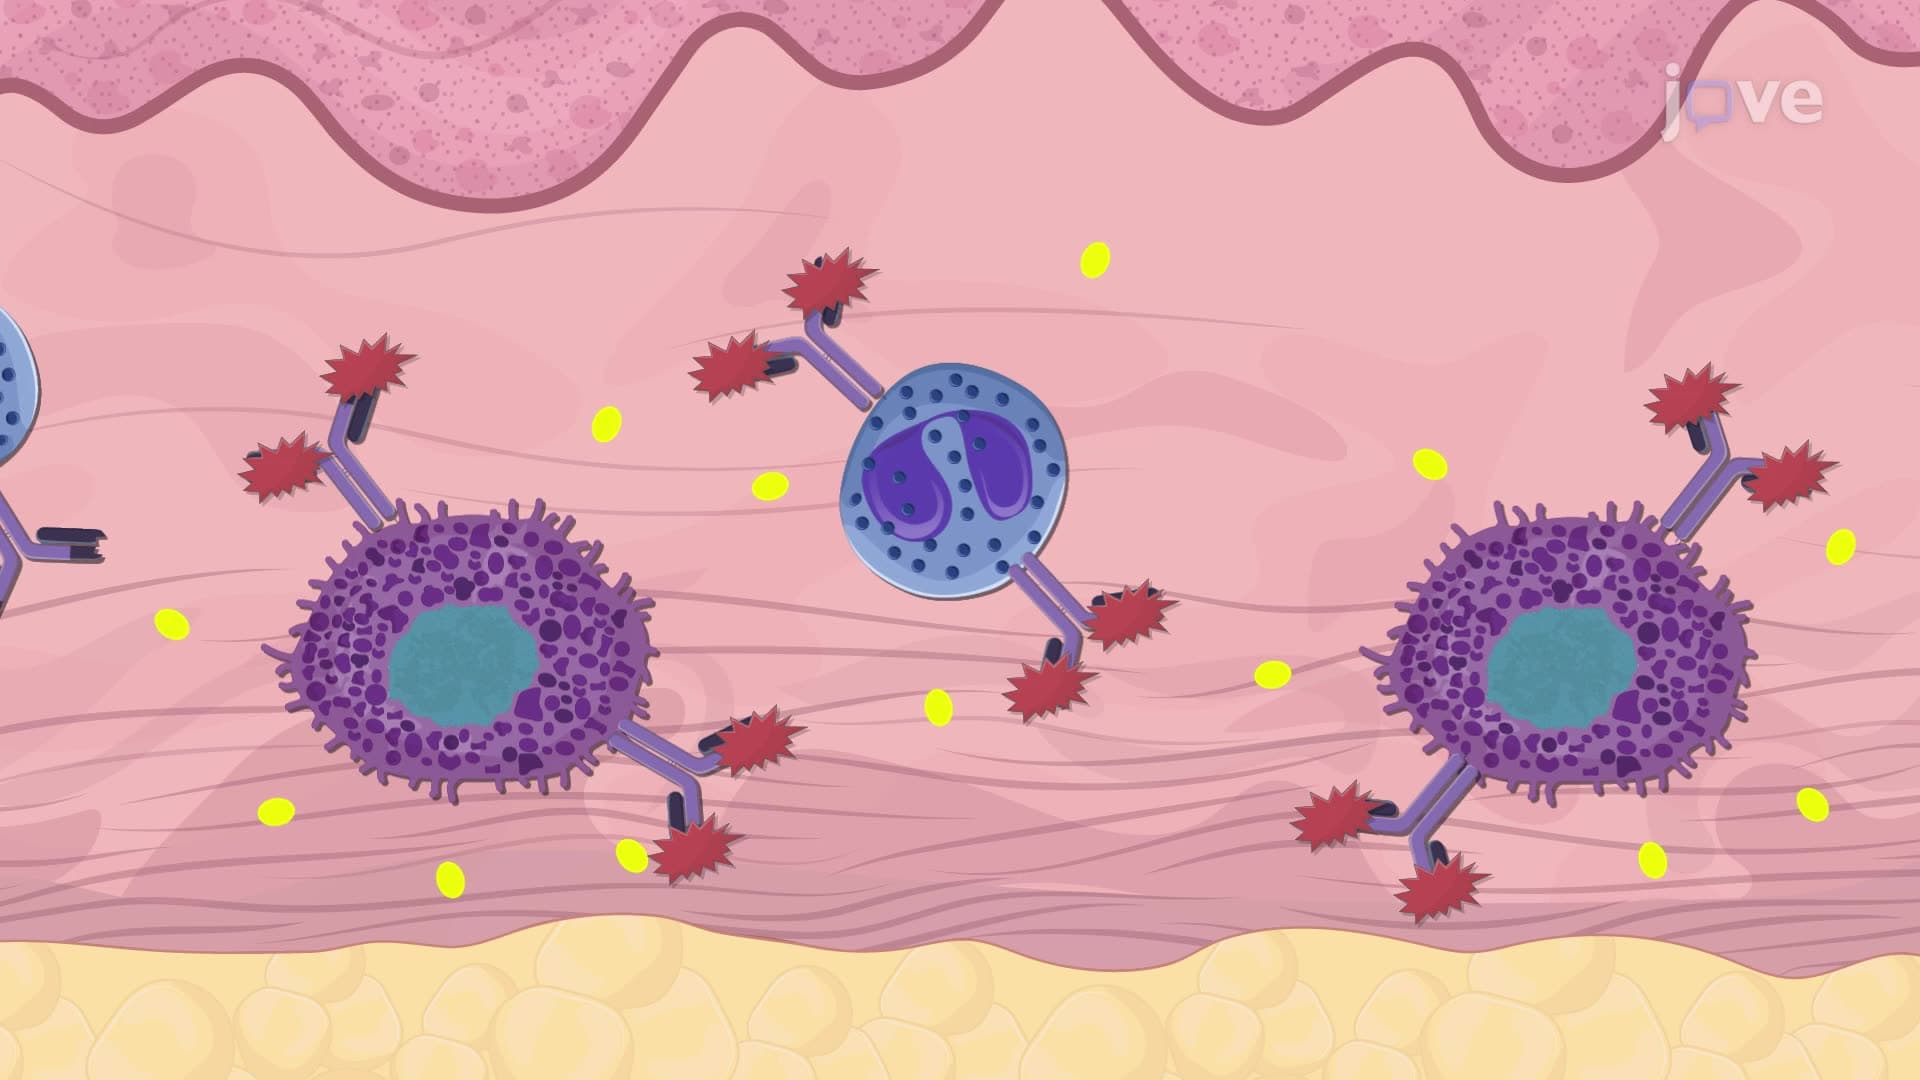
Hypersensitivity reactions are categorized into four types: Type 1, Type 2, Type 3, and Type 4. Each type has a distinct mechanism...
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...