Related Experiment Video
Updated: Dec 10, 2025


Quantification of the Immunosuppressant Tacrolimus on Dried Blood Spots Using LC-MS/MS
Published on: November 8, 2015
Intrapatient variability in concentration/dose ratio of tacrolimus predicts transplant-associated thrombotic
Ken Sagou1,2, Nobuaki Fukushima3, Shun Ukai3
1Department of Hematology and Oncology, JA Aichi Konan Kosei Hospital, 137, Omatsubara, Takaya-cho, Konan, Aichi, 483-8704, Japan. kensagou@gmail.com.

Tacrolimus (TAC) is essential for prophylaxis of acute graft-versus-host disease (aGVHD) after allogeneic hematopoietic cell transplantation (allo-HSCT). We have sometimes observed large fluctuations in TAC concentration. However, links between the variability in the concentration or the concentration/dose (C/D) ratio of TAC and clinical complications remain ambiguous. To clarify relationships between various parameters of TAC and early complications such as pre-engraftment immune reactions/engraftment syndrome, aGVHD, and transplant-associated thrombotic microangiopathy (TA-TMA), a total of 146 patients who underwent allo-HSCT were included. Intrapatient variabilities in the concentration and C/D ratio of TAC were estimated by intrapatient mean absolute deviation (iMAD). The mean concentration and C/D ratio of TAC were not significantly different between with and without complications. A strong association was observed between greater iMAD for TAC C/D ratio from days 15 to 21 and the development of TA-TMA. iMAD values for TAC C/D ratio of 11.4 or greater was a risk factor for TA-TMA and the cumulative incidence of nonrelapse mortality (NRM) was significantly higher in patients with iMAD values for TAC C/D ratio of 11.4 or greater. Intrapatient variability in the C/D ratio of TAC was associated with the incidence of TA-TMA and NRM and might be useful for predicting TA-TMA.
Tacrolimus (TAC) is essential for prophylaxis of acute graft-versus-host disease (aGVHD) after allogeneic hematopoietic cell transplantation (allo-HSCT). We have sometimes observed large fluctuations in TAC concentration. However, links between the variability in the concentration or the concentration/dose (C/D) ratio of TAC and clinical complications remain ambiguous. To clarify relationships between various parameters of TAC and early complications such as pre-engraftment immune reactions/engraftment syndrome, aGVHD, and transplant-associated thrombotic microangiopathy (TA-TMA), a total of 146 patients who underwent allo-HSCT were included. Intrapatient variabilities in the concentration and C/D ratio of TAC were estimated by intrapatient mean absolute deviation (iMAD). The mean concentration and C/D ratio of TAC were not significantly different between with and without complications. A strong association was observed between greater iMAD for TAC C/D ratio from days 15 to 21 and the development of TA-TMA. iMAD values for TAC C/D ratio of 11.4 or greater was a risk factor for TA-TMA and the cumulative incidence of nonrelapse mortality (NRM) was significantly higher in patients with iMAD values for TAC C/D ratio of 11.4 or greater. Intrapatient variability in the C/D ratio of TAC was associated with the incidence of TA-TMA and NRM and might be useful for predicting TA-TMA.

Related Concept Videos
 01:29
Therapeutic Drug Monitoring: Affecting Factors
 01:15
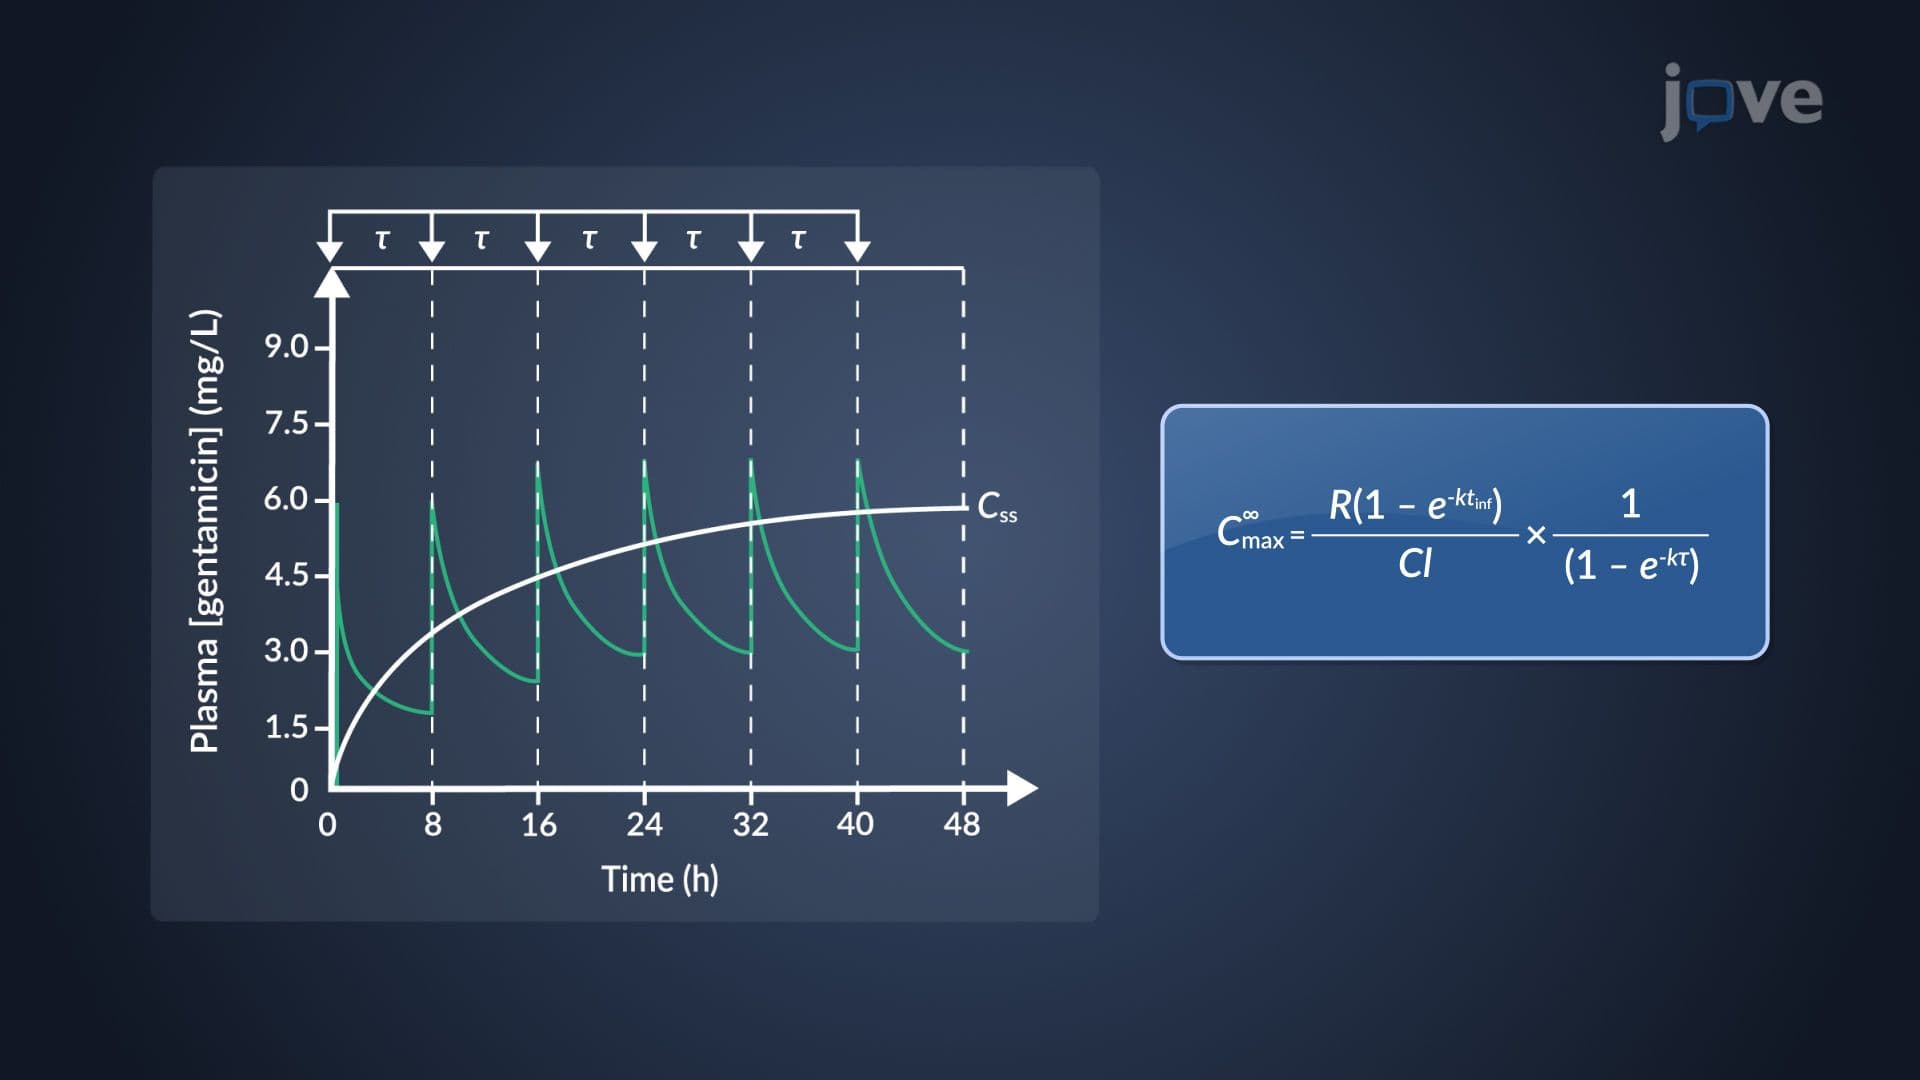
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:24
Dosage Regimen: Individualization
 01:24
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:16
Therapeutic Drug Monitoring: Overview and Classification
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant