

Evaluation of amikacin use and comparison of the models implemented in two Bayesian forecasting software packages to
Alice C Ryan1, Jane E Carland2,3, Robert C McLeay4
1The School of Medicine, The University of Notre Dame Australia, Sydney, NSW, Australia.

Aims:
Bayesian forecasting software can assist in guiding therapeutic drug monitoring (TDM)-based dose adjustments for amikacin to achieve therapeutic targets. This study aimed to evaluate amikacin prescribing and TDM practices, and to determine the suitability of the amikacin model incorporated into the DoseMeRx® software as a replacement for the previously available software (Abbottbase®).
Methods:
Patient demographics, pathology, amikacin dosing history, amikacin concentrations and Abbottbase® predicted TDM targets (area under the curve up to 24 hours, maximum concentration and trough concentration) were collected for adults receiving intravenous amikacin (2012-2017). Concordance with the Australian Therapeutic Guidelines was assessed. Observed and predicted amikacin concentrations were compared to determine the predictive performance (bias and precision) of DoseMeRx®. Amikacin TDM targets were predicted by DoseMeRx® and compared to those predicted by Abbottbase®.
Results:
Overall, guideline compliance for 63 courses of amikacin in 47 patients was suboptimal. Doses were often lower than recommended. For therapy >48 h, TDM sample collection timing was commonly discordant with recommendations, therapeutic target attainment low and 34% of dose adjustments inappropriate. DoseMeRx® under-predicted amikacin concentrations by 0.9 mg/L (95% confidence interval [CI] -1.4 to -0.5) compared with observed concentrations. However, maximum concentration values (n = 19) were unbiased (-1.7 mg/L 95%CI -5.8 to 0.8) and precise (8.6% 95%CI 5.4-18.1). Predicted trough concentration values (n = 7) were, at most, 1 mg/L higher than observed. Amikacin area under the curve values estimated using Abbottbase® (181 mg h/L 95%CI 161-202) and DoseMeRx® (176 mg h/L 95%CI 152-199) were similar (P = .59).
Conclusion:
Amikacin dosing and TDM practice was suboptimal compared with guidelines. The model implemented by DoseMeRx® is satisfactory to guide amikacin dosing.
More Related Videos
 10:33
Expedited Radiation Biodosimetry by Automated Dicentric Chromosome Identification ADCI and Dose Estimation
Published on: September 4, 2017
 06:19
Author Spotlight: Characterizing Airway Environments to Advance Model Systems and Antimicrobial Discovery in Cystic Fibrosis and Chronic Respiratory Infections
Published on: October 11, 2024
Related Concept Videos
 01:20
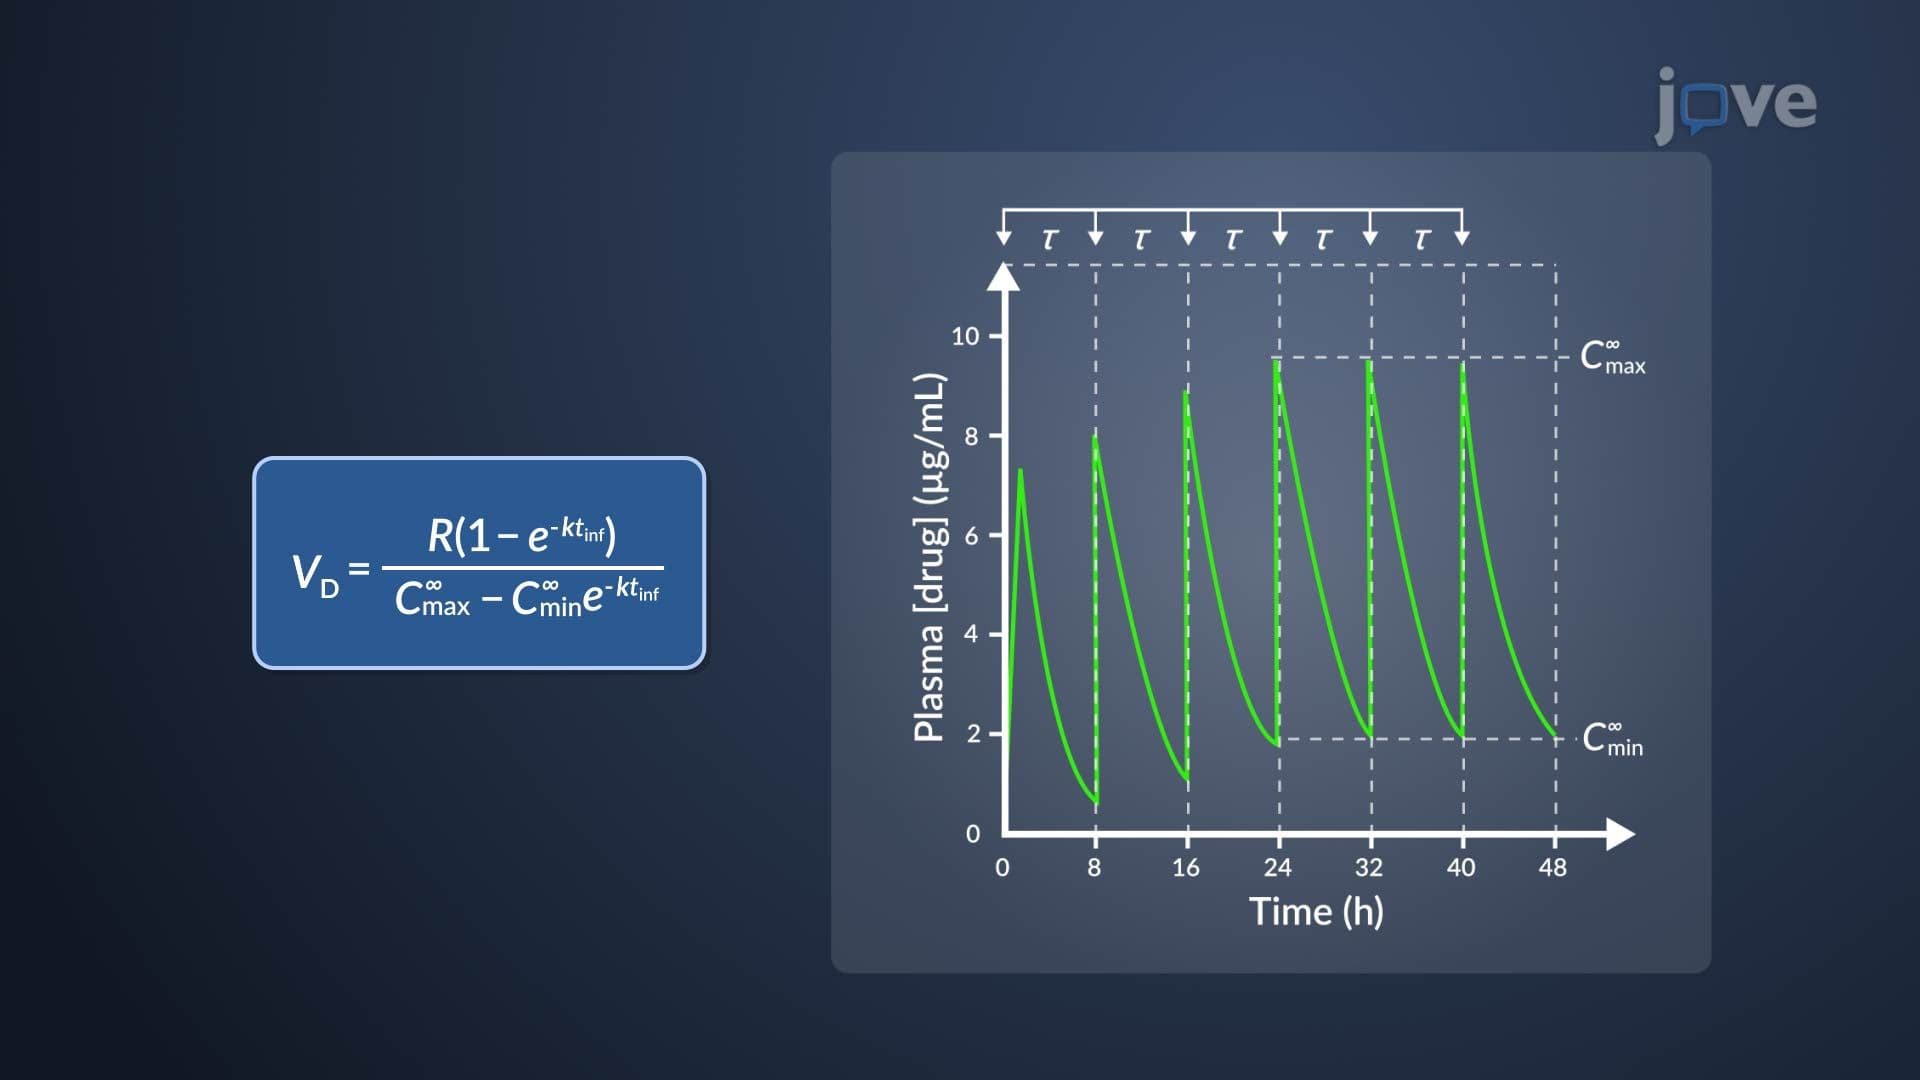
Estimation of k and VD of Aminoglycosides
 01:26
Pharmacokinetic Models: Comparison and Selection Criterion
Physiological models take a detailed approach by considering specific molecular processes. They can predict drug distribution, metabolism, and elimination changes, providing a comprehensive understanding of how drugs interact with the body.
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:14
Analysis Methods of Pharmacokinetic Data: Model and Model-Independent Approaches
The model approach uses mathematical models to describe changes in drug concentration over time. Pharmacokinetic models help characterize drug behavior in patients, predict drug concentration in the body fluids, calculate optimum dosage regimens, and evaluate the risk of toxicity. However, ensuring that the model fits the experimental data accurately...
 01:20
Pharmacokinetic Models: Overview
There are three primary types of models: empirical, compartment, and physiological. Empirical models, with minimal...