Related Experiment Video
Updated: Dec 9, 2025


Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
Risk Factors Predicting C- Versus S-shaped Sagittal Spine Profiles in Natural, Relaxed Sitting: An Important Aspect
Hwee Weng Dennis Hey1, Miguel Rafael David Ramos1, Eugene Tze-Chun Lau1
1University Orthopaedics, Hand and Reconstructive Microsurgery (UOHC), National University Health System, Singapore.

Study Design:
A cross-sectional study on a randomly selected prospective cohort of patients presenting to a single tertiary spine center.
Objective:
The aim of this study was to describe the clinical and radiographic parameters of patients with S- and C-shaped thoracolumbar sagittal spinal profiles, and to identify predictors of these profiles in a natural, relaxed sitting posture.
Summary Of Background Data:
Sagittal realignment in adult spinal deformity surgery has to consider the sitting profile to minimize the risks of junctional failure. Persistence of an S-shaped sagittal profile in the natural, relaxed sitting posture may reflect a lesser need to accommodate for this posture during surgical realignment.
Methods:
Consecutive patients with low back pain underwent whole body anteroposterior and lateral radiographs in both standing and sitting. Baseline clinical data of patients and radiographic parameters of both standing and sitting sagittal profiles were compared using χ, unpaired t tests, and Wilcoxon rank-sum test. Subsequently, using stepwise multivariate logistic regression analysis, predictors of S-shaped curves were identified while adjusting for confounders.
Results:
Of the 120 patients included, 54.2% had S-shaped curves when sitting. The most common diagnoses were lumbar spondylosis (26.7%) and degenerative spondylolisthesis (26.7%). When comparing between patients with S- and C-shaped spines in the sitting posture, only diagnoses of degenerative spondylolisthesis (odds ratio [OR], 5.44; P = 0.01) and degenerative scoliosis (OR, 2.00; P = 0.039), and pelvic incidence (PI) >52.5° (OR, 5.48; P = 0.008), were predictive of an S-shaped sitting sagittal spinal alignment on multivariate analysis.
Conclusion:
Stiffer lumbar curves (eg, patients with degenerative spondylolisthesis and degenerative scoliosis) or those who have a predilection for an S-shaped standing sagittal profile when sitting (eg, high PI) may be more amenable to fusion in accordance with previously studied sagittal realignment targets. In contrast, more flexible curves may benefit from less aggressive lordotic realignment to prevent potential junctional failures.
Level Of Evidence:
3.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 06:28
Biomechanical Changes Related to Low Back Pain: An Innovative Tool for Movement Pattern Assessment and Treatment Evaluation in Rehabilitation
Published on: December 13, 2024
Related Concept Videos
 01:16
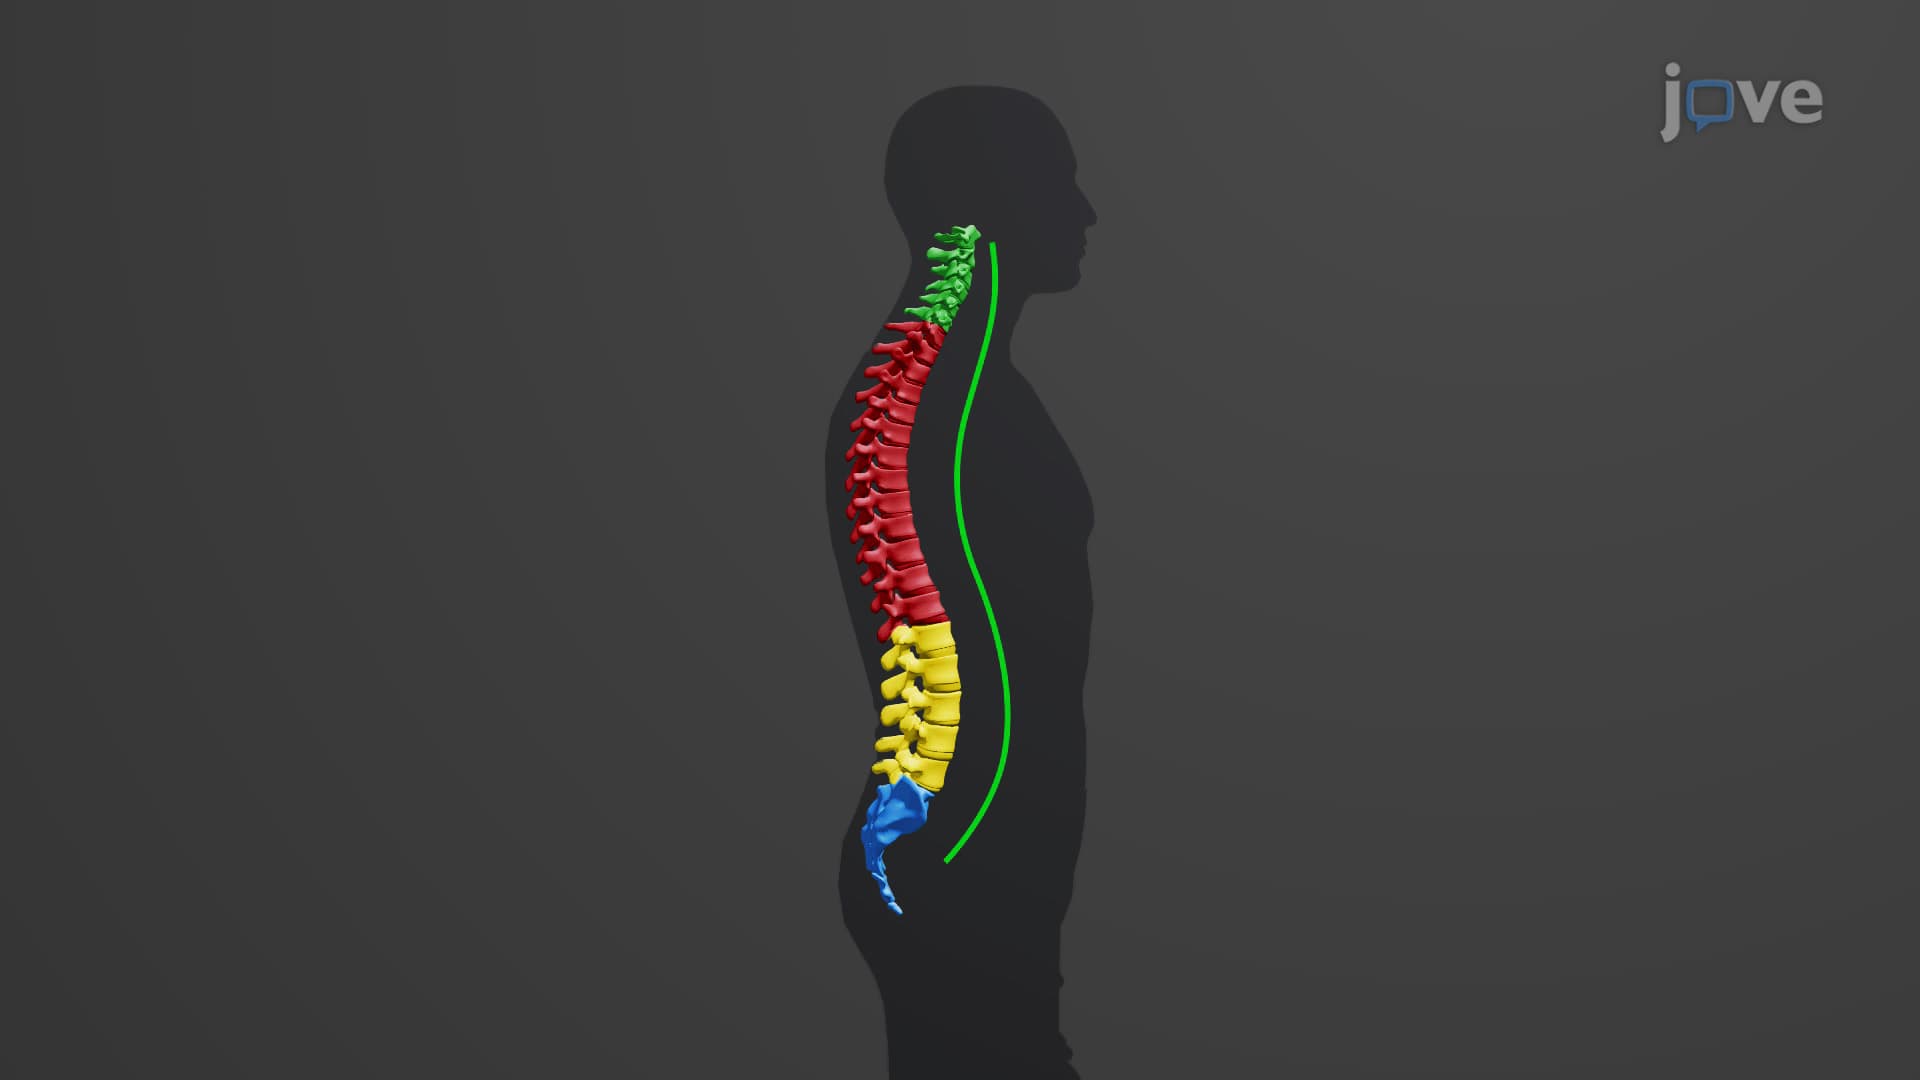
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:11
Anatomical Positions
The body is upright, facing forward, and standing erect.
The feet are parallel and flat on the floor.
The arms are hanging by the...