Related Experiment Video
Updated: Dec 9, 2025


How to Administer Near-Infrared Spectroscopy in Critically ill Neonates, Infants, and Children
Published on: August 19, 2020
Decreased cerebral oxygen saturation levels during direct laryngoscopy with spontaneous ventilation in children
Oshri Wasserzug1, Gadi Fishman1, Ophir Handzel2
1Pediatric ENT Unit, Tel Aviv, Israel; Department of Anesthesiology, Tel Aviv Sourasky Medical Center, Sackler Faculty of Medicine, Tel Aviv University, Tel Aviv, Israel.

Insights
Direct laryngoscopy in children with spontaneous ventilation may reduce brain oxygenation, even when peripheral oxygen levels appear normal. This finding suggests standard monitoring may miss critical cerebral oxygen changes during the procedure.
Area of Science:
- Pediatric Anesthesiology
- Cerebral Oxygenation Monitoring
- Airway Management
Background:
- Direct laryngoscopy in children typically uses spontaneous ventilation, with cerebral oxygenation effects unstudied.
- Standard monitoring via pulse oximetry may not reflect cerebral oxygen saturation during this procedure.
Purpose of the Study:
- To determine if spontaneous ventilation during pediatric direct laryngoscopy causes significant reductions in cerebral oxygen saturation.
- To assess if these cerebral oxygen reductions correlate with peripheral oxygen saturation changes.
Main Methods:
- A pilot study involving 16 children undergoing direct laryngoscopy with general anesthesia and spontaneous ventilation.
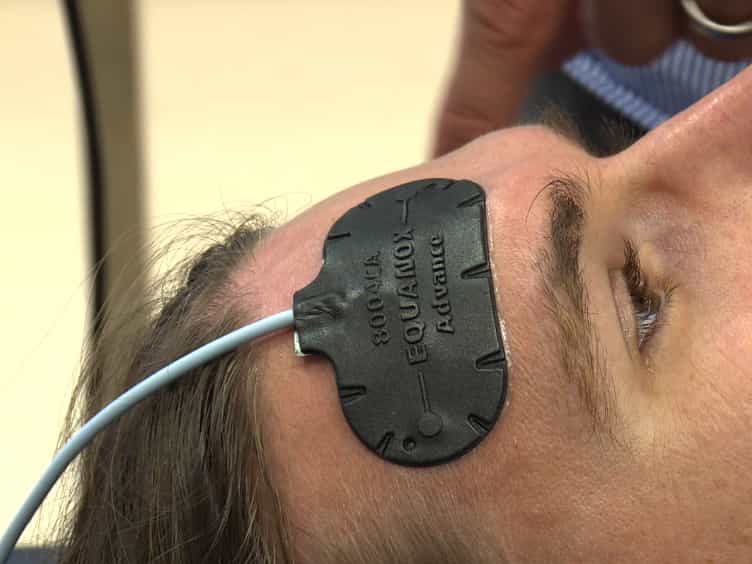
- Cerebral oxygenation monitored using the INVOS™ system (near-infrared spectroscopy) on the forehead.
- Simultaneous recording of peripheral pulse oximetry for comparison.
Main Results:
- Cerebral oxygen saturation decreased by over 20% from baseline in 70% of children with tracheostomy and 33% without.
- Peripheral oxygen saturation levels remained stable in all participants.
- Significant cerebral oxygenation decrease occurred around 14 minutes post-anesthesia induction.
Conclusions:
- Pediatric direct laryngoscopy with spontaneous ventilation can lead to undetected reductions in brain oxygenation.
- Standard pulse oximetry may not adequately monitor cerebral oxygen levels in these cases.
- Further research is needed to understand the clinical implications of these cerebral oxygen changes.
Introduction:
Direct laryngoscopy in children is usually performed with spontaneous ventilation and monitored by pulse oximetry. It is currently unknown if spontaneous ventilation has an effect on cerebral oxygenation. We hypothesized that cerebral oxygenation may be impeded during direct laryngoscopy with spontaneous ventilation in children.
Objective:
Our objective was to determine if children who undergo direct laryngoscopy under general anesthesia with spontaneous breathing experience significant reductions in cerebral oxygen saturation levels, and whether or not these reductions are accompanied by decreases in peripheral oxygen saturation levels.
Methods:
This pilot study included 16 consecutive children who underwent direct laryngoscopy under general anesthesia and spontaneous ventilation. The INVOS™ system, which is currently used to monitor cerebral oxygen saturation levels during neurosurgery and cardiothoracic surgery, consists of a processing unit and 2 sensors that are applied to the patient's forehead. We used it to record cerebral oxygenation levels throughout the procedure. Peripheral pulse oximetry was recorded simultaneously, and the results were compared to the levels recorded by the INVOS™ system.
Results:
Cerebral oxygen saturation levels decreased by more than 20% from baseline in 7/10 children with tracheostomy and in 2/6 children without tracheostomy, while peripheral oxygen saturation levels remained intact in all the children. The mean time from induction of anesthesia to significant decrease in the cerebral oxygenation level (rSO2) was 14 ± 6 min for the tracheostomy group and 14.5 ± 1.5 min for the no tracheostomy group.
Conclusions:
Children who undergo direct laryngoscopy under general anesthesia with spontaneous ventilation may display reductions in brain oxygenation levels that are not detected by standard pulse oximetry, which reflects only peripheral oxygenation levels. Further study is required to explore the possible effect of this phenomenon in children who undergo direct laryngoscopy.

Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:19
Special considerations while measuring oxygen saturation
Ensuring accuracy in vital sign recordings while prioritizing patient comfort and minimizing anxiety is...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:26
Oxygen Delivering System I: Nasal Cannula and Face Mask
Nasal Cannula
A nasal cannula is a lightweight tube split at one end into two prongs and placed in the nostrils. It is typically used to deliver low to medium levels of oxygen.
Suggested flow rate: The suggested flow rate for a nasal cannula typically ranges between 1 and 6 L/min.
Oxygen percentage setting:...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...