Accuracy of controlled attenuation parameter compared with ultrasound for detecting hepatic steatosis in children with severe obesity
Jurgen H Runge1, Jet van Giessen1, Laura G Draijer2,3,4
1Department of Radiology and Nuclear Medicine, Amsterdam University Medical Centers, Location Academic Medical Center, University of Amsterdam, Amsterdam, The Netherlands.

Insights
Controlled Attenuation Parameter (CAP) and ultrasound (US) show similar accuracy in detecting liver steatosis in obese children. CAP offers better specificity when US relies solely on echogenicity for screening.
Area of Science:
- Pediatric Gastroenterology
- Hepatology
- Medical Imaging
Background:
- Non-alcoholic fatty liver disease (NAFLD) is a growing concern in obese children.
- Accurate non-invasive methods for diagnosing and grading liver steatosis are crucial in pediatric populations.
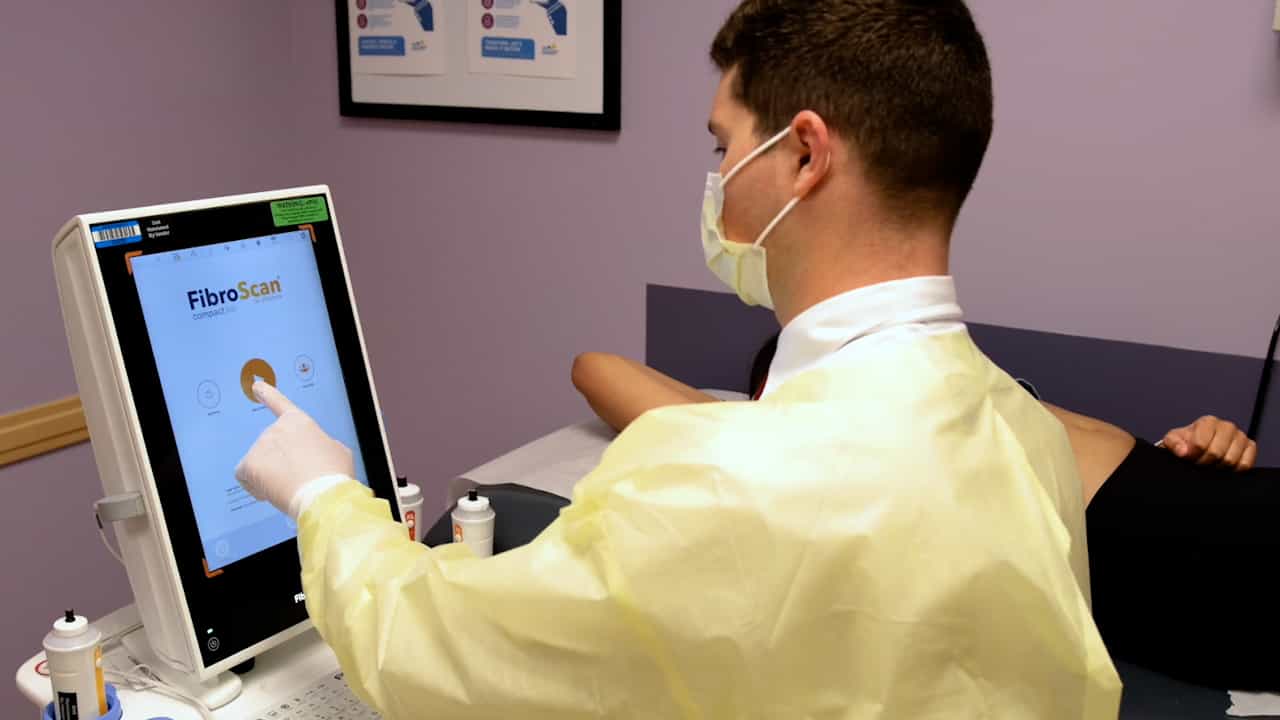
- FibroScan® with Controlled Attenuation Parameter (CAP) offers a potential tool for assessing liver fat content.
Purpose of the Study:
- To evaluate the diagnostic accuracy of CAP for detecting and grading liver steatosis in severely obese children.
- To compare the performance of CAP head-to-head with conventional B-mode ultrasound (US) in a screening setting.
Main Methods:
- Sixty severely obese children underwent CAP and B-mode US assessments.
- Magnetic resonance spectroscopy proton density fat fraction (MRS-PDFF) served as the reference standard.
- A standardized scoring system was applied for both CAP and US evaluations.
Main Results:
- Steatosis was detected in 60% of the children.
- The area under the ROC curve (AUROC) for CAP in detecting steatosis (≥S1) was 0.80, compared to 0.68 for US (p=0.09).
- CAP demonstrated higher specificity than US when US relied solely on liver echogenicity for steatosis detection (75% vs. 46%, p=0.04).
Conclusions:
- CAP's overall performance is comparable to standardized US for detecting liver steatosis in obese children.
- CAP may be superior to US when US is based only on liver echogenicity for screening.
- Both CAP and standardized US are viable options for detecting steatosis in this pediatric cohort.
Objectives:
To determine the diagnostic accuracy of controlled attenuation parameter (CAP) on FibroScan® in detecting and grading steatosis in a screening setting and perform a head-to-head comparison with conventional B-mode ultrasound.
Methods:
Sixty children with severe obesity (median BMI z-score 3.37; median age 13.7 years) were evaluated. All underwent CAP and US using a standardized scoring system. Magnetic resonance spectroscopy proton density fat fraction (MRS-PDFF) was used as a reference standard.
Results:
Steatosis was present in 36/60 (60%) children. The areas under the ROC (AUROC) of CAP for the detection of grade ≥ S1, ≥ S2, and ≥ S3 steatosis were 0.80 (95% CI: 0.67-0.89), 0.77 (95% CI: 0.65-0.87), and 0.79 (95% CI: 0.66-0.88), respectively. The AUROC of US for the detection of grade ≥ S1 steatosis was 0.68 (95% CI: 0.55-0.80) and not significantly different from that of CAP (p = 0.09). For detecting ≥ S1 steatosis, using the optimal cutoffs, CAP (277 dB/m) and US (US steatosis score ≥ 2) had a sensitivity of 75% and 61% and a specificity of 75% and 71%, respectively. When using echogenicity of liver parenchyma as only the scoring item, US had a sensitivity of 70% and specificity of 46% to detect ≥ S1 steatosis. The difference in specificity of CAP and US when using only echogenicity of liver parenchyma of 29% was significant (p = 0.04).
Conclusion:
The overall performance of CAP is not significantly better than that of US in detecting steatosis in children with obesity, provided that the standardized scoring of US features is applied. When US is based on liver echogenicity only, CAP outperforms US in screening for any steatosis (≥ S1).
Key Points:
• The areas under the ROC curves of CAP and ultrasound (US) for detecting grade ≥ S1 steatosis were 0.80 and 0.68, respectively, and were not significantly different (p = 0.09). • For detecting grade ≥ S1 steatosis in severely obese children, CAP had a sensitivity of 75% and a specificity of 75% at its optimal cutoff value of 277 dB/m. • For detecting grade ≥ S1 steatosis in clinical practice, both CAP and US can be used, provided that the standardized scoring of US images is used.

Related Concept Videos
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test