Related Experiment Video
Updated: Dec 8, 2025
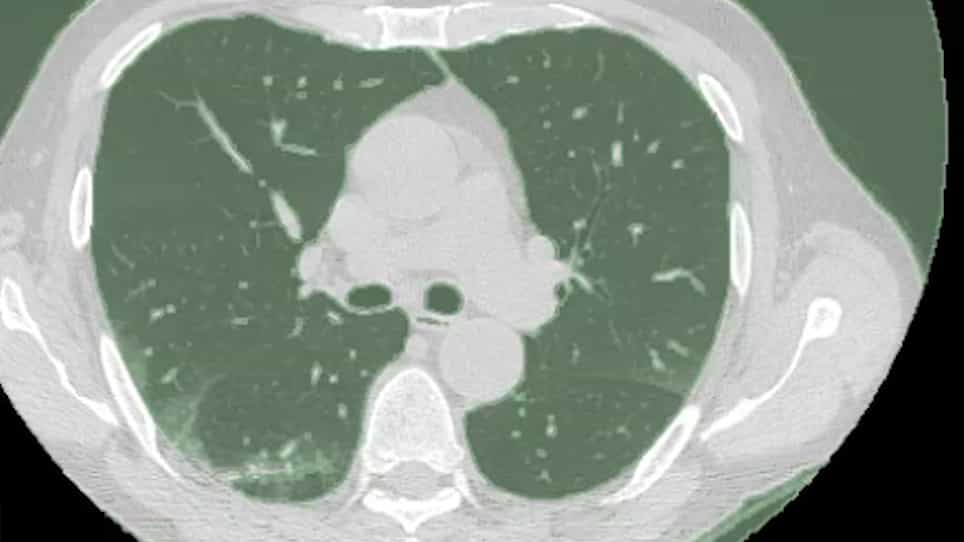
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Prognostic factors in patients admitted to an urban teaching hospital with COVID-19 infection
Donogh Maguire1, Marylynne Woods2, Conor Richards2
1Emergency Medicine Department, Glasgow Royal Infirmary, 84 Castle Street, Glasgow, G4 0SF, UK. Donogh.Maguire@glasgow.ac.uk.

Background:
Severe COVID-19 infection results in a systemic inflammatory response (SIRS). This SIRS response shares similarities to the changes observed during the peri-operative period that are recognised to be associated with the development of multiple organ failure.
Methods:
Electronic patient records for patients who were admitted to an urban teaching hospital during the initial 7-week period of the COVID-19 pandemic in Glasgow, U.K. (17th March 2020-1st May 2020) were examined for routine clinical, laboratory and clinical outcome data. Age, sex, BMI and documented evidence of COVID-19 infection at time of discharge or death certification were considered minimal criteria for inclusion.
Results:
Of the 224 patients who fulfilled the criteria for inclusion, 52 (23%) had died at 30-days following admission. COVID-19 related respiratory failure (75%) and multiorgan failure (12%) were the commonest causes of death recorded. Age ≥ 70 years (p < 0.001), past medical history of cognitive impairment (p ≤ 0.001), previous delirium (p < 0.001), clinical frailty score > 3 (p < 0.001), hypertension (p < 0.05), heart failure (p < 0.01), national early warning score (NEWS) > 4 (p < 0.01), positive CXR (p < 0.01), and subsequent positive COVID-19 swab (p ≤ 0.001) were associated with 30-day mortality. CRP > 80 mg/L (p < 0.05), albumin < 35 g/L (p < 0.05), peri-operative Glasgow Prognostic Score (poGPS) (p < 0.05), lymphocytes < 1.5 109/l (p < 0.05), neutrophil lymphocyte ratio (p ≤ 0.001), haematocrit (< 0.40 L/L (male)/ < 0.37 L/L (female)) (p ≤ 0.01), urea > 7.5 mmol/L (p < 0.001), creatinine > 130 mmol/L (p < 0.05) and elevated urea: albumin ratio (< 0.001) were also associated with 30-day mortality. On multivariate analysis, age ≥ 70 years (O.R. 3.9, 95% C.I. 1.4-8.2, p < 0.001), past medical history of heart failure (O.R. 3.3, 95% C.I. 1.2-19.3, p < 0.05), NEWS > 4 (O.R. 2.4, 95% C.I. 1.1-4.4, p < 0.05), positive initial CXR (O.R. 0.4, 95% C.I. 0.2-0.9, p < 0.05) and poGPS (O.R. 2.3, 95% C.I. 1.1-4.4, p < 0.05) remained independently associated with 30-day mortality. Among those patients who tested PCR COVID-19 positive (n = 122), age ≥ 70 years (O.R. 4.7, 95% C.I. 2.0-11.3, p < 0.001), past medical history of heart failure (O.R. 4.4, 95% C.I. 1.2-20.5, p < 0.05) and poGPS (O.R. 2.4, 95% C.I. 1.1-5.1, p < 0.05) remained independently associated with 30-days mortality.
Conclusion:
Age ≥ 70 years and severe systemic inflammation as measured by the peri-operative Glasgow Prognostic Score are independently associated with 30-day mortality among patients admitted to hospital with COVID-19 infection.

Related Concept Videos
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:30
Pneumonia III: Complications and Assessment
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...