Related Experiment Video
Updated: Dec 8, 2025

Author Spotlight: Unraveling the Impact of Mechanical Ventilation on Diaphragm Function and Patient Outcomes
Published on: November 3, 2023
Diaphragmatic atrophy and dysfunction in critically ill mechanically ventilated children
Sabyasachi Mistri1, Nitin Dhochak1, Manisha Jana2
1Department of Pediatrics, All India Institute of Medical Sciences, New Delhi, India.

Insights
Critically ill children on mechanical ventilation experience significant diaphragmatic atrophy within the first week. Pressure-targeted ventilation showed a lower atrophy rate compared to volume-targeted ventilation.
Area of Science:
- Pediatric Critical Care Medicine
- Respiratory Physiology
- Mechanical Ventilation
Background:
- Diaphragmatic atrophy and dysfunction are concerns in critically ill children, particularly in developing countries.
- The extent and progression of diaphragmatic changes during mechanical ventilation in this population are not well-established.
Purpose of the Study:
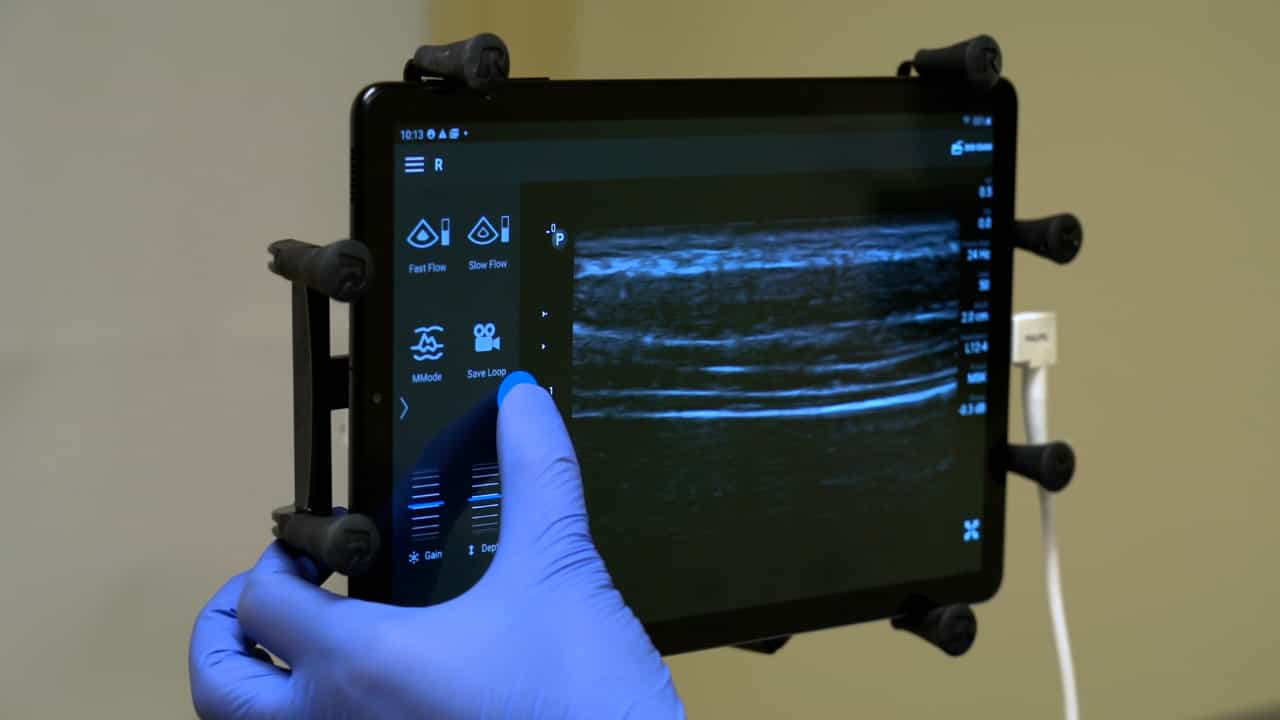
- To quantify changes in diaphragmatic thickness using ultrasound over the first week of mechanical ventilation in critically ill children.
- To determine the magnitude and identify risk factors associated with diaphragmatic atrophy.
Main Methods:
- An observational cohort study included children aged 1-18 years requiring mechanical ventilation.
- Ultrasound measurements of diaphragmatic thickness at end-expiration (DTe) and end-inspiration (DTi), and diaphragmatic thickening fraction (DTF) were recorded daily for the first week.
- Diaphragmatic atrophy percentage and daily atrophy rate were calculated.
Main Results:
- A significant reduction in DTe was observed over the first week of ventilation (p < .001).
- Median diaphragmatic atrophy was 9.91% with an atrophy rate of 2.01% per day.
- Pressure-targeted ventilation was associated with a lower diaphragmatic atrophy rate (1.79%/day) compared to volume-targeted ventilation (3.10%/day; p = .038).
Conclusions:
- The diaphragm undergoes progressive atrophy during the initial week of mechanical ventilation in critically ill children.
- Further research into ventilation strategies aimed at mitigating diaphragmatic atrophy is warranted.
Rationale:
The extent of diaphragmatic atrophy and dysfunction in critically ill children from developing countries is not established.
Objectives:
To estimate changes in ultrasound measurements of diaphragmatic thickness over the first week of mechanical ventilation. To assess magnitude and risk factors of diaphragmatic atrophy.
Methods:
In an observational cohort study, children aged 1-18 years, requiring mechanical ventilation were included. Ultrasound measurements of diaphragmatic thickness at end-expiration (DTe) and end-inspiration (DTi), and diaphragmatic thickening fraction (DTF) were performed daily during the first week of admission, and pre- and post-extubation. Diaphragmatic atrophy (%) and atrophy rate (rate of decline in DTe, % per day) were calculated.
Measurements And Main Results:
Of 55 children (74.6% boys) enrolled, 20 (36.4%) died. Of 35 children with planned extubation, 5 (14.3%) required reintubation. Baseline median (interquartile range [IQR]) DTe, DTi, and DTF were 1.27 mm (1, 1.6), 1.76 mm (1.35, 2.10), and 33.75% (26.90, 44.60), respectively. There was a significant reduction in DTe over the first week of mechanical ventilation (p < .001), median (IQR) diaphragmatic atrophy and atrophy rate of 9.91% (5.26, 17.35) and 2.01% (1.08, 3.04) per day, respectively. Diaphragmatic atrophy rate was lower in pressure targeted ventilation (n = 44; 1.79% [1.03, 2.87]) than volume targeted ventilation (n = 11; 3.10% [1.31, 5.49]), p = .038. There was no difference in diaphragmatic parameters (atrophy rate, and peri-extubation DTe and DTF) in extubation success versus failure.
Conclusions:
The diaphragm undergoes progressive atrophy during the first week of mechanical ventilation in critically ill children. Future studies should evaluate ventilation strategies to reduce the diaphragmatic atrophy.


Related Concept Videos
 01:30
Acute Respiratory Failure-III
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:17
Pulmonary Cycle: Exhalation
 01:23
Acute Respiratory Failure-IV
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...