

Relation of High-sensitivity Cardiac Troponin I Elevation With Exercise to Major Adverse Cardiovascular Events in
Bruno B Lima1, Muhammad Hammadah1, Jeong Hwan Kim2
1Emory Clinical Cardiovascular Research Institute, Department of Medicine, Division of Cardiology, Emory University School of Medicine, Atlanta, Georgia; Department of Epidemiology, Rollins School of Public Health, Emory University, Atlanta, Georgia.

Insights
Elevated cardiac troponin I (hs-cTnI) after exercise stress testing predicts major adverse cardiac events in stable coronary artery disease (CAD) patients. Changes in hs-cTnI offer prognostic value beyond traditional risk factors.
Area of Science:
- Cardiology
- Biomarkers
- Clinical Risk Stratification
Background:
- High-sensitive cardiac troponin I (hs-cTnI) levels increase with inducible myocardial ischemia in patients with coronary artery disease (CAD).
- The prognostic significance of hs-cTnI changes during exercise stress testing for major adverse cardiac events (MACE) in stable CAD remains to be fully elucidated.
Purpose of the Study:
- To assess the association between exercise-induced changes in hs-cTnI levels and the occurrence of MACE in patients with stable CAD.
- To determine if hs-cTnI dynamics improve risk prediction beyond traditional factors and inducible ischemia.
Main Methods:
- A cohort of 365 stable CAD patients underwent treadmill exercise stress testing with myocardial perfusion imaging.
- Plasma hs-cTnI levels were measured at rest and 45 minutes post-stress.
- Multivariable Fine & Gray's subdistribution hazards models analyzed the association between hs-cTnI changes and MACE (cardiovascular death, myocardial infarction, unstable angina requiring revascularization) over a median 3-year follow-up.
Main Results:
- 39 patients (11%) experienced MACE.
- Each two-fold increment in hs-cTnI with stress was associated with a 2.2-fold increase in MACE hazard.
- High resting hs-cTnI and ≥20% stress-induced elevation showed the highest MACE incidence (SHR 4.6).
- Adding hs-cTnI levels (resting and change) significantly improved risk model discrimination (C-statistic 0.67 to 0.71).
Conclusions:
- Higher resting hs-cTnI levels and exercise-induced elevation predict adverse cardiovascular outcomes in stable CAD.
- hs-cTnI dynamics provide prognostic information beyond traditional risk factors and inducible ischemia detected by SPECT.
- hs-cTnI measurements during stress testing can enhance risk stratification in stable CAD patients.
Abstract:
High sensitive cardiac troponin I (hs-cTnI) increases with inducible myocardial ischemia in patients with coronary artery disease (CAD). We aimed to assess if the change in hs-cTnI levels with exercise stress testing is associated with major adverse cardiac events (MACE). A cohort of 365 (age 62 ± 9 years, 77% men) patients with stable CAD underwent 99mTc sestamibi myocardial perfusion imaging with treadmill testing. Plasma hs-cTnI level was measured at rest and at 45 min after stress. Multivariable Fine & Gray's subdistribution hazards models were used to determine the association between the change in hs-cTnI and MACE, a composite end point of cardiovascular death, myocardial infarction, and unstable angina requiring revascularization. During a median follow-up of 3 years, 39 (11%) patients experienced MACE. After adjustment, for each two-fold increment in hs-cTnI with stress, there was a 2.2 (95% confidence interval 1.3-3.6)-fold increase in the hazard for MACE. Presence of both a high resting hs-cTnI level (>median) and ≥ 20% stress-induced hs-cTnI elevation was associated with the highest incidence of MACE (subdistribution hazards models 4.6, 95% confidence interval 1.6 to 13.0) compared with low levels of both. Risk discrimination statistics significantly improved after addition of resting and change in hs-cTnI levels to a model including traditional risk factors and inducible ischemia (0.67 to 0.71). Conversely, adding inducible ischemia by SPECT did not significantly improve the C-statistic from a model including traditional risk factors, baseline and change in hs-cTnI (0.70 to 0.71). In stable CAD patients, higher resting levels and elevation of hs-cTnI with exercise are predictors of adverse cardiovascular outcomes beyond traditional cardiovascular risk factors and presence of inducible ischemia.
More Related Videos
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
 04:41
Digital PCR for Quantifying Circulating MicroRNAs in Acute Myocardial Infarction and Cardiovascular Disease
Published on: July 3, 2018
Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:26
Exercise Stress Test
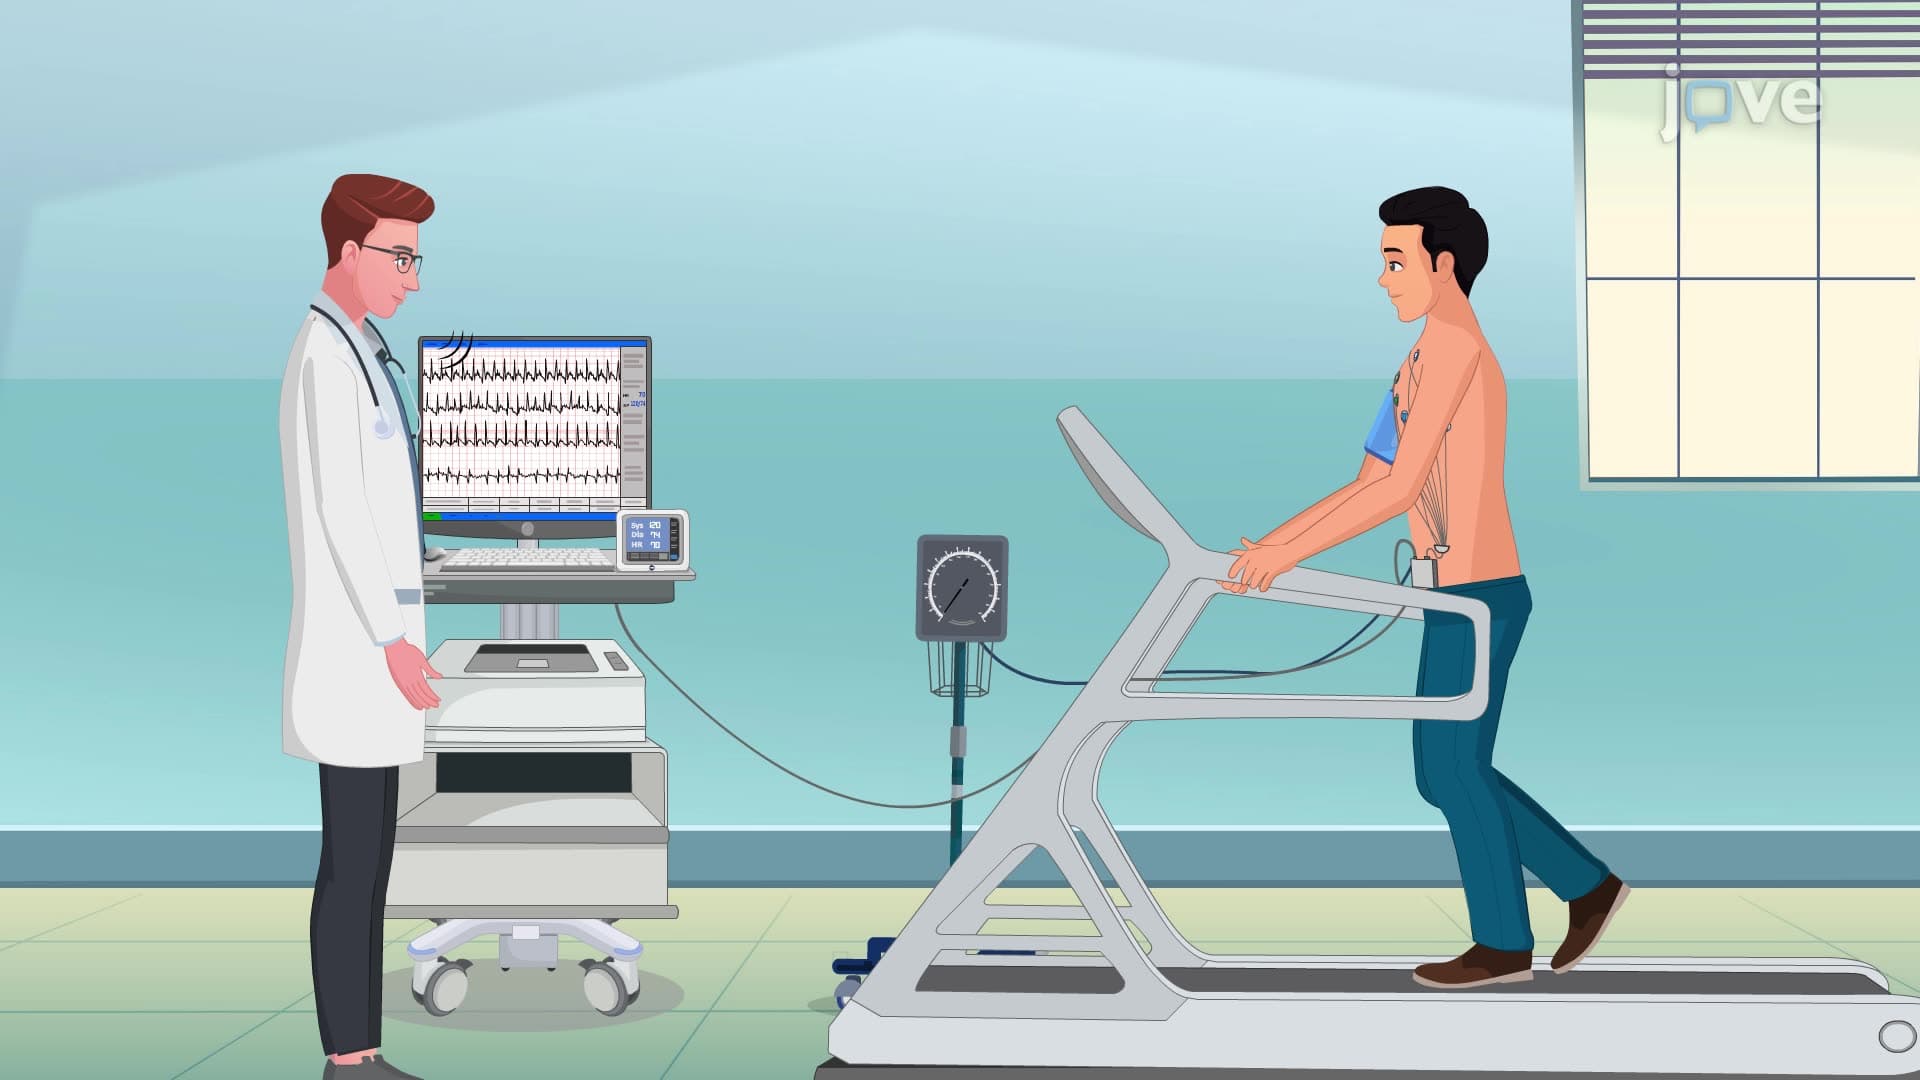
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations