Related Experiment Video
Updated: Dec 8, 2025


Diagnosis of Hirschsprung's Disease by Immunostaining Rectal Suction Biopsies for Calretinin, S100 Protein and Protein Gene Product 9.5
Published on: April 26, 2019
What is the appropriate aganglionic bowel length on contrast enema for attempting single stage transanal endorectal
Bahar Ashjaei1, Afshar Ghamari Khameneh2, Neda Pak3
1Department of Pediatric surgery, Pediatric center of excellence, Tehran University of Medical Sciences, Tehran, Iran.

Insights
Single-stage transanal endorectal pull-through (TERPT) is safe for Hirschsprung disease (HD) patients older than 10 months with aganglionic length under 52 cm, reducing the need for laparotomy.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Colorectal Surgery
Background:
- Hirschsprung disease (HD) is a congenital disorder characterized by the absence of ganglion cells in the distal bowel.
- Single-stage transanal endorectal pull-through (TERPT) is a surgical approach for HD.
- Patient selection and surgical technique are crucial for successful TERPT outcomes.
Purpose of the Study:
- To determine the influence of patient age and abnormal bowel length on the surgical technique for single-stage TERPT in HD.
- To identify predictive factors for operative approach in HD patients undergoing TERPT.
Main Methods:
- Observational study over 2.5 years including children under 14 with suspected HD.
- Contrast enema (CE) used to measure aganglionic bowel length (distance from anus to transitional zone).
- Preoperative biopsy confirmed diagnosis; statistical analysis included t-tests, correlation, and ROC analysis.
Main Results:
- Mean aganglionic bowel length measured 33.5 cm on CE and 56.8 cm pathologically (p < 0.01).
- A length of 52 cm predicted laparoscopy/laparotomy need with 75% sensitivity and 85% specificity.
- Significant differences in CE vs. pathology measurements were noted in infants < 10 months (p = .004).
Conclusions:
- Single-stage TERPT is feasible for HD patients older than 10 months with aganglionic length < 52 cm on CE.
- These criteria predict a low chance of requiring additional laparotomy or laparoscopy.
- Age and bowel length are key factors in planning TERPT for HD.
Purpose:
To identify influence of different values of age and abnormal bowel length in HD patients selected for single stage TERPT which affects the technique of surgery.
Methods:
This observational study was carried out for over 2.5 years. All children younger than 14 years old with clinical suspicion for HD, typical transitional zone (TZ) on contrast enema (CE) distal to splenic flexure, preoperative diagnosis approved by full thickness biopsy, no previous surgical history and no urgency were included. The distance between the anus and TZ was considered as aganglionic length on CE. Biopsy was taken from distal to proximal of resected bowel to reach circumferentially normal innervated bowel. Paired sample Student's t-test, Pearson correlation test, receiver operating characteristic (ROC) analysis were performed.
Results:
Forty-eight patients were enrolled in this study. Measured mean for aganglionic bowel length on CE and pathology were 33.5 ± 17.1 cm and 56.8 ± 33.5 cm, respectively (p < 0.01). Correlation coefficient (R) and coefficient of determination (R2) were 0.632 and 40%, respectively (p < 0.01). The difference between radiologic and pathologic measurements in females was higher than males (mean: 29.3 vs 21.9 cm) but was not statistically significant (p = 0.75). There was statistically significant difference between CE and pathologic results in the infants younger than 10 months (p = .004). Abnormal bowel length equal to 52 cm predicted requirement of laparoscopy assistance/laparotomy with 75% sensitivity and 85% specificity.
Conclusion:
Our investigation showed it is safe to attempt for single stage TERPT when aganglionic length on CE is less than 52 cm and the child with HD is older than 10 months. Chance of requiring additional laparotomy or laparoscopy assistance is low in these patients.
Type Of Study:
Study of diagnostic test.
Level Of Evidence:
Level II.


Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:23
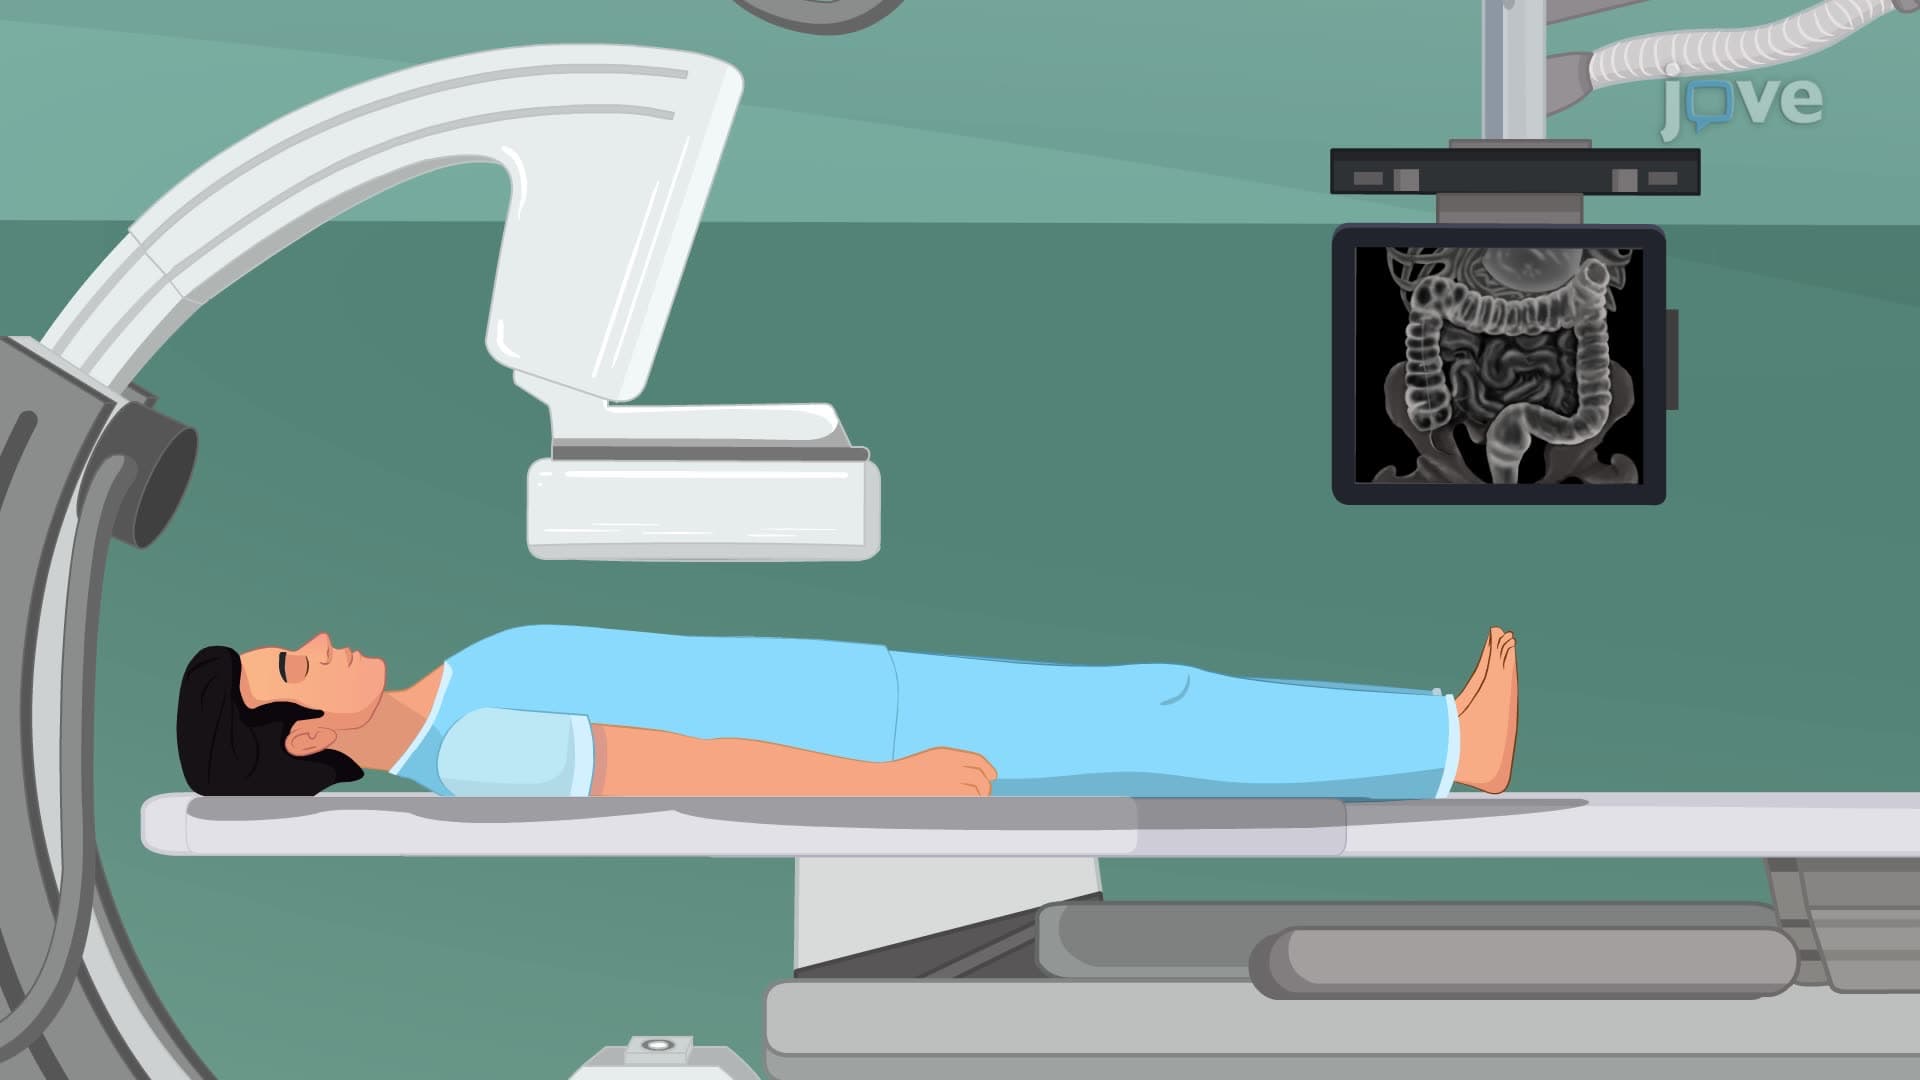
Lower GI Series: Barium Enema
Procedure Details
The examination begins by inserting a lubricated rectal tube into the patient's rectum to administer a radiopaque barium solution. The barium flow is carefully...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...