Predicting the risk for major bleeding in elderly patients with venous thromboembolism using the Charlson index. Findings from the RIETE
Related Experiment Video
Updated: Dec 8, 2025
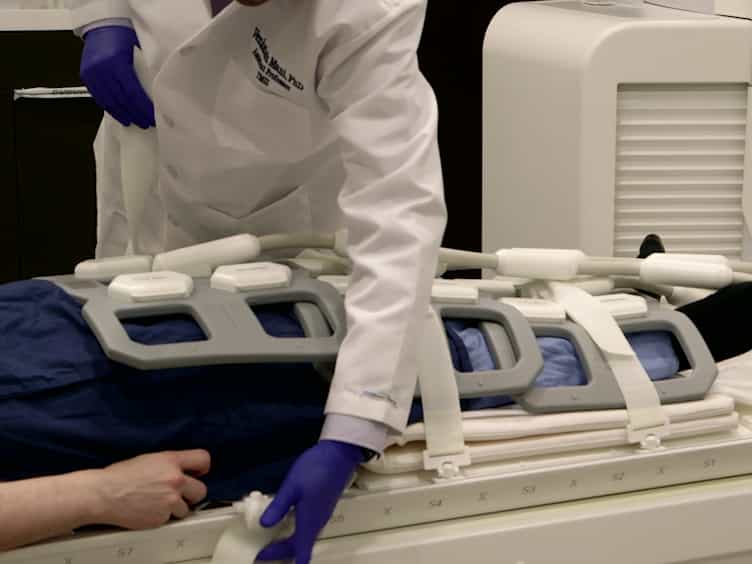
A Multicenter MRI Protocol for the Evaluation and Quantification of Deep Vein Thrombosis
Published on: June 2, 2015
Covadonga Gómez-Cuervo1, Agustina Rivas2, Adriana Visonà3
1Department of Internal Medicine, Hospital Universitario, 12 de Octubre, Avenida de Córdoba s/n 28041, Madrid, Spain. covadonga.gomez@salud.madrid.org.

Insights
The Comorbidity Charlson Index (CCI) shows modest ability to predict major bleeding in elderly patients on anticoagulation for venous thromboembolism (VTE). A CCI score of 4 or less may help identify older VTE patients who benefit more from extended anticoagulation.
Area of Science:
- Cardiology
- Geriatrics
- Hematology
Background:
- Elderly patients on anticoagulant therapy for venous thromboembolism (VTE) face elevated bleeding risks.
- Risk stratification is crucial for optimizing extended anticoagulation in this population.
Purpose of the Study:
- To evaluate the Comorbidity Charlson Index (CCI) prognostic ability for major bleeding in patients aged over 75 years receiving anticoagulation for VTE beyond three months.
- To assess if CCI improves risk prediction compared to existing scores.
Main Methods:
- Analysis of data from the RIETE registry, including 4303 patients aged >75 years.
- Calculation of Area Under the Receiver-Operating Characteristic Curve (AUC), Net Reclassification Index (NRI), and Net Benefit (NB).
- Assessment of a CCI cut-off of 4 points (CCI4) for predicting major bleeding.
Main Results:
- The overall AUC for CCI predicting major bleeding was modest (0.569).
- Patients with CCI ≤ 4 had significantly lower rates of major bleeding and all-cause death compared to those with CCI > 10.
- CCI4 demonstrated 82% sensitivity and 30% specificity for predicting major bleeding beyond three months.
- CCI4 reclassification improved the Net Benefit (NB) of the RIETE bleeding score for predicting bleeding.
Conclusions:
- While the CCI's AUC for predicting major bleeding is modest, it can aid in identifying elderly VTE patients (>75 years) who may benefit more from extended anticoagulation due to lower bleeding risk and better survival.
- The CCI, particularly a score of 4 or less, offers value in refining risk assessment for extended anticoagulation in older VTE patients.
Abstract:
Old patients receiving anticoagulant therapy for venous thromboembolism (VTE) are at an increased risk for bleeding. We used data from the RIETE registry to assess the prognostic ability of the Comorbidity Charlson Index (CCI) to predict the risk for major bleeding in patients aged > 75 years receiving anticoagulation for VTE beyond the third month. We calculated the area under the receiver-operating characteristic curve (AUC), the category-based net reclassification index (NRI) and the net benefit (NB). We included 4303 patients with a median follow-up of 706 days (interquartile range [IQR] 462-1101). Of these, 147 (3%) developed major bleeding (27 died of bleeding). The AUC was 0.569 (95% CI 0.524-0.614). Patients with CCI ≤ 4 points were at a lower risk for adverse outcomes than those with CCI > 10 (major bleeding 0.81 (95% CI 0.53-1.19) vs. 2.21 (95% CI 1.18-3.79) per 100 patient-years; p < 0.05; all-cause death 1.9 (95% CI 1.45-2.44) vs. 15.67 (95% CI 12.63-19.22) per 100 patient-years; p < 0.05). A cut-off point of 4 points (CCI4) had a sensitivity of 82% (95% CI 75-89) and a specificity of 30% (95% CI 29-31) to predict major bleeding beyond the third month. CCI4 reclassification improved the NB of the RIETE bleeding score to predict bleeding beyond the third month (CCI4 NB 1.78% vs. RIETE NB 0.44%). Although the AUC of the CCI to predict major bleeding was modest, it could become an additional help to select patients aged > 75 years that obtain more benefit of extended anticoagulation, due to a lower risk for bleeding and better survival.
Related Concept Videos
 01:30
Venous Thrombosis IV: Nursing Management
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis I: Introduction
 01:20
Venous Thrombosis II: Clinical Manifestations and Diagnostic Studies
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care