Related Experiment Video
Updated: Dec 8, 2025

Author Spotlight: An Economic and Efficient Method for Quantitative Evaluation of Bone Microarchitecture in a Murine Osteoporosis Model
Published on: September 8, 2023
Adiposity and bone microarchitecture in the GLOW study
A E Litwic1,2, L D Westbury1, K Ward1
1MRC Lifecourse Epidemiology Unit, University of Southampton, Southampton, UK.

Abstract:
Low body mass index (BMI) is an established risk factor for fractures in postmenopausal women but the interaction of obesity with bone microarchitecture is not fully understood. In this study, obesity was associated with more favourable bone microarchitecture parameters but not after parameters were normalised for body weight.
Introduction:
To examine bone microarchitecture in relation to fat mass and examine both areal bone mineral density (aBMD) and microarchitecture in relation to BMI categories in the UK arm of the Global Longitudinal Study of Osteoporosis in Women.
Methods:
Four hundred and ninety-one women completed questionnaires detailing medical history; underwent anthropometric assessment; high-resolution peripheral quantitative computed tomography (HRpQCT) scans of the radius and tibia and DXA scans of whole body, proximal femur and lumbar spine. Fat mass index (FMI) residuals (independent of lean mass index) were derived. Linear regression was used to examine HRpQCT and DXA aBMD parameters according to BMI category (unadjusted) and HRpQCT parameters in relation to FMI residuals (with and without adjustment for anthropometric, demographic and lifestyle covariates).
Results:
Mean (SD) age was 70.9 (5.4) years; 35.0% were overweight, 14.5% class 1 obese and 7.7% class 2/3 obese. There were significant increasing trends according to BMI category in aBMD of whole body, hip, femoral neck and lumbar spine (p ≤ 0.001); cortical area (p < 0.001), thickness (p < 0.001) and volumetric density (p < 0.03), and trabecular number (p < 0.001), volumetric density (p < 0.04) and separation (p < 0.001 for decreasing trend) at the radius and tibia. When normalised for body weight, all HRpQCT and DXA aBMD parameters decreased as BMI increased (p < 0.001). FMI residuals were associated with bone size and trabecular architecture at the radius and tibia, and tibial cortical microarchitecture.
Conclusion:
Significant trends in HRpQCT parameters suggested favourable bone microarchitecture at the radius and tibia with increasing BMI but these were not proportionate to increased weight.
More Related Videos
 04:24
Proper Positioning and Restraint of a Rat Hind Limb for Focused High Resolution Imaging of Bone Micro-architecture Using In Vivo Micro-computed Tomography
Published on: November 22, 2017
 07:56
Scanning Skeletal Remains for Bone Mineral Density in Forensic Contexts
Published on: January 29, 2018
Related Concept Videos
 01:17
Gross Anatomy of Bone
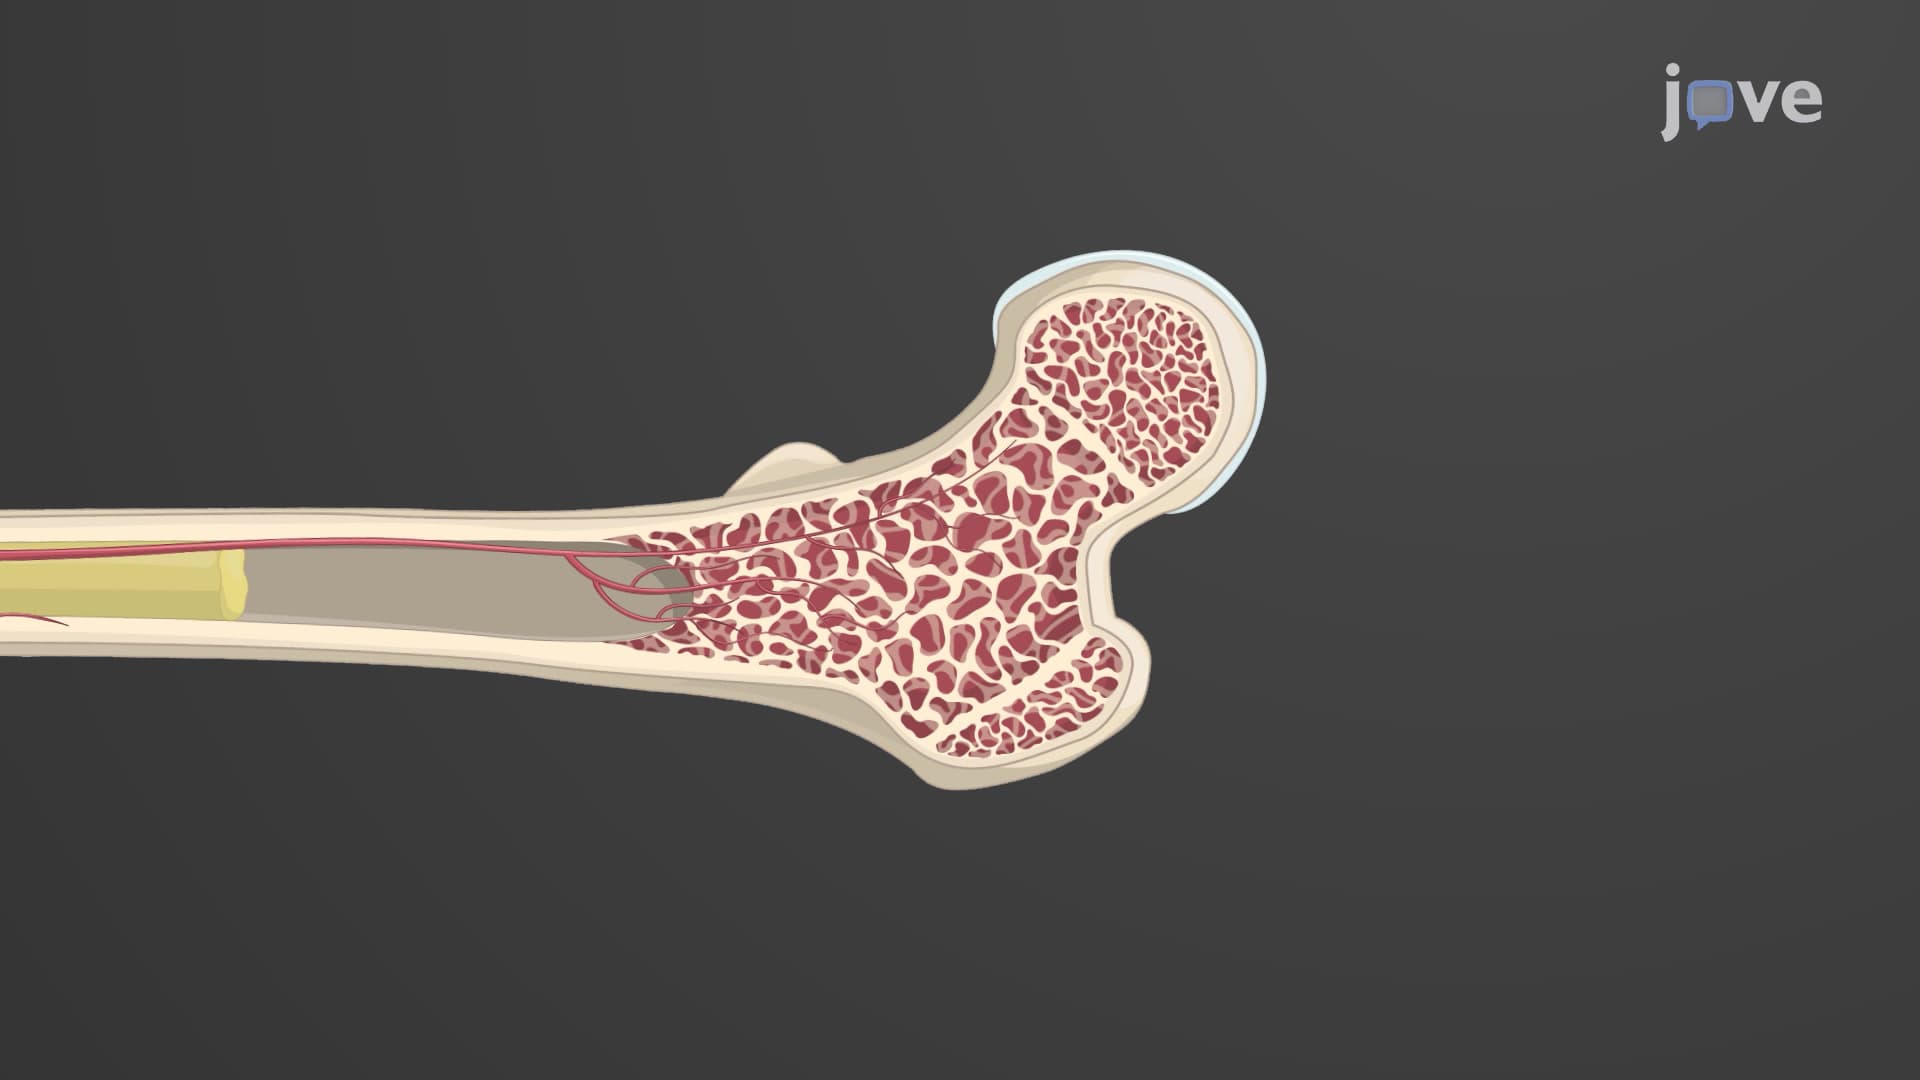
The diaphysis is the tubular shaft that runs between the proximal and distal ends of the bone. The walls of the diaphysis are composed of dense and hard compact bone made of numerous osteons — the functional unit of the compact bone. The hollow region in the diaphysis is called the medullary cavity, which harbors the bone marrow. In infants and children, this marrow cavity is filled with red marrow, whereas in...
 01:55
Bone Structure
 01:27
Compact Bone
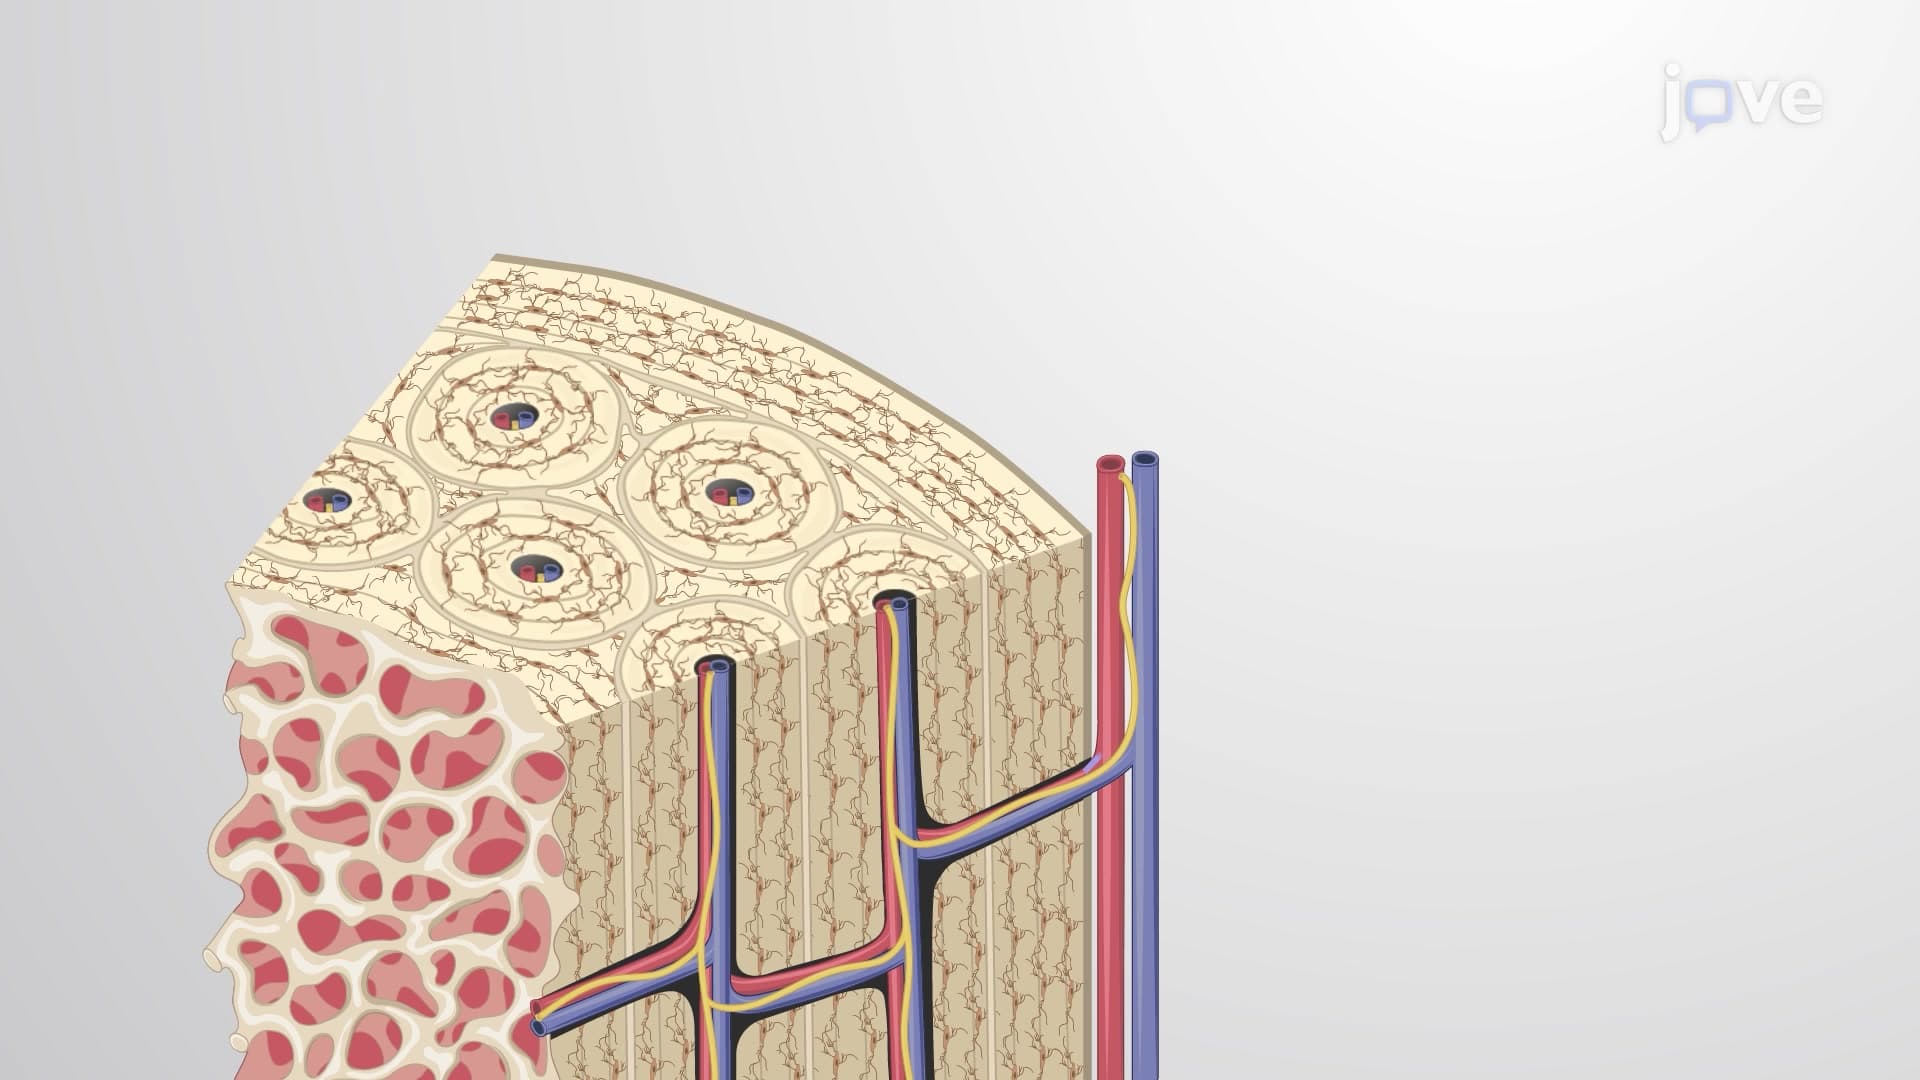
Compact bone, also called cortical bone, is the denser, stronger of the two types of bone tissue. It is found under the periosteum and in the diaphyses of long bones, where it provides support and protection. The microscopic structural unit of compact bone is called an osteon, or haversian system. Each osteon is composed of concentric rings of calcified...
 01:40
Bone Remodeling
 01:27
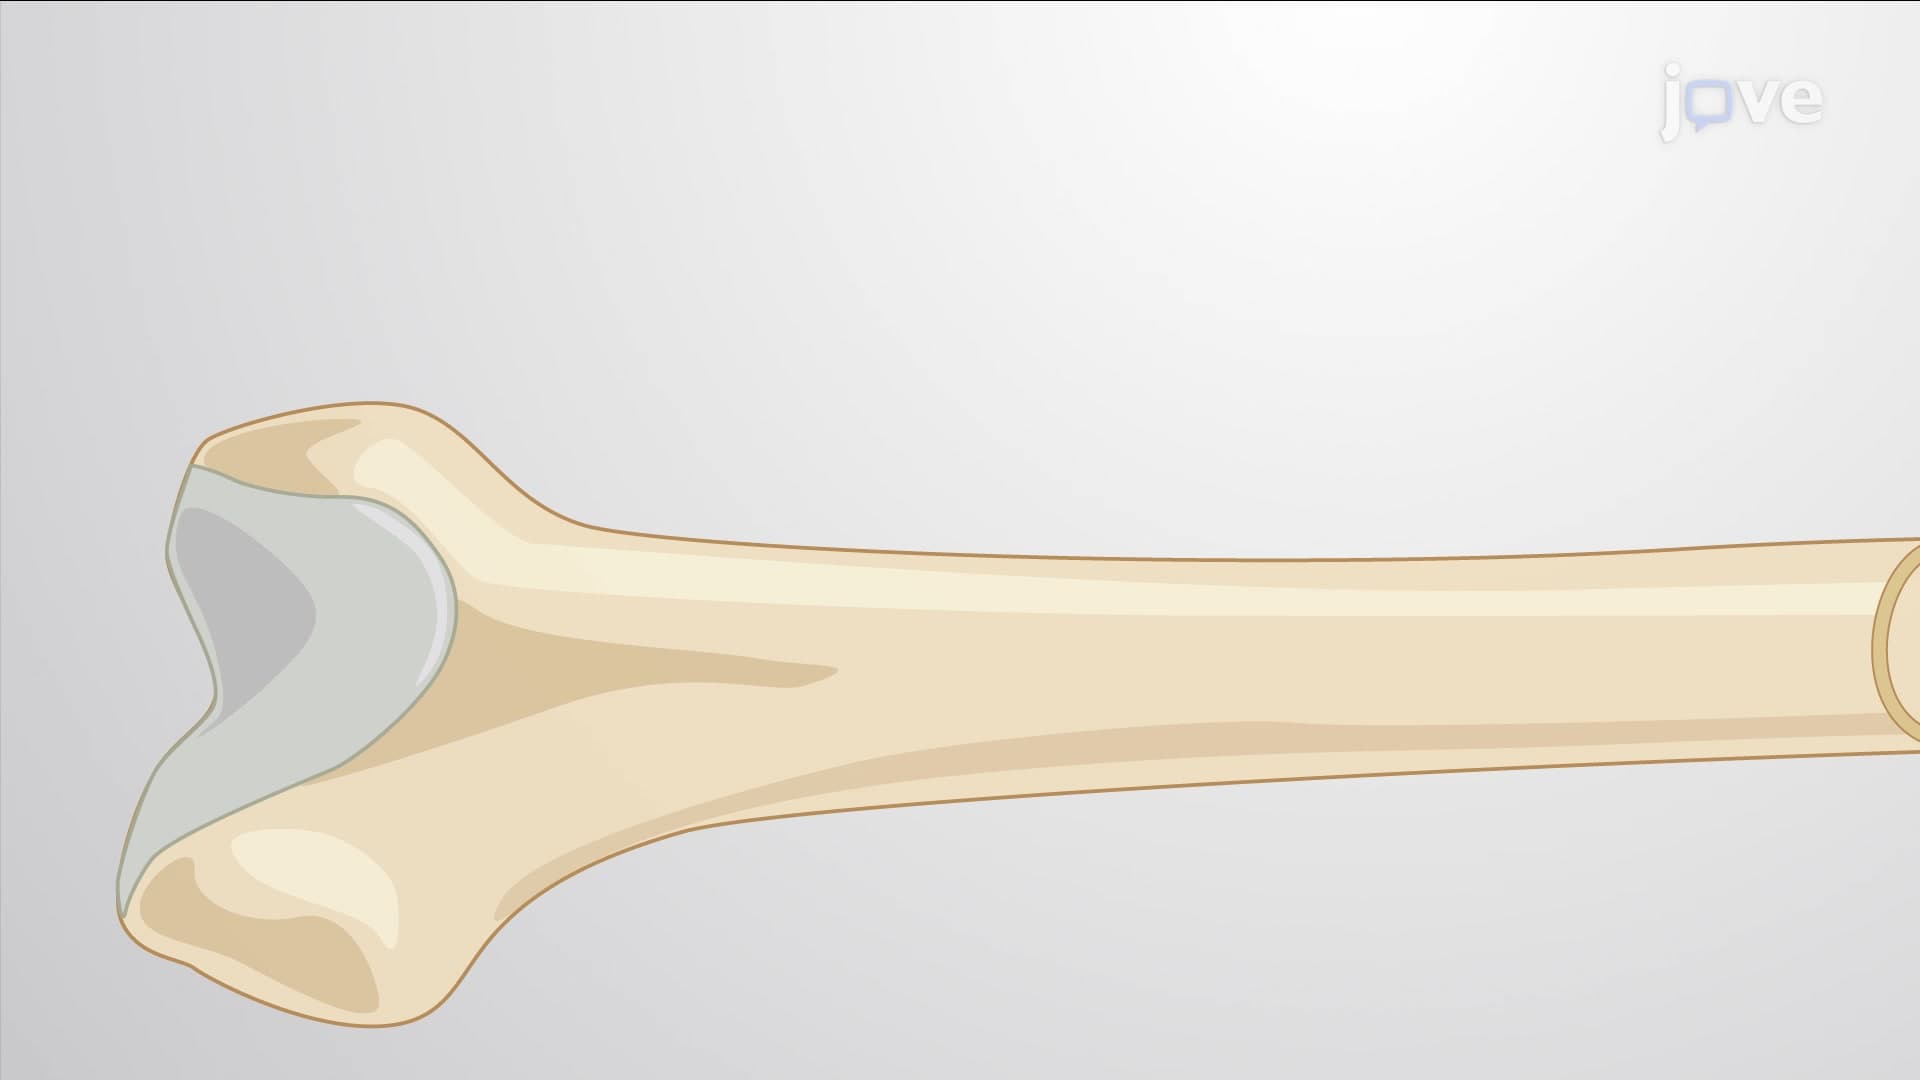
Growth of Cartilage and Bone Tissue
 01:09
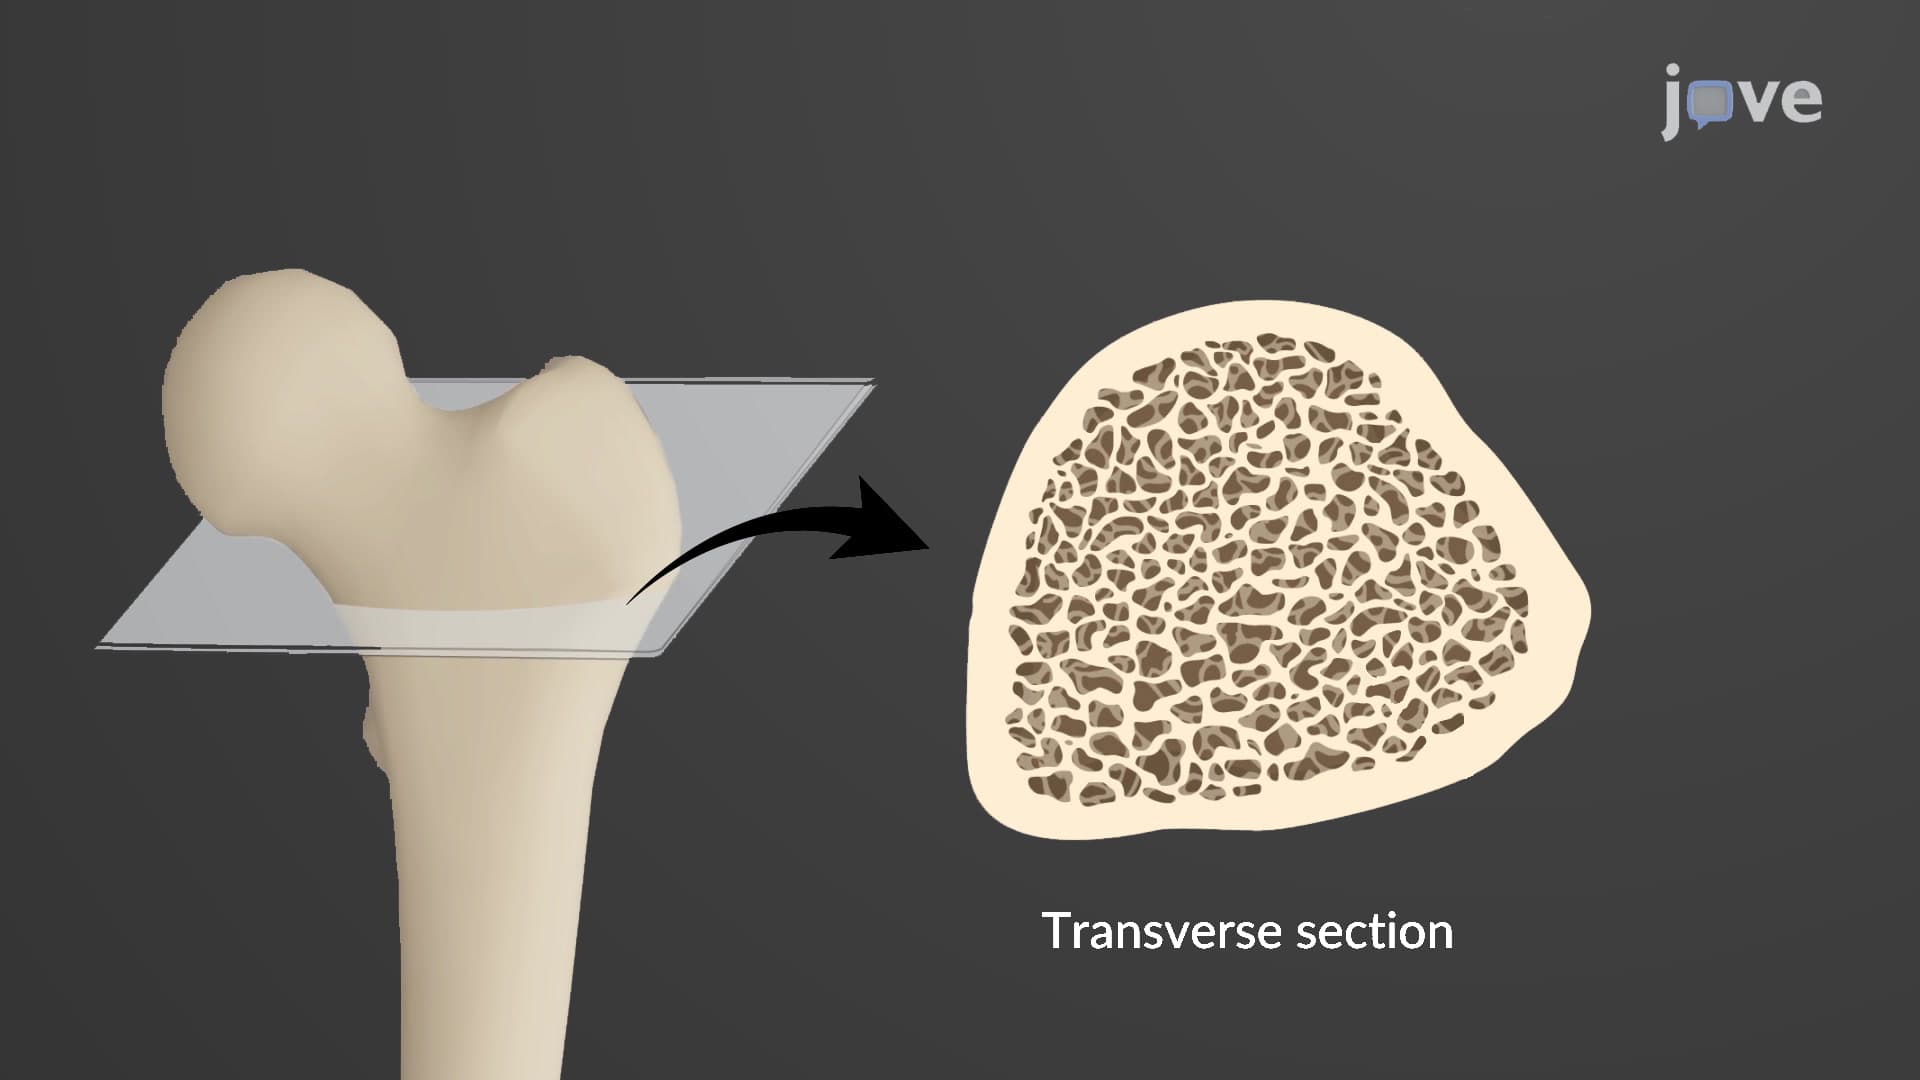
Spongy Bone
Spongy bone is more porous, and less dense compared to compact bone. It is composed of concentric lamellae that are arranged irregularly to form the trabecular network. In some bones, the spaces between trabeculae contain red marrow, where...