Related Experiment Video
Updated: Dec 8, 2025
Laparoscopic Choledochal Cyst Excision and Roux-en-Y Choledochojejunostomy in Adults
Published on: February 28, 2025
Unusual variant of choledochal cyst in a child: A case report, in Tertiary Specialized Hospital, Ethiopia
Workye Tigabie1, Hadush Tesfay1, Dagnachew Tamrat1
1Addis Ababa University, College of Health Sciences, Ethiopia.

Insights
This case report highlights an unusual choledochal cyst (CC) variant. Accurate diagnosis via imaging and meticulous surgical excision are crucial for managing these rare congenital biliary tract anomalies.
Area of Science:
- Pediatric Surgery
- Gastroenterology
- Congenital Anomalies
Background:
- Choledochal cyst (CC) is a rare congenital biliary tract disease.
- CC presents with diverse classifications and subtypes.
- Uncommon variants can pose diagnostic and management challenges.
Observation:
- A 9-year-old female presented with right quadrant abdominal pain.
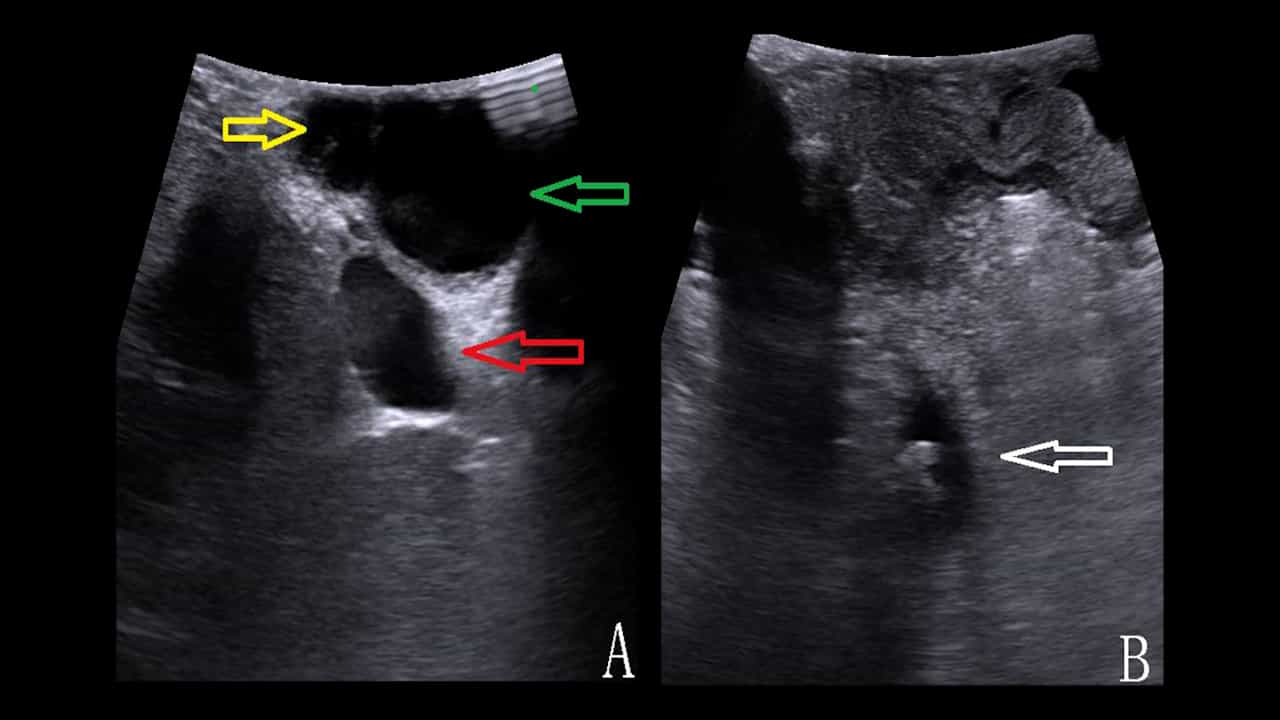
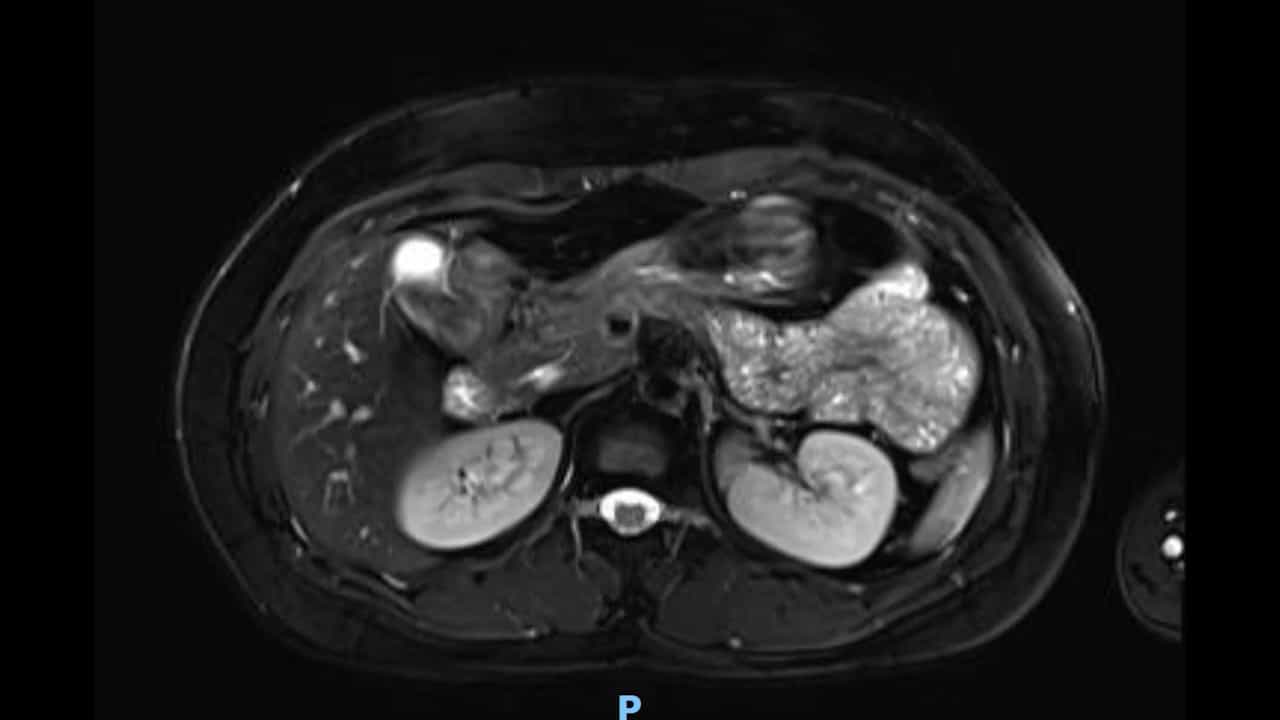
- Abdominal CT scan suggested a type II choledochal cyst.
- Intraoperative findings revealed an unusual posterior location of the cyst at the common hepatic duct confluence.
Findings:
- The choledochal cyst was successfully excised.
- The patient experienced a favorable outcome post-surgery.
- This case represents an anatomical variant not fitting standard CC classifications.
Implications:
- Highlights the importance of detailed pre-operative investigations (CT scan, cholangiography) for choledochal cyst diagnosis.
- Alerts surgeons to the existence of rare anatomical variants of choledochal cysts.
- Emphasizes meticulous surgical dissection to ensure complete excision and prevent complications.
Introduction:
Choledochal cyst (CC) is an uncommon congenital disease of the biliary tract. There are five main types of CC with several recognized sub-types. However, occasional variants with a difficulty in diagnosis and management do occur.
Presentation Of The Case:
We report a case of a nine years old female child diagnosed with CC who presented with right quadrant abdominal pain with unremarkable physical findings. Investigation using abdominal CT scan suggested type II choledochal cyst. The intraoperative finding revealed an unusual site of the cyst that is at the confluence of common hepatic duct (CHD) posteriorly. The cyst was successfully excised and the child is doing well on her follow ups.
Discussion:
In the management of choledochal cyst the anatomy should be clearly defined with detailed investigations like Abdominal CT Scan or cholangiography before surgical excision as abnormal variants which usually do not fit into the known classification types and subtypes. This might confuse with other differentials like gall bladder duplication. Surgical excision is the gold standard management option.
Conclusion:
This case report will alert surgeons that there are different anatomic variant of choledochal cysts out of the known classifications and with meticulous dissection will help proper excision and avoid unnecessary complications.